Correlation of Serum Ferritin and Inflammatory Markers in Anemia of Chronic Disease
- Rohini Srivastava , Associate Professor, Department of Pathology, Naraina Medical College and Research Centre, Kanpur, Uttar Pradesh, India
- Sakshi Sharma , Specialist, Department of Pathology, Cantonment General Hospital, Delhi Cantt, Delhi, India
- Sonal Sharma , Associate Professor, Department of Pathology, Naraina Medical College and Research Centre, Kanpur, Uttar Pradesh, India
- Tarun Nigam , Professor, Department of Psychiatry, Naraina Medical College and Research Institute, Kanpur, Uttar Pradesh, India
Article Information:
Abstract:
Background: Anemia of chronic disease (ACD), also known as anemia of inflammation, is one of the most common forms of anemia encountered in patients with chronic infections, autoimmune disorders, malignancies, and chronic systemic illnesses. Serum ferritin and inflammatory markers play an important role in the diagnosis and assessment of disease severity in ACD.Aim: To evaluate the correlation between serum ferritin levels and inflammatory markers in patients diagnosed with anemia of chronic disease.Materials and Methods: This prospective observational study was conducted in the Department of Pathology, Naraina Medical College and Research Centre, Kanpur, Uttar Pradesh, India, over a period of one year. A total of 120 patients diagnosed with anemia of chronic disease were included. Hematological parameters including hemoglobin, serum ferritin, erythrocyte sedimentation rate (ESR), C-reactive protein (CRP), and serum iron profile were analyzed. Statistical analysis was performed using SPSS version 25. Correlation analysis between serum ferritin and inflammatory markers was assessed using Pearson’s correlation coefficient.Results: The majority of patients belonged to the age group of 41–60 years with male predominance. Elevated serum ferritin, ESR, and CRP levels were observed in most patients. A significant positive correlation was found between serum ferritin and inflammatory markers including ESR and CRP. Serum iron and transferrin saturation were decreased in the majority of cases.Conclusion: Serum ferritin demonstrates significant correlation with inflammatory markers in anemia of chronic disease and serves as an important biochemical indicator in evaluating inflammatory activity and iron metabolism abnormalities. Combined assessment of ferritin and inflammatory markers improves diagnostic accuracy in ACD
Keywords:
Article :
INTRODUCTION:
Anemia is one of the most common hematological abnormalities encountered in clinical practice and is associated with significant morbidity and reduced quality of life. Among the various types of anemia, anemia of chronic disease (ACD), also known as anemia of inflammation, is considered the second most prevalent form after iron deficiency anemia [1]. It is commonly observed in patients suffering from chronic infections, autoimmune disorders, chronic kidney disease, inflammatory conditions, and malignancies [2].
Anemia of chronic disease develops as a consequence of persistent immune activation and chronic inflammatory response. Inflammatory cytokines including interleukin-6 (IL-6), tumor necrosis factor-alpha (TNF-α), and interferon-gamma play a major role in the pathogenesis of ACD by affecting iron metabolism, erythropoietin production, and erythroid progenitor cell proliferation [3]. These cytokines stimulate increased production of hepcidin, a peptide hormone synthesized by the liver, which inhibits iron absorption from the intestine and prevents release of stored iron from macrophages [4]. As a result, iron becomes sequestered within reticuloendothelial cells, leading to restricted iron availability for erythropoiesis despite adequate or increased body iron stores.
Patients with anemia of chronic disease typically present with mild to moderate normocytic normochromic anemia, although microcytic hypochromic anemia may also occur in prolonged disease states [5]. The diagnosis of ACD is often challenging because its laboratory findings may overlap with iron deficiency anemia and other chronic hematological disorders [6].
Serum ferritin is an intracellular iron storage protein widely used as a marker of body iron reserves. However, ferritin also acts as an acute phase reactant and its levels rise significantly during inflammation and infection [7]. Elevated serum ferritin levels in ACD reflect both iron sequestration and inflammatory activity. Therefore, isolated ferritin estimation may not reliably differentiate anemia of chronic disease from iron deficiency anemia without simultaneous assessment of inflammatory markers [8].
Inflammatory markers such as erythrocyte sedimentation rate (ESR) and C-reactive protein (CRP) are commonly elevated in chronic inflammatory conditions and serve as useful indicators of systemic inflammation [9]. CRP is synthesized by hepatocytes in response to inflammatory cytokines and is considered a sensitive marker of acute and chronic inflammatory states [10]. ESR also increases secondary to elevated plasma proteins and inflammatory mediators. Previous studies have demonstrated a significant association between serum ferritin and inflammatory markers in patients with chronic diseases [11].
Evaluation of serum ferritin in combination with inflammatory markers and iron profile parameters including serum iron, total iron binding capacity (TIBC), and transferrin saturation improves the diagnostic accuracy of anemia of chronic disease [12]. This combined approach is particularly important in tertiary care settings where patients frequently present with multiple chronic comorbid conditions contributing to anemia.
Despite increasing recognition of anemia of chronic disease, limited data are available regarding the correlation between serum ferritin and inflammatory markers in Indian populations, particularly in patients with chronic inflammatory disorders attending tertiary care hospitals [13]. Understanding this relationship may assist clinicians in early diagnosis, disease monitoring, and therapeutic management.
Therefore, the present study was undertaken to evaluate serum ferritin levels and their correlation with inflammatory markers such as ESR and CRP in patients diagnosed with anemia of chronic disease at a tertiary care teaching hospital [14,15].
MATERIALS AND METHODS:
Study Design and Setting
The present study was a hospital-based prospective observational study conducted in the Department of Pathology in collaboration with the Department of General Medicine at Naraina Medical College and Research Centre, Kanpur, Uttar Pradesh, India.
Study Duration
The study was carried out over a period of one year from January 2025 to December 2025.
Study Population
The study included patients clinically diagnosed with chronic inflammatory, infectious, autoimmune, malignant, or chronic systemic disorders associated with anemia who attended the outpatient and inpatient departments during the study period.
Sample Size
A total of 120 patients fulfilling the inclusion criteria were enrolled in the study.
Inclusion Criteria
1. Patients aged ≥18 years.
2. Patients diagnosed with anemia based on WHO criteria:
3. Hemoglobin <13 g/dL in males
4. Hemoglobin <12 g/dL in females
5. Patients with evidence of chronic inflammatory or chronic systemic disease for more than three months.
6. Patients willing to provide informed consent.
Exclusion Criteria
1. Patients with acute blood loss anemia.
2. Patients with confirmed iron deficiency anemia.
3. Patients who received blood transfusion within the previous three months.
4. Patients on iron supplementation or erythropoietin therapy.
5. Pregnant females.
6. Patients with hematological malignancies or hemolytic anemia.
7. Patients with severe hepatic failure or hereditary iron overload disorders.
Ethical Consideration
The study protocol was reviewed and approved by the Institutional Ethics Committee of Naraina Medical College and Research Centre, Kanpur. Written informed consent was obtained from all participants prior to enrollment in the study.
Clinical Evaluation
Detailed demographic data including age, gender, presenting complaints, duration of illness, underlying chronic disease, medication history, and clinical examination findings were recorded using a predesigned proforma.
Sample Collection
Under aseptic precautions, approximately 5 mL of venous blood was collected from each participant.
· 2 mL blood was collected in EDTA vial for complete blood count and peripheral smear examination.
· 3 mL blood was collected in plain vial for biochemical investigations including serum ferritin, serum iron, total iron binding capacity (TIBC), and C-reactive protein (CRP).
Samples were transported immediately to the laboratory and processed according to standard laboratory protocols.
Laboratory Investigations
The following hematological and biochemical investigations were performed.
Hematological Parameters
· Hemoglobin (Hb)
· Total leukocyte count (TLC)
· Differential leukocyte count (DLC)
· Red blood cell indices
· Mean corpuscular volume (MCV)
· Mean corpuscular hemoglobin (MCH)
· Mean corpuscular hemoglobin concentration (MCHC)
· Peripheral blood smear examination
· Erythrocyte sedimentation rate (ESR)
Complete blood count was performed using an automated hematology analyzer. Peripheral smears were stained with Leishman stain and examined microscopically.
Biochemical Parameters
· Serum ferritin
· Serum iron
· Total iron binding capacity (TIBC)
· Transferrin saturation
· C-reactive protein (CRP)
Serum ferritin estimation was performed using chemiluminescent immunoassay (CLIA) method. Serum iron and TIBC were measured using colorimetric methods on an automated biochemistry analyzer. Transferrin saturation was calculated using the formula.
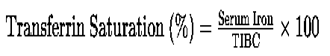
CRP estimation was performed by immunoturbidimetric method. ESR was measured using the Westergren method.
Diagnostic Criteria for Anemia of Chronic Disease
Diagnosis of anemia of chronic disease was established based on:
· Presence of anemia with chronic inflammatory/systemic disease
· Low serum iron levels
· Low or normal TIBC
· Reduced transferrin saturation
· Normal or elevated serum ferritin levels
· Elevated inflammatory markers (ESR and CRP),
Statistical Analysis
All collected data were entered into Microsoft Excel spreadsheet and analyzed using Statistical Package for Social Sciences (SPSS) software version 25.0 Quantitative variables were expressed as mean ± standard deviation (SD), while qualitative variables were expressed as percentages and proportions.
Correlation between serum ferritin and inflammatory markers (ESR and CRP) was assessed using Pearson’s correlation coefficient test.
A p-value of less than 0.05 was considered statistically significant.
RESULTS:
A total of 120 patients diagnosed with anemia of chronic disease were evaluated during the study period. The majority of patients belonged to the age group of 41–60 years. Chronic infections and autoimmune disorders constituted the most common underlying etiologies.
Table 1: Age-wise Distribution of Cases
|
Age Group (Years) |
Number of Cases |
Percentage |
|
18–30 |
18 |
15.0% |
|
31–40 |
24 |
20.0% |
|
41–60 |
52 |
43.3% |
|
>60 |
26 |
21.7% |
|
Total |
120 |
100% |
Male predominance was observed among the study population with males accounting for 58.3% of cases.
Table 2: Gender Distribution
|
Gender |
Number of Cases |
Percentage |
|
Male |
70 |
58.3% |
|
Female |
50 |
41.7% |
|
Total |
120 |
100% |
Most patients showed moderate anemia with reduced serum iron and transferrin saturation levels. Elevated serum ferritin levels were observed in the majority of cases despite low serum iron values.
Table 3: Hematological and Iron Profile Parameters
|
Parameter |
Mean ± SD |
|
Hemoglobin (g/dL) |
8.9 ± 1.4 |
|
Serum Ferritin (ng/mL) |
412 ± 96 |
|
Serum Iron (µg/dL) |
38 ± 12 |
|
TIBC (µg/dL) |
218 ± 34 |
|
Transferrin Saturation (%) |
16 ± 5 |
|
ESR (mm/hr) |
54 ± 18 |
|
CRP (mg/L) |
22 ± 8 |
Inflammatory markers including ESR and CRP were significantly elevated among patients with higher ferritin levels.
Table 4: Correlation of Serum Ferritin with Inflammatory Markers
|
Parameter |
Correlation Coefficient (r) |
p-value |
|
ESR |
+0.68 |
<0.001 |
|
CRP |
+0.72 |
<0.001 |
A significant positive correlation was observed between serum ferritin and inflammatory markers including ESR and CRP.
Among the underlying chronic disorders, chronic infections represented the largest group followed by autoimmune diseases and chronic kidney disease.
Table 5: Underlying Etiology of ACD
|
Etiology |
Number of Cases |
Percentage |
|
Chronic Infections |
42 |
35.0% |
|
Autoimmune Disorders |
30 |
25.0% |
|
Chronic Kidney Disease |
24 |
20.0% |
|
Malignancy |
16 |
13.3% |
|
Chronic Liver Disease |
8 |
6.7% |
|
Total |
120 |
100% |
DISCUSSION:
Anemia of chronic disease (ACD) is a common hematological abnormality associated with chronic inflammatory, infectious, autoimmune, and malignant conditions. The pathogenesis of ACD is multifactorial and involves altered iron metabolism, impaired erythropoietin response, suppression of erythroid progenitor cells, and cytokine-mediated inflammatory activity [1]. The present study was conducted to evaluate the correlation between serum ferritin and inflammatory markers in patients with anemia of chronic disease.
In the present study, the majority of patients belonged to the 41–60 years age group. Similar findings were reported by Weiss and Goodnough [1], who observed that anemia of chronic disease is more frequently encountered in middle-aged and elderly individuals due to the higher prevalence of chronic systemic illnesses in this age group. The increased occurrence of chronic inflammatory and degenerative disorders with advancing age contributes significantly to the development of anemia.
Male predominance was observed in the present study, with males constituting 58.3% of cases. Comparable observations were reported by Roy et al. [13], who demonstrated a higher prevalence of chronic inflammatory disorders among males, particularly chronic infections and chronic kidney disease. Lifestyle factors, occupational exposure, and increased prevalence of chronic diseases in males may explain this predominance.
The present study demonstrated reduced hemoglobin levels in all patients, with mean hemoglobin value of 8.9 ± 1.4 g/dL. Most patients had moderate anemia. Similar findings were observed by Means et al. [2], who described anemia of chronic disease as predominantly mild to moderate anemia resulting from impaired erythropoiesis and iron restriction secondary to inflammation.
Serum ferritin levels were significantly elevated in the majority of cases included in this study. The mean serum ferritin level was 412 ± 96 ng/mL. Ferritin is not only an indicator of iron storage but also an acute phase reactant whose synthesis increases during inflammatory states [5]. Elevated ferritin levels observed in the present study may therefore reflect both iron sequestration and chronic inflammatory activity. Similar observations were reported by Wang et al. [9], who demonstrated significantly raised ferritin levels in inflammatory disorders and chronic diseases.
Serum iron levels and transferrin saturation were decreased in the present study, while total iron binding capacity (TIBC) was low or normal. These findings are characteristic laboratory features of anemia of chronic disease and occur due to cytokine-mediated iron sequestration and reduced iron availability for erythropoiesis [4]. Cartwright [11] also reported similar biochemical alterations in patients with chronic inflammatory anemia.
Inflammatory markers including ESR and CRP were significantly elevated in the study population. The mean ESR was 54 ± 18 mm/hr and mean CRP level was 22 ± 8 mg/L. Chronic inflammatory states stimulate hepatic production of acute phase reactants including CRP and ferritin through cytokine-mediated pathways [7]. Elevated inflammatory markers observed in the present study indicate persistent inflammatory activity in patients with chronic disease.
A significant positive correlation was observed between serum ferritin and ESR (r = +0.68, p <0.001) as well as serum ferritin and CRP (r = +0.72, p <0.001). These findings suggest that increasing inflammatory activity is associated with elevated ferritin levels in anemia of chronic disease. Similar findings were documented by Kalantar-Zadeh et al. [8], who reported strong association between ferritin levels and inflammatory markers in chronic inflammatory conditions. Increased ferritin synthesis during inflammation is largely mediated by interleukin-6 and hepcidin pathways [3].
Chronic infections constituted the most common underlying etiology in the present study followed by autoimmune disorders and chronic kidney disease. Persistent inflammatory stimulation in these disorders results in continuous cytokine release, impaired iron utilization, and suppression of erythropoiesis [10]. Similar etiological patterns were reported in previous studies evaluating anemia associated with chronic diseases [12].
The findings of the present study emphasize the importance of combined assessment of serum ferritin and inflammatory markers in patients with anemia of chronic disease. Interpretation of ferritin levels without considering inflammatory status may lead to diagnostic confusion, particularly in differentiating ACD from iron deficiency anemia [6]. Simultaneous evaluation of ESR, CRP, serum iron, TIBC, and transferrin saturation significantly improves diagnostic accuracy.
The present study highlights the role of serum ferritin as both a marker of iron metabolism and an indicator of inflammatory activity. Early identification of inflammatory anemia and appropriate management of underlying chronic disorders may help improve patient outcomes and reduce disease-associated morbidity [14,15.
CONCLUSION:
Serum ferritin demonstrates significant positive correlation with inflammatory markers such as ESR and CRP in anemia of chronic disease. Elevated ferritin levels in ACD reflect both altered iron metabolism and inflammatory activity.
Combined evaluation of serum ferritin, ESR, CRP, and iron profile parameters improves diagnostic accuracy and helps differentiate anemia of chronic disease from other forms of anemia. Early recognition of inflammatory status and iron metabolism abnormalities is important for appropriate clinical management.
Limitations of the Study
1. Small sample size.
2. Single-center study.
3. Advanced inflammatory cytokines such as IL-6 and hepcidin were not evaluated.
4. Follow-up assessment after treatment was not performed.
Recommendations
1. Serum ferritin should always be interpreted along with inflammatory markers in chronic disease patients.
2. Assessment of hepcidin and cytokine profile may improve diagnostic precision.
Larger multicentric studies are recommended for better understanding of inflammatory pathways in ACD
REFERENCES:
1. Weiss G, Goodnough LT. Anemia of chronic disease. N Engl J Med. 2005 Mar 10;352(10):1011-23.
2. Means RT Jr. The anemia of infection. Baillieres Best Pract Res Clin Haematol. 2000 Jun;13(2):151-62.
3. Ganz T. Hepcidin and iron regulation, 10 years later. Blood. 2011 Apr 28;117(17):4425-33.
4. Nemeth E, Rivera S, Gabayan V, Keller C, Taudorf S, Pedersen BK, Ganz T. IL-6 mediates hypoferremia of inflammation by inducing the synthesis of the iron regulatory hormone hepcidin. J Clin Invest. 2004 May;113(9):1271-6.
5. Worwood M. Serum ferritin. Crit Rev Clin Lab Sci. 1979;10(2):171-204.
6. Lee GR. The anemia of chronic disease. Semin Hematol. 1983 Apr;20(2):61-80.
7. Gabay C, Kushner I. Acute-phase proteins and other systemic responses to inflammation. N Engl J Med. 1999 Feb 11;340(6):448-54.
8. Kalantar-Zadeh K, Rodriguez RA, Humphreys MH. Association between serum ferritin and measures of inflammation, nutrition and iron in haemodialysis patients. Kidney Int. 2004 Oct;66(4):1791-9.
9. Wang W, Knovich MA, Coffman LG, Torti FM, Torti SV. Serum ferritin: Past, present and future. Biochim Biophys Acta. 2010 Aug;1800(8):760-9.
10. Means RT Jr. Pathogenesis of the anemia of chronic disease: A cytokine-mediated anemia. Stem Cells. 1995 Jul-Aug;13(1):32-7.
11. Cartwright GE. The anemia of chronic disorders. Semin Hematol. 1966 Oct;3(4):351-75.
12. Ferguson BJ, Skikne BS, Simpson KM, Baynes RD, Cook JD. Serum transferrin receptor distinguishes the anemia of chronic disease from iron deficiency anemia. J Lab Clin Med. 1992 Apr;119(4):385-90.
13. Roy CN. Anemia of inflammation. Hematology Am Soc Hematol Educ Program. 2010 Dec 4;2010:276-80.
14. Cullis JO. Diagnosis and management of anaemia of chronic disease: Current status. Br J Haematol. 2011 Jul;154(3):289-300.
15. Weiss G. Iron metabolism in the anemia of chronic disease. Biochim Biophys Acta. 2009 Jul;1790(7):682-93.