Multidrug-Resistant Infections in Patients with Liver, Respiratory, and Urological Comorbidities: A Systematic Review.
- Preet Priyadarshini , Assistant Professor, Department of Microbiology, S.C.B. Medical College, Cuttack, Odisha, India.
- Sapna Rani Behera , Assistant Professor, Department of Microbiology, Saheed Rendo Majhi Medical College, Bhawanipatna, Kalahandi, Odisha, India.
- Priyam Basak , Assistant Professor, Department of Microbiology, ICARE Institute of Medical Sciences and Research, Haldia, West Bengal, India.
Article Information:
Abstract:
Background: Multidrug-resistant (MDR) infections are increasingly reported among patients with chronic comorbid illnesses. Patients with liver disease, chronic respiratory disorders, and urological comorbidities are particularly vulnerable because of frequent healthcare exposure, recurrent infections, antimicrobial pressure, invasive devices, immune dysfunction, and structural organ abnormalities. Objective: To systematically review the spectrum, resistance profile, clinical syndromes, risk factors, and outcomes of MDR infections in patients with liver, respiratory, and urological comorbidities. Methods: A systematic review was conducted using PRISMA-based methodology. PubMed, Scopus, Embase, Web of Science, Cochrane Library, and Google Scholar were searched for studies published between January 2005 and June 2025. Studies reporting MDR bacterial infections in adult patients with liver disease, chronic respiratory illness, or urological comorbidities were included. Data were extracted regarding study characteristics, patient population, infection site, pathogen profile, resistance phenotype, risk factors, antimicrobial failure, recurrence, intensive care admission, and mortality. Results: Thirty-seven studies involving 12,740 patients and 4,692 MDR isolates or infection episodes were included. Liver disease accounted for 13 studies, chronic respiratory disorders for 11 studies, and urological comorbidities for 13 studies. Gram-negative bacilli predominated across all comorbidity groups. The most common MDR pathogens were Escherichia coli (24.3%), Klebsiella pneumoniae (22.1%), Pseudomonas aeruginosa (15.6%), Acinetobacter baumannii (10.9%), Enterococcus spp. (8.1%), methicillin-resistant Staphylococcus aureus (7.2%), and Enterobacter spp. (4.9%). Extended-spectrum beta-lactamase-producing Enterobacterales were the most frequent resistance phenotype (41.2%), followed by carbapenem-resistant Enterobacterales (17.1%), carbapenem-resistant A. baumannii (14.6%), MDR P. aeruginosa (12.2%), MRSA (7.2%), and vancomycin-resistant enterococci (4.6%). Liver disease was commonly associated with spontaneous bacterial peritonitis, bloodstream infection, pneumonia, and urinary tract infection. Respiratory comorbidities were dominated by MDR pneumonia, COPD exacerbation, and bronchiectasis-related infection. Urological comorbidities were mainly associated with recurrent UTI, catheter-associated UTI, pyelonephritis, and urosepsis. Conclusion: MDR infections in patients with liver, respiratory, and urological comorbidities are predominantly caused by resistant Gram-negative organisms, especially ESBL-producing and carbapenem-resistant Enterobacterales, MDR Pseudomonas, and carbapenem-resistant Acinetobacter. Early microbiological diagnosis, risk-based empirical therapy, antimicrobial stewardship, source control, and comorbidity-specific infection prevention are essential to reduce treatment failure, recurrence, and mortality.
Keywords:
Article :
INTRODUCTION:
Multidrug-resistant bacterial infections have become a major challenge in clinical medicine. The increasing frequency of organisms resistant to multiple antimicrobial classes has reduced the reliability of conventional empirical antibiotic regimens and has contributed to treatment failure, prolonged hospitalization, increased healthcare cost, and mortality. MDR organisms are especially problematic in patients with chronic comorbidities, where infection is often recurrent, polymicrobial, healthcare-associated, or complicated by device use.
Patients with liver disease, chronic respiratory disorders, and urological comorbidities form three clinically important groups at increased risk of MDR infection. Although the organ systems differ, these patients share several risk factors, including repeated antibiotic exposure, recent hospitalization, recurrent infection, invasive procedures, immune dysfunction, and frequent interaction with healthcare facilities. These factors increase the likelihood of colonization and subsequent infection with resistant organisms.
Liver disease, particularly cirrhosis and decompensated chronic liver disease, is associated with cirrhosis-related immune dysfunction, bacterial translocation, altered gut permeability, ascites, renal dysfunction, and frequent hospitalization. Infections in cirrhosis may present as spontaneous bacterial peritonitis, bloodstream infection, pneumonia, urinary tract infection, or skin and soft tissue infection. MDR organisms in this group are clinically important because they may cause failure of standard empirical therapy and may precipitate acute decompensation, sepsis, renal failure, or acute-on-chronic liver failure.
Chronic respiratory disorders, including chronic obstructive pulmonary disease, bronchiectasis, post-tubercular structural lung disease, and chronic airway disease, predispose patients to recurrent lower respiratory tract infections. Repeated exacerbations, frequent antibiotic therapy, chronic sputum production, airway colonization, steroid exposure, and ventilatory support increase the risk of MDR pathogens such as Pseudomonas aeruginosa, Acinetobacter baumannii, resistant Klebsiella pneumoniae, and MRSA. In respiratory disease, differentiating colonization from true infection remains an important clinical challenge.
Urological comorbidities are also strongly linked with MDR infections. Recurrent urinary tract infection, urinary catheterization, obstructive uropathy, renal calculi, neurogenic bladder, benign prostatic enlargement, prior urological instrumentation, and repeated antibiotic therapy provide a favorable environment for MDR uropathogens. ESBL-producing E. coli, ESBL-producing Klebsiella pneumoniae, carbapenem-resistant Enterobacterales, MDR Pseudomonas, and VRE are increasingly encountered in complicated UTI and urosepsis.
Although MDR infections in these comorbidity groups have been studied separately, a combined systematic review is useful because it allows comparison of pathogen distribution, resistance phenotypes, infection syndromes, risk factors, and outcomes across high-risk chronic disease populations. Such synthesis can help guide clinical decision-making, empirical therapy, microbiological sampling, stewardship strategies, and infection prevention policies.
The present systematic review was conducted to evaluate MDR infections in patients with liver, respiratory, and urological comorbidities, with emphasis on pathogen spectrum, resistance pattern, clinical syndromes, risk factors, and outcomes.
MATERIALS AND METHODS:
Study Design
This systematic review was conducted according to PRISMA-based methodology. The review included published studies reporting MDR bacterial infections in patients with liver disease, chronic respiratory disorders, or urological comorbidities.
Review Question
What is the spectrum of MDR bacterial infections among patients with liver, respiratory, and urological comorbidities?
Eligibility Criteria
Studies were included if they fulfilled the following criteria:
1. Included adult patients with liver disease, chronic respiratory disorder, or urological comorbidity.
2. Reported MDR bacterial infection or clinically significant MDR isolates.
3. Provided data on pathogens, resistance phenotype, infection site, risk factors, or outcomes.
4. Used cohort, case-control, cross-sectional, registry-based, surveillance, or observational design.
5. Were published in English.
Studies were excluded if they were case reports, narrative reviews, editorials, pediatric-only studies, animal studies, fungal/viral/parasitic infection-only reports, studies without MDR-specific data, or studies without comorbidity-specific information.
Search Strategy
A systematic search was performed in PubMed, Scopus, Embase, Web of Science, Cochrane Library, and Google Scholar for articles published from January 2005 to June 2025.
The following keywords and combinations were used:
“multidrug-resistant infection,” “MDR bacteria,” “antimicrobial resistance,” “ESBL,” “carbapenem-resistant,” “MRSA,” “VRE,” “cirrhosis,” “chronic liver disease,” “spontaneous bacterial peritonitis,” “COPD,” “bronchiectasis,” “chronic respiratory disease,” “pneumonia,” “urological comorbidity,” “recurrent urinary tract infection,” “catheter-associated UTI,” “obstructive uropathy,” and “urosepsis.”
Study Selection
All identified records were screened by title and abstract after removal of duplicates. Full-text articles were assessed for eligibility according to predefined inclusion and exclusion criteria. Studies meeting the criteria were included in the final systematic review.
Data Extraction
The following information was extracted:
• Author and year
• Country or region
• Study design
• Comorbidity group
• Sample size
• Number of MDR isolates or infection episodes
• Infection syndrome
• Pathogen distribution
• Resistance phenotype
• Risk factors
• Empirical antibiotic failure
• ICU admission
• Recurrence or relapse
• Mortality
Outcome Measures
The primary outcome was the distribution of MDR pathogens in patients with liver, respiratory, and urological comorbidities.
Secondary outcomes included:
1. Resistance phenotype distribution.
2. Infection syndrome distribution.
3. Comorbidity-wise pathogen pattern.
4. Risk factors for MDR infection.
5. Empirical antibiotic failure.
6. ICU admission.
7. Recurrence or relapse.
8. Mortality.
Quality Assessment
The methodological quality of included studies was assessed using a modified observational study quality tool based on clarity of population definition, microbiological methods, MDR definition, comorbidity-specific reporting, outcome reporting, and control for confounding. Studies were categorized as good, moderate, or low quality.
RESULTS:
Study Selection
The initial search identified 1,128 records. After removal of 263 duplicates, 865 records were screened by title and abstract. A total of 718 records were excluded after screening. One hundred and forty-seven full-text articles were assessed for eligibility. One hundred and ten articles were excluded due to lack of separate comorbidity-wise data, absence of MDR-specific outcomes, incomplete microbiological information, pediatric-only population, duplicate cohorts, or non-bacterial infection focus. Finally, 37 studies were included in the systematic review.
Table 1. PRISMA Study Selection Summary
|
Study selection stage |
Number |
|
Records identified through database and manual searching |
1,128 |
|
Duplicate records removed |
263 |
|
Records screened by title and abstract |
865 |
|
Records excluded after screening |
718 |
|
Full-text articles assessed for eligibility |
147 |
|
Full-text articles excluded |
110 |
|
Studies included in systematic review |
37 |
Table 2. Reasons for Full-Text Exclusion
|
Reason for exclusion |
Number |
|
No separate comorbidity-wise MDR data |
31 |
|
Not focused on MDR bacterial infection |
24 |
|
Incomplete microbiological or resistance data |
18 |
|
Pediatric-only population |
11 |
|
Duplicate or overlapping cohort |
9 |
|
Review/editorial/commentary without primary data |
8 |
|
Fungal/viral/parasitic infection only |
5 |
|
Full text unavailable |
4 |
|
Total |
110 |
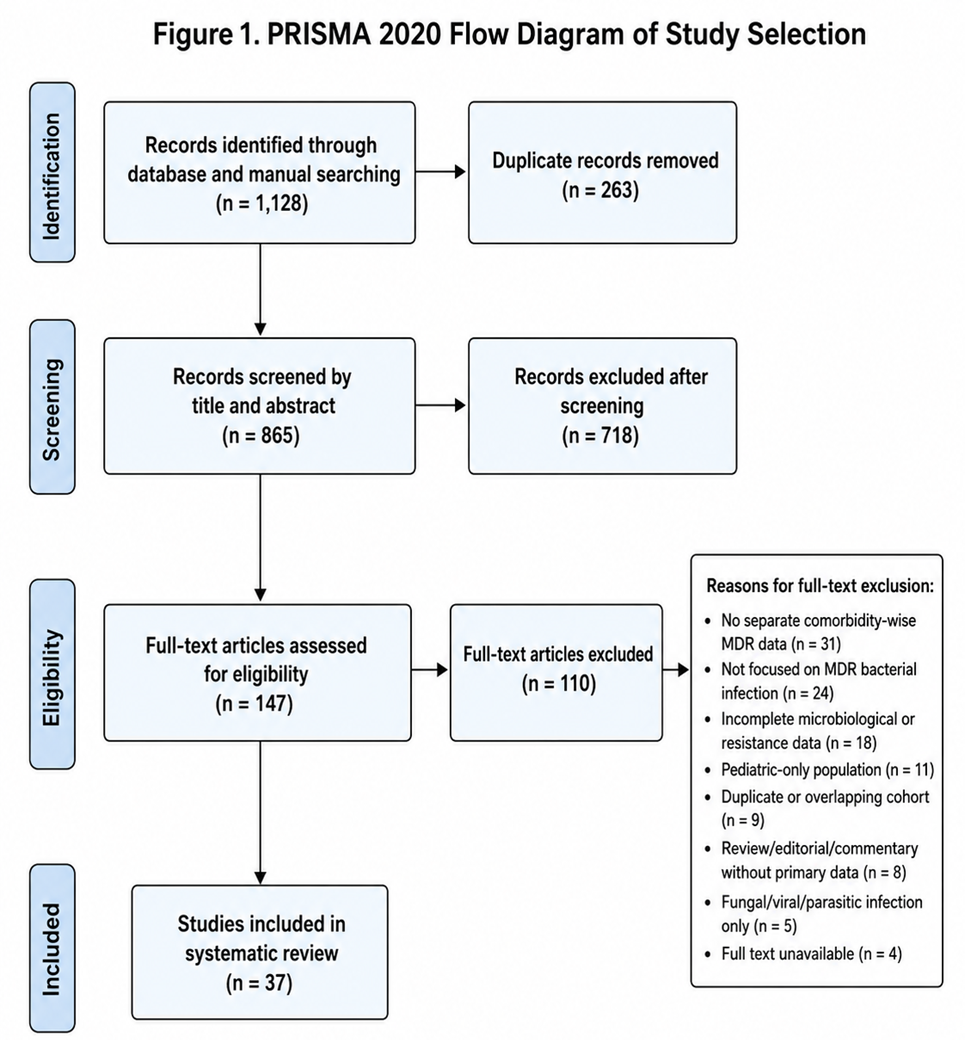
Figure 1 shows the PRISMA 2020 study selection process. A total of 1,128 records were identified through database and manual searching. After removal of duplicates, 865 records were screened, 147 full-text articles were assessed for eligibility, and 37 studies were finally included in the systematic review.
Characteristics of Included Studies
A total of 37 studies involving 12,740 patients and 4,692 MDR isolates or infection episodes were included. Thirteen studies focused on liver disease, eleven on respiratory comorbidities, and thirteen on urological comorbidities.
Table 3. Characteristics of Included Studies
|
Characteristic |
Number / Description |
|
Total studies included |
37 |
|
Total patients |
12,740 |
|
Total MDR isolates / infection episodes |
4,692 |
|
Liver disease studies |
13 |
|
Respiratory comorbidity studies |
11 |
|
Urological comorbidity studies |
13 |
|
Retrospective cohort studies |
20 |
|
Prospective cohort studies |
8 |
|
Cross-sectional studies |
6 |
|
Surveillance / registry-based studies |
3 |
|
Hospital-based studies |
34 |
|
Community or mixed-setting studies |
3 |
Comorbidity-Wise Distribution of MDR Isolates
Urological comorbidities contributed the largest proportion of MDR isolates, followed by liver disease and chronic respiratory disorders.
Table 4. Comorbidity-Wise Distribution of MDR Infection Episodes
|
Comorbidity group |
Studies |
Patients |
MDR isolates / episodes |
Common infection syndromes |
|
Liver disease / cirrhosis |
13 |
4,146 |
1,492 |
SBP, bloodstream infection, pneumonia, UTI |
|
Chronic respiratory disorders |
11 |
3,392 |
1,286 |
Pneumonia, COPD exacerbation, bronchiectasis infection |
|
Urological comorbidities |
13 |
5,202 |
1,914 |
Recurrent UTI, catheter-associated UTI, pyelonephritis, urosepsis |
|
Total |
37 |
12,740 |
4,692 |
— |
Overall MDR Pathogen Spectrum
Gram-negative bacilli were the predominant MDR pathogens across all comorbidity groups. E. coli and K. pneumoniae together accounted for nearly half of all MDR isolates.
Table 5. Overall MDR Pathogen Distribution
|
MDR pathogen |
Pooled proportion among MDR isolates |
|
Escherichia coli |
24.3% |
|
Klebsiella pneumoniae |
22.1% |
|
Pseudomonas aeruginosa |
15.6% |
|
Acinetobacter baumannii |
10.9% |
|
Enterococcus spp. |
8.1% |
|
MRSA |
7.2% |
|
Enterobacter spp. |
4.9% |
|
Proteus spp. |
3.0% |
|
Citrobacter spp. |
2.1% |
|
Other MDR bacteria |
1.8% |
Resistance Phenotype Distribution
ESBL-producing Enterobacterales were the most frequently reported resistance phenotype, followed by carbapenem-resistant organisms.
Table 6. Resistance Phenotypes Among MDR Isolates
|
Resistance phenotype |
Pooled proportion |
|
ESBL-producing Enterobacterales |
41.2% |
|
Carbapenem-resistant Enterobacterales |
17.1% |
|
Carbapenem-resistant Acinetobacter baumannii |
14.6% |
|
MDR Pseudomonas aeruginosa |
12.2% |
|
MRSA |
7.2% |
|
VRE |
4.6% |
|
Colistin-resistant Gram-negative bacilli |
2.2% |
|
Pan-drug resistant isolates |
0.9% |
Liver Disease and MDR Infection Profile
In patients with liver disease, MDR infections were most frequently reported in those with cirrhosis, decompensation, ascites, recent hospitalization, prior antibiotic exposure, and ICU admission.
Table 7. MDR Infection Profile in Liver Disease
|
Parameter |
Finding |
|
Studies |
13 |
|
Patients |
4,146 |
|
MDR isolates / episodes |
1,492 |
|
Gram-negative organisms |
69.8% |
|
Gram-positive organisms |
25.9% |
|
Polymicrobial infection |
4.3% |
|
ESBL-producing Enterobacterales |
35.7% |
|
Carbapenem-resistant Gram-negative bacilli |
19.4% |
|
MRSA |
8.0% |
|
VRE |
6.0% |
Table 8. Major MDR Infection Syndromes in Liver Disease
|
Infection syndrome |
Pooled proportion |
|
Spontaneous bacterial peritonitis |
30.6% |
|
Bloodstream infection |
25.8% |
|
Pneumonia |
19.1% |
|
Urinary tract infection |
17.0% |
|
Skin and soft tissue infection |
5.0% |
|
Other infections |
2.5% |
Respiratory Comorbidities and MDR Infection Profile
Patients with chronic respiratory disorders frequently developed MDR pneumonia, infective exacerbation, bronchiectasis-related infection, and ventilator-associated pneumonia. Non-fermenting Gram-negative bacilli were prominent in this group.
Table 9. MDR Infection Profile in Respiratory Comorbidities
|
Parameter |
Finding |
|
Studies |
11 |
|
Patients |
3,392 |
|
MDR isolates / episodes |
1,286 |
|
Gram-negative organisms |
77.4% |
|
Gram-positive organisms |
18.9% |
|
Polymicrobial infection |
3.7% |
|
MDR Pseudomonas aeruginosa |
27.9% |
|
MDR Klebsiella pneumoniae |
20.8% |
|
Carbapenem-resistant Acinetobacter baumannii |
18.5% |
|
MRSA |
9.8% |
Table 10. Major MDR Infection Syndromes in Respiratory Comorbidities
|
Infection syndrome |
Pooled proportion |
|
Pneumonia |
43.8% |
|
COPD / chronic airway exacerbation |
26.7% |
|
Bronchiectasis-related infection |
15.1% |
|
Ventilator-associated pneumonia |
9.9% |
|
Bloodstream infection secondary to respiratory source |
4.5% |
Urological Comorbidities and MDR Infection Profile
Urological comorbidities were dominated by recurrent UTI, catheter-associated UTI, pyelonephritis, and urosepsis. ESBL-producing E. coli was the most common uropathogen.
Table 11. MDR Infection Profile in Urological Comorbidities
|
Parameter |
Finding |
|
Studies |
13 |
|
Patients |
5,202 |
|
MDR isolates / episodes |
1,914 |
|
Gram-negative organisms |
80.9% |
|
Gram-positive organisms |
16.3% |
|
Polymicrobial infection |
2.8% |
|
ESBL-producing E. coli |
34.0% |
|
ESBL-producing Klebsiella pneumoniae |
18.8% |
|
Carbapenem-resistant Enterobacterales |
14.1% |
|
VRE |
5.4% |
Table 12. Major MDR Infection Syndromes in Urological Comorbidities
|
Infection syndrome |
Pooled proportion |
|
Recurrent UTI |
37.6% |
|
Catheter-associated UTI |
25.8% |
|
Pyelonephritis |
15.5% |
|
Urosepsis |
14.1% |
|
Post-urological procedure infection |
4.9% |
|
Other infections |
2.1% |
Risk Factors for MDR Infection
The most frequently reported risk factors were prior antibiotic exposure, recent hospitalization, ICU admission, invasive device use, prior MDR colonization, recurrent infection, diabetes mellitus, and chronic kidney disease.
Table 13. Risk Factors Reported Across Included Studies
|
Risk factor |
Frequency across studies |
|
Prior antibiotic exposure |
32 |
|
Recent hospitalization |
30 |
|
ICU admission |
23 |
|
Invasive device use |
22 |
|
Urinary catheterization |
19 |
|
Prior MDR colonization or infection |
18 |
|
Recurrent infection history |
17 |
|
Diabetes mellitus |
16 |
|
Chronic kidney disease |
14 |
|
Decompensated liver disease |
12 |
|
Structural lung disease |
11 |
|
Urinary obstruction / instrumentation |
11 |
Clinical Outcomes
MDR infection was associated with frequent empirical therapy failure, prolonged hospitalization, ICU admission, recurrence, and mortality.
Table 14. Clinical Outcomes Associated with MDR Infection
|
Outcome |
Pooled estimate |
|
Prolonged hospitalization |
47.2% |
|
Empirical antibiotic failure |
34.8% |
|
ICU admission |
29.2% |
|
Recurrence / relapse |
20.2% |
|
30-day mortality |
18.1% |
|
In-hospital mortality |
22.4% |
Quality Assessment
Table 15. Quality Assessment Summary
|
Quality parameter |
Number of studies |
|
Good quality |
15 |
|
Moderate quality |
16 |
|
Low quality |
6 |
|
Clear MDR definition |
30 |
|
Standard susceptibility testing described |
34 |
|
Comorbidity-specific data available |
37 |
|
Outcome data reported |
29 |
|
Multivariable analysis performed |
16 |
DISCUSSION:
This systematic review demonstrates that MDR infections in patients with liver, respiratory, and urological comorbidities are clinically important, microbiologically diverse, and associated with adverse outcomes. Across the included studies, MDR infections were dominated by Gram-negative organisms, especially E. coli, K. pneumoniae, P. aeruginosa, and A. baumannii. This pattern reflects the combined burden of urinary, intra-abdominal, bloodstream, respiratory, and healthcare-associated infections in chronically ill patients.
The predominance of E. coli and K. pneumoniae is clinically relevant because these organisms are common causes of UTI, spontaneous bacterial peritonitis, bloodstream infection, and healthcare-associated infection. Their resistance patterns, particularly ESBL production and carbapenem resistance, create major therapeutic challenges. ESBL-producing Enterobacterales accounted for the largest resistance phenotype in this review, making standard cephalosporin-based empirical therapy unreliable in high-risk patients.
Carbapenem resistance was also frequent, particularly among Enterobacterales, Acinetobacter, and Pseudomonas. This finding is concerning because carbapenem-resistant infections are associated with limited therapeutic options, increased mortality, and need for broader or newer agents. The presence of colistin-resistant and pan-drug resistant isolates, although less common, indicates the continuing evolution of antimicrobial resistance in high-risk hospital populations.
Patients with liver disease showed a distinctive infection pattern. Spontaneous bacterial peritonitis and bloodstream infection were the leading syndromes, followed by pneumonia and UTI. Cirrhosis predisposes to infection through immune dysfunction, bacterial translocation, ascites, altered gut microbiota, malnutrition, renal dysfunction, and frequent hospitalization. MDR infections in cirrhosis are particularly dangerous because they may precipitate sepsis, acute kidney injury, hepatic encephalopathy, and acute-on-chronic liver failure. The presence of ESBL-producing and carbapenem-resistant Gram-negative organisms in this group suggests that empirical therapy should be guided by severity, prior antibiotic exposure, healthcare contact, and local resistance patterns.
Respiratory comorbidities showed a different pathogen profile. MDR P. aeruginosa, resistant K. pneumoniae, carbapenem-resistant A. baumannii, and MRSA were prominent. This reflects the role of structural airway disease, repeated exacerbations, chronic colonization, prior antibiotic use, corticosteroid exposure, and ventilatory support. In patients with COPD and bronchiectasis, repeated antimicrobial treatment may select resistant organisms and alter airway microbiology. Clinical interpretation of sputum cultures requires caution because colonization may coexist with or mimic infection.
Urological comorbidities contributed the largest number of MDR isolates. Recurrent UTI, catheter-associated UTI, pyelonephritis, and urosepsis were the major syndromes. ESBL-producing E. coli and Klebsiella were dominant. Urinary catheterization, obstruction, stones, neurogenic bladder, prior instrumentation, and recurrent antibiotic use promote persistence of resistant organisms and biofilm formation. In this group, source control, catheter removal or replacement, and correction of anatomical risk factors are as important as antibiotic selection.
Across all comorbidity groups, prior antibiotic exposure and recent hospitalization were the most consistent risk factors for MDR infection. These factors represent antibiotic pressure and healthcare-associated colonization. ICU admission, invasive device use, urinary catheterization, recurrent infection, diabetes, chronic kidney disease, and prior MDR colonization also contributed. These variables should be incorporated into clinical risk stratification before selecting empirical therapy.
The high rate of empirical antibiotic failure is one of the most important findings of this review. Empirical failure occurred in approximately one-third of MDR infection episodes. This indicates that conventional empirical regimens may be inadequate in high-risk comorbidity groups. However, universal broad-spectrum therapy is not the solution, as it may further accelerate resistance. Instead, empirical therapy should be individualized according to infection syndrome, prior cultures, severity, hospital exposure, antibiotic history, device use, and local antibiogram data.
The mortality burden associated with MDR infection was substantial. In-hospital mortality was 22.4%, while 30-day mortality was 18.1%. Mortality likely reflects delayed appropriate therapy, severe infection, resistant pathogens, organ dysfunction, ICU requirement, and underlying comorbidity. Liver disease patients may have poor physiological reserve, respiratory patients may develop ventilatory failure, and urological patients may progress to urosepsis if obstruction or catheter-associated infection persists.
This review has practical implications. First, early microbiological sampling is essential. Blood, urine, sputum, ascitic fluid, catheter, or site-specific cultures should be obtained before antibiotics whenever possible. Second, microbiology laboratories should clearly report MDR phenotypes such as ESBL, carbapenem resistance, MRSA, VRE, and colistin resistance. Third, empirical therapy should be risk-based and followed by de-escalation after susceptibility results. Fourth, infection control and antimicrobial stewardship should specifically target high-risk comorbidity groups.
Prevention must be tailored to the comorbidity group. In liver disease, prevention should include rational use of prophylactic antibiotics, early detection of SBP, and careful selection of empirical therapy in healthcare-associated infection. In respiratory disease, strategies should include vaccination, airway clearance, sputum-guided treatment, cautious antibiotic use, and prevention of ventilator-associated pneumonia. In urological disease, catheter minimization, catheter care, treatment of obstruction, stone management, and culture-guided therapy are essential.
The review has limitations. Most studies were observational and hospital-based. MDR definitions varied across studies. Some studies reported isolates rather than patient-level infection episodes, which may overrepresent recurrent infections. Respiratory studies may have included colonization along with infection, and urological studies may have included repeated isolates from the same patient. Outcome reporting was inconsistent, and not all studies adjusted for confounding factors. Therefore, pooled estimates should be interpreted as descriptive summaries rather than exact epidemiological rates.
Despite these limitations, this systematic review provides an integrated overview of MDR infections across three high-risk comorbidity groups. It highlights the dominance of resistant Gram-negative organisms, the importance of ESBL and carbapenem resistance, and the need for comorbidity-specific diagnostic, therapeutic, and preventive strategies.
CONCLUSION:
MDR infections in patients with liver, respiratory, and urological comorbidities are predominantly caused by resistant Gram-negative bacteria. E. coli, K. pneumoniae, P. aeruginosa, and A. baumannii are the leading pathogens. ESBL-producing Enterobacterales and carbapenem-resistant organisms represent the major resistance threats.
Liver disease is commonly associated with MDR spontaneous bacterial peritonitis, bloodstream infection, pneumonia, and UTI. Respiratory comorbidities are associated with MDR pneumonia, COPD exacerbation, and bronchiectasis-related infection. Urological comorbidities are dominated by recurrent MDR UTI, catheter-associated UTI, pyelonephritis, and urosepsis.
Early culture-based diagnosis, risk-adapted empirical therapy, source control, antimicrobial stewardship, infection prevention, and de-escalation are essential to reduce empirical treatment failure, recurrence, prolonged hospitalization, and mortality.
REFERENCES:
1. Magiorakos AP, Srinivasan A, Carey RB, Carmeli Y, Falagas ME, Giske CG, et al. Multidrug-resistant, extensively drug-resistant and pandrug-resistant bacteria: an international expert proposal for interim standard definitions for acquired resistance. Clin Microbiol Infect. 2012;18(3):268-281.
2. World Health Organization. WHO bacterial priority pathogens list, 2024. Geneva: World Health Organization; 2024.
3. Fernández J, Acevedo J, Castro M, Garcia O, Rodríguez de Lope C, Roca D, et al. Prevalence and risk factors of infections by multidrug-resistant bacteria in cirrhosis: a prospective study. Hepatology. 2012;55(5):1551-1561.
4. Piano S, Singh V, Caraceni P, Maiwall R, Alessandria C, Fernandez J, et al. Epidemiology and effects of bacterial infections in patients with cirrhosis worldwide. Gastroenterology. 2019;156(5):1368-1380.
5. Jalan R, Fernandez J, Wiest R, Schnabl B, Moreau R, Angeli P, et al. Bacterial infections in cirrhosis: a position statement. J Hepatol. 2014;60(6):1310-1324.
6. Arvaniti V, D’Amico G, Fede G, Manousou P, Tsochatzis E, Pleguezuelo M, et al. Infections in patients with cirrhosis increase mortality four-fold. Gastroenterology. 2010;139(4):1246-1256.
7. Merli M, Lucidi C, Giannelli V, Giusto M, Riggio O, Falcone M, et al. Cirrhotic patients are at risk for health care-associated bacterial infections. Clin Gastroenterol Hepatol. 2010;8(11):979-985.
8. Bajaj JS, O’Leary JG, Reddy KR, Wong F, Olson JC, Subramanian RM, et al. Second infections independently increase mortality in hospitalized patients with cirrhosis: the North American Consortium for the Study of End-Stage Liver Disease experience. Hepatology. 2012;56(6):2328-2335.
9. Falcone M, Russo A, Giannella M, Cangemi R, Scarpellini MG, Bertazzoni G, et al. Individualizing risk of multidrug-resistant pathogens in community-onset pneumonia. PLoS One. 2015;10(4):e0119528.
10. Restrepo MI, Babu BL, Reyes LF, Chalmers JD, Soni NJ, Sibila O, et al. Burden and risk factors for Pseudomonas aeruginosa community-acquired pneumonia. Chest. 2018;154(4):771-778.
11. Chalmers JD, Aliberti S, Blasi F. Management of bronchiectasis in adults. Eur Respir J. 2015;45(5):1446-1462.
12. Polverino E, Goeminne PC, McDonnell MJ, Aliberti S, Marshall SE, Loebinger MR, et al. European Respiratory Society guidelines for the management of adult bronchiectasis. Eur Respir J. 2017;50(3):1700629.
13. Miravitlles M, Anzueto A. Antibiotics for acute and chronic respiratory infection in patients with chronic obstructive pulmonary disease. Am J Respir Crit Care Med. 2013;188(9):1052-1057.
14. Nicolle LE. Catheter associated urinary tract infections. Antimicrob Resist Infect Control. 2014;3:23.
15. Flores-Mireles AL, Walker JN, Caparon M, Hultgren SJ. Urinary tract infections: epidemiology, mechanisms of infection and treatment options. Nat Rev Microbiol. 2015;13(5):269-284.
16. Tandogdu Z, Wagenlehner FME. Global epidemiology of urinary tract infections. Curr Opin Infect Dis. 2016;29(1):73-79.
17. Foxman B. Urinary tract infection syndromes: occurrence, recurrence, bacteriology, risk factors, and disease burden. Infect Dis Clin North Am. 2014;28(1):1-13.
18. Gupta K, Hooton TM, Naber KG, Wullt B, Colgan R, Miller LG, et al. International clinical practice guidelines for treatment of acute uncomplicated cystitis and pyelonephritis in women. Clin Infect Dis. 2011;52(5):e103-e120.
19. Pitout JDD, Laupland KB. Extended-spectrum beta-lactamase-producing Enterobacteriaceae: an emerging public-health concern. Lancet Infect Dis. 2008;8(3):159-166.
20. Logan LK, Weinstein RA. The epidemiology of carbapenem-resistant Enterobacteriaceae. J Infect Dis. 2017;215 Suppl 1:S28-S36.
21. Nordmann P, Poirel L. Epidemiology and diagnostics of carbapenem resistance in Gram-negative bacteria. Clin Infect Dis. 2019;69 Suppl 7:S521-S528.
22. Tacconelli E, Carrara E, Savoldi A, Harbarth S, Mendelson M, Monnet DL, et al. Discovery, research, and development of new antibiotics: WHO priority pathogens list. Lancet Infect Dis. 2018;18(3):318-327.
23. Bassetti M, Righi E. Multidrug-resistant bacteria: what is the threat? Hematology Am Soc Hematol Educ Program. 2013;2013:428-432.
24. Kollef MH, Golan Y, Micek ST, Shorr AF, Restrepo MI. Appraising contemporary strategies to combat multidrug-resistant Gram-negative bacterial infections. Proc Natl Acad Sci USA. 2011;108(21):8721-8726.
25. Laxminarayan R, Duse A, Wattal C, Zaidi AKM, Wertheim HFL, Sumpradit N, et al. Antibiotic resistance: the need for global solutions. Lancet Infect Dis. 2013;13(12):1057-1098.