AN OBSERVATIONAL STUDY OF SERUM URIC ACID AS METABOLIC MARKER IN ACUTE CORONARY SYNDROME.
- Mohd Quamre Azam , Senior Resident, Department of Medicine, ESIC Medical College and Hospital, Sector-24, Noida, Uttar Pradesh, India.
- Kapil Kumar Verma , Associate Professor and Head, Department of Medicine, ESIC Medical College and Hospital, Ahmedabad, Gujarat, India.
- Vijay Kumar Malviya , Professor and Head, Department of Medicine, ESIC Medical College and Hospital, Indore, Madhya Pradesh, India.
Article Information:
Abstract:
Background: Acute coronary syndrome (ACS) remains a major cause of cardiovascular morbidity and mortality worldwide. Serum uric acid, the end product of purine metabolism, has been implicated in oxidative stress, endothelial dysfunction, inflammation, and atherosclerosis. Increasing evidence suggests that elevated serum uric acid levels may reflect the metabolic disturbances associated with myocardial ischemia and injury. The present study was undertaken to evaluate the role of serum uric acid as a metabolic marker in patients with acute coronary syndrome. Methods: This prospective observational study was conducted at ESIC Model Hospital and Occupational Disease Centre, Indore, Madhya Pradesh, from May 2023 to April 2024. A total of 220 adult patients diagnosed with acute coronary syndrome were enrolled. Detailed clinical evaluation, electrocardiography, echocardiography, and laboratory investigations including serum uric acid estimation were performed. Hyperuricemia was defined as serum uric acid levels >7 mg/dL in males and >6 mg/dL in females. Clinical severity was assessed using the Killip classification. Statistical analysis was performed using SPSS version 21.0, and a p-value <0.05 was considered statistically significant. Results: The mean age of the study population was 61.2 ± 9.2 years, and 68.2% of patients were male. The mean serum uric acid level was 7.52 ± 2.11 mg/dL, and hyperuricemia was present in 39.1% of patients. ST-segment elevation myocardial infarction constituted 90.0% of ACS presentations. According to Killip classification, 49.1% of patients belonged to Class I, 38.6% to Class II, 5.9% to Class III, and 6.4% to Class IV. A significant association was observed between hyperuricemia and Killip class (p=0.0001). The prevalence of hyperuricemia increased progressively from 28.7% in Killip Class I to 100% in Killip Class IV. Mean serum uric acid levels also increased significantly with worsening Killip class, from 5.05 ± 1.33 mg/dL in Class I to 11.20 ± 0.09 mg/dL in Class IV (p=0.0001). Conclusions: Serum uric acid levels are significantly associated with the clinical severity of acute coronary syndrome. Both the prevalence of hyperuricemia and mean serum uric acid concentrations increase with worsening Killip class. These findings suggest that serum uric acid may serve as a simple, inexpensive, and readily available metabolic marker for assessing disease severity in patients presenting with acute coronary syndrome.
Keywords:
Article :
INTRODUCTION:
Acute coronary syndrome (ACS) remains one of the leading causes of morbidity and mortality worldwide and represents a major public health challenge. ACS encompasses a spectrum of clinical conditions resulting from acute myocardial ischemia, including unstable angina pectoris (UAP), ST-segment elevation myocardial infarction (STEMI), and non-ST-segment elevation myocardial infarction (NSTEMI). It is characterized by chest pain, electrocardiographic changes, and varying degrees of myocardial injury or necrosis. The current clinical definition of myocardial infarction requires evidence of myocardial ischemia in association with elevated cardiac biomarkers, reflecting myocardial damage. [1,2] Despite advances in diagnostic and therapeutic strategies, early risk stratification and prognostic assessment remain crucial for improving outcomes in patients with ACS.
Numerous biomarkers have been investigated to predict disease severity and prognosis in ACS. However, no single marker has demonstrated complete reliability in identifying patients at increased risk of adverse cardiovascular events. In recent years, serum uric acid (SUA) has emerged as a potential metabolic marker associated with cardiovascular diseases and adverse cardiac outcomes. [3,4]
Uric acid is the final product of purine metabolism in humans, and its serum concentration is influenced by dietary intake, cellular turnover, and renal excretion. Elevated serum uric acid levels, known as hyperuricemia, have been associated with several cardiovascular risk factors, including hypertension, diabetes mellitus, dyslipidemia, obesity, and metabolic syndrome. [5-7] Growing evidence suggests that uric acid contributes to cardiovascular pathology through multiple mechanisms, including oxidative stress, endothelial dysfunction, inflammation, and promotion of atherosclerosis. [8,9]
In the setting of ACS, serum uric acid levels may increase due to enhanced purine degradation and release from ischemic and necrotic myocardial tissue. Elevated SUA may therefore reflect the extent of myocardial injury and metabolic disturbance. Furthermore, uric acid-mediated oxidative and inflammatory responses may aggravate myocardial dysfunction and contribute to complications such as heart failure, arrhythmias, and cardiogenic shock. [10-11]
Given these observations, serum uric acid may serve as a simple, inexpensive, and readily available metabolic marker for assessing disease severity and prognosis in ACS. Therefore, the present study was undertaken to evaluate serum uric acid levels and their association with clinical outcomes in patients presenting with acute coronary syndrome.
MATERIALS AND METHODS:
This prospective observational study was conducted in the Department of Medicine at ESIC Model Hospital and Occupational Disease Centre, Indore, Madhya Pradesh, India, between May 2023 and April 2024. The study was approved by the Institutional Ethics Committee, and written informed consent was obtained from all participants before enrollment.
A total of 220 consecutive adult patients diagnosed with acute coronary syndrome (ACS) were included in the study. ACS was diagnosed based on the presence of angina or angina-equivalent symptoms in association with electrocardiographic changes suggestive of myocardial ischemia and/or elevated cardiac biomarkers consistent with current diagnostic criteria.
Inclusion and Exclusion Criteria
Patients aged 18 years or older presenting with acute coronary syndrome, including ST-segment elevation myocardial infarction (STEMI) and non-ST-segment elevation myocardial infarction (NSTEMI), were eligible for inclusion.
Patients receiving uricosuric medications or drugs known to alter uric acid metabolism, those with acute kidney injury, chronic kidney disease, known gout, active malignancy, previous history of ischemic heart disease on aspirin therapy, chronic alcoholism, and patients younger than 18 years were excluded from the study.
Clinical Assessment and Data Collection
A detailed clinical history was obtained from all participants, including demographic characteristics, cardiovascular risk factors, smoking status, hypertension, diabetes mellitus, dyslipidemia, and medication history. Clinical examination findings and vital parameters were recorded at admission.
Presenting symptoms including chest pain, sweating, dyspnea, palpitations, syncope, and other angina-equivalent symptoms were documented. Electrocardiography was performed in all patients at admission and repeated whenever clinically indicated. Echocardiographic evaluation was carried out to assess left ventricular function and determine left ventricular ejection fraction (LVEF).
Laboratory investigations included serum creatinine, fasting lipid profile, random blood glucose, serum electrolytes, cardiac biomarkers, and serum uric acid levels.
Estimation of Serum Uric Acid
Venous blood samples were collected immediately after hospital admission and analyzed in the central laboratory. Serum uric acid estimation was performed using the enzymatic uricase method on an automated analyzer. Hyperuricemia was defined as serum uric acid levels >7.0 mg/dL in males and >6.0 mg/dL in females.
Assessment of Clinical Severity
The severity of acute coronary syndrome was assessed using the Killip classification. Patients were categorized as:
• Killip Class I: No clinical signs of heart failure.
• Killip Class II: Presence of rales, S3 gallop, or elevated jugular venous pressure.
• Killip Class III: Acute pulmonary edema.
• Killip Class IV: Cardiogenic shock or systolic blood pressure <90 mmHg with evidence of peripheral hypoperfusion.
Study Outcome Measures
The primary objective of the study was to evaluate serum uric acid levels in patients with acute coronary syndrome and determine their association with disease severity. The relationship between hyperuricemia, serum uric acid levels, and Killip classification was analyzed to assess the role of serum uric acid as a metabolic marker in ACS.
Statistical Analysis
Data were entered into Microsoft Excel and analyzed using Statistical Package for the Social Sciences (SPSS) software version 21.0 (IBM Corp., Chicago, IL, USA). Continuous variables were expressed as mean ± standard deviation (SD), whereas categorical variables were presented as frequencies and percentages. Comparisons between categorical variables were performed using the chi-square test. Differences in mean serum uric acid levels across Killip classes were assessed using one-way analysis of variance (ANOVA). A p-value <0.05 was considered statistically significant.
RESULTS:
A total of 220 patients with acute coronary syndrome (ACS) were included in the study. The mean age of the study population was 61.2 ± 9.2 years (range: 39–78 years), with 51.8% of patients aged >60 years. Males constituted 68.2% of the study population. Smoking (44.4%), diabetes mellitus (35.9%), hypertension (29.1%), and dyslipidemia (25.9%) were the major cardiovascular risk factors identified among the study participants (Table 1).
Table 1. Baseline demographic characteristics and cardiovascular risk factors of study participants
|
Variable |
Value |
|
Age (years), Mean ± SD |
61.2 ± 9.2 |
|
Age ≤60 years, n (%) |
106 (48.2) |
|
Age >60 years, n (%) |
114 (51.8) |
|
Male, n (%) |
150 (68.2) |
|
Female, n (%) |
70 (31.8) |
|
Hypertension, n (%) |
64 (29.1) |
|
Diabetes mellitus, n (%) |
79 (35.9) |
|
Dyslipidemia, n (%) |
57 (25.9) |
|
Smoking, n (%) |
98 (44.4) |
Chest pain was the predominant presenting symptom and was reported by 95.9% of patients, followed by sweating (67.8%), restlessness (61.4%), dyspnea (52.3%), and palpitations (30.9%). The mean serum uric acid level was 7.52 ± 2.11 mg/dL, while the mean left ventricular ejection fraction was 38.3 ± 8.5%. Other laboratory parameters are summarized in Table 2.
Table 2. Clinical presentation and laboratory characteristics of study participants
|
Variable |
Value |
|
Chest pain, n (%) |
211 (95.9) |
|
Sweating, n (%) |
149 (67.8) |
|
Restlessness (Ghabrahat), n (%) |
135 (61.4) |
|
Dyspnea, n (%) |
115 (52.3) |
|
Palpitations, n (%) |
68 (30.9) |
|
Syncope, n (%) |
30 (13.6) |
|
Serum creatinine (mg/dL), Mean ± SD |
1.15 ± 0.43 |
|
Total cholesterol (mg/dL), Mean ± SD |
187.12 ± 40.33 |
|
HDL cholesterol (mg/dL), Mean ± SD |
37.70 ± 8.30 |
|
LDL cholesterol (mg/dL), Mean ± SD |
109.24 ± 34.90 |
|
Random blood sugar (mg/dL), Mean ± SD |
162.18 ± 69.10 |
|
Serum sodium (mEq/L), Mean ± SD |
133.4 ± 4.54 |
|
Serum uric acid (mg/dL), Mean ± SD |
7.52 ± 2.11 |
|
LVEF (%), Mean ± SD |
38.3 ± 8.49 |
Regarding ACS subtype, ST-segment elevation myocardial infarction (STEMI) was observed in 198 (90.0%) patients, while 22 (10.0%) patients had NSTEMI. Anterior wall myocardial infarction was the most common infarct location (43.6%), followed by inferior wall myocardial infarction (32.7%) (Table 3).
Table 3. Distribution according to ACS type and infarct location
|
Variable |
Frequency (%) |
|
Type of ACS |
|
|
STEMI |
198 (90.0) |
|
NSTEMI |
22 (10.0) |
|
Site of Myocardial Infarction |
|
|
Anterior wall MI |
96 (43.6) |
|
Inferior wall MI |
72 (32.7) |
|
Anterolateral wall MI |
37 (16.8) |
|
Lateral wall MI |
10 (4.5) |
|
Anteroseptal wall MI |
5 (2.3) |
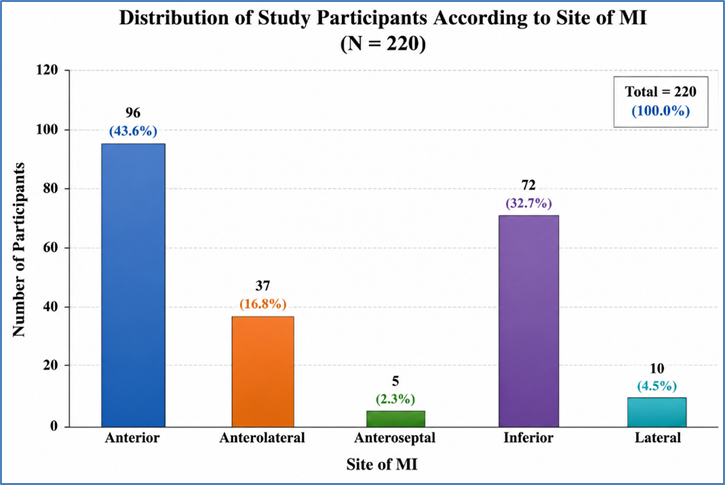
Figure 1: Distribution of study participants according to site of MI
Hyperuricemia was present in 86 (39.1%) patients, while 134 (60.9%) had normal serum uric acid levels. Based on Killip classification, 108 (49.1%) patients belonged to Class I, 85 (38.6%) to Class II, 13 (5.9%) to Class III, and 14 (6.4%) to Class IV (Table 4).
Table 4. Distribution of hyperuricemia and Killip classification
|
Variable |
Frequency (%) |
|
Hyperuricemia |
|
|
Present |
86 (39.1) |
|
Absent |
134 (60.9) |
|
Killip Classification |
|
|
Class I |
108 (49.1) |
|
Class II |
85 (38.6) |
|
Class III |
13 (5.9) |
|
Class IV |
14 (6.4) |
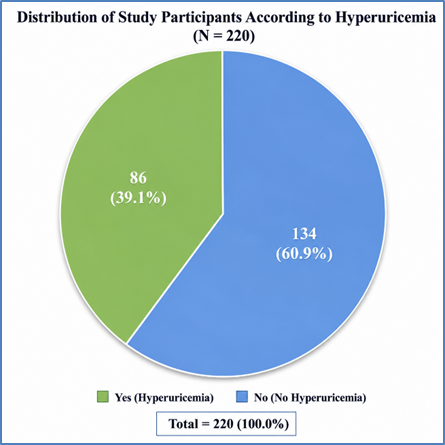
Figure 2: Distribution of study participants according to hyperuricemia:
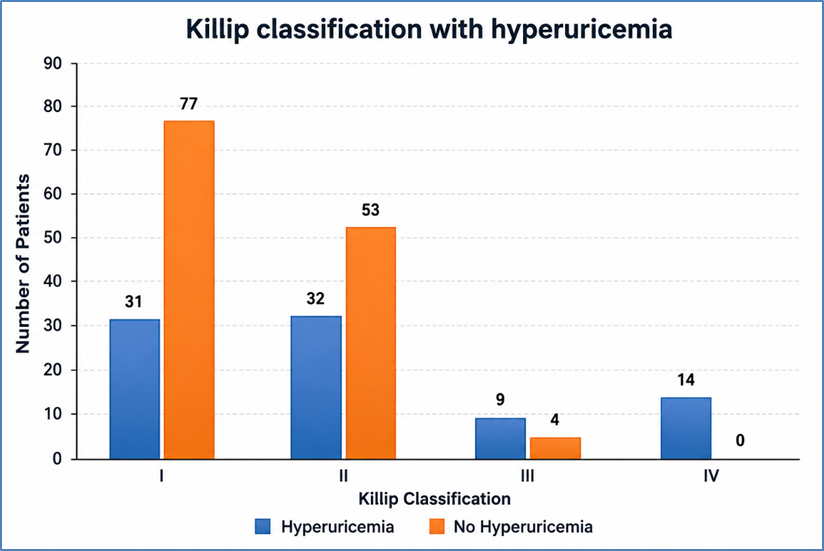
Figure 3: Distribution of study participants according to Killip classifications
A significant association was observed between hyperuricemia and Killip class (p=0.0001). The prevalence of hyperuricemia increased progressively with worsening Killip class, ranging from 28.7% in Killip Class I to 100% in Killip Class IV (Table 5).
Table 5. Association between hyperuricemia and Killip classification
|
Killip Class |
Hyperuricemia n (%) |
No Hyperuricemia n (%) |
P value |
|
I (n=108) |
31 (28.7) |
77 (71.3) |
p = 0.0001 |
|
II (n=85) |
32 (37.6) |
53 (62.4) |
|
|
III (n=13) |
9 (69.2) |
4 (30.8) |
|
|
IV (n=14) |
14 (100.0) |
0 (0.0) |
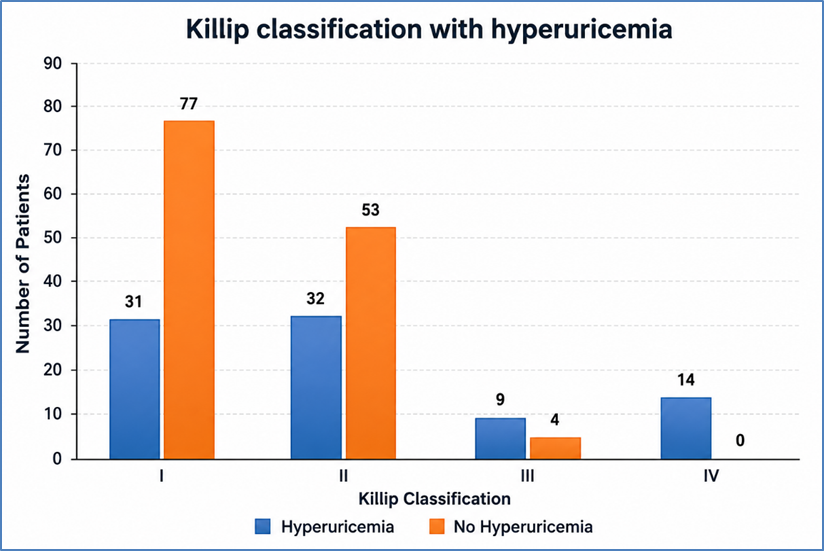
Figure 4: Comparison of Killip classification with hyperuricemia.
Mean serum uric acid levels demonstrated a significant stepwise increase with increasing severity of heart failure. Patients in Killip Class I had a mean serum uric acid level of 5.05 ± 1.33 mg/dL compared with 11.20 ± 0.09 mg/dL among those in Killip Class IV (p=0.0001) (Table 6).
Table 6. Serum uric acid levels according to Killip classification
|
Killip Class |
Mean Serum Uric Acid (mg/dL) |
SD |
P value |
|
I |
5.05 |
1.33 |
p = 0.0001 |
|
II |
6.17 |
1.78 |
|
|
III |
8.17 |
3.31 |
|
|
IV |
11.20 |
0.09 |
DISCUSSION:
Acute coronary syndrome (ACS) remains a major cause of cardiovascular morbidity and mortality worldwide. Identification of simple and reliable biomarkers that reflect disease severity is important for improving clinical assessment and risk stratification. Serum uric acid, the final product of purine metabolism, has been increasingly recognized as a marker of oxidative stress, endothelial dysfunction, inflammation, and myocardial ischemia.
The mean age of patients in the present study was 61.2 ± 9.2 years, with a predominance of patients above 60 years of age. Similar findings were reported by Madan VD et al. (2011) [12] and Tang Q et al. (2011) [13], who observed that ACS predominantly affects older individuals. Male patients constituted 68.2% of the study population, which is consistent with previous reports demonstrating a higher prevalence of ACS among men.[12]
Traditional cardiovascular risk factors were common among study participants. Smoking was observed in 44.4% of patients, diabetes mellitus in 35.9%, hypertension in 29.1%, and dyslipidemia in 25.9%. These findings are in agreement with previous studies highlighting the contribution of conventional risk factors to the development of coronary artery disease and ACS.[14]
Chest pain was the predominant presenting symptom, followed by sweating, restlessness, dyspnea, and palpitations. Similar observations were reported by Choi JS et al. (2017) [15]. Regarding ACS subtype, STEMI constituted 90% of cases, while NSTEMI accounted for only 10%. Anterior wall myocardial infarction was the most common infarct location, followed by inferior wall myocardial infarction. Comparable findings were reported by Adhikari G et al. (2018) [16].
A key finding of the present study was the high prevalence of hyperuricemia among ACS patients. Hyperuricemia was observed in 39.1% of patients, and the mean serum uric acid level was 7.52 ± 2.11 mg/dL. Elevated uric acid levels during ACS may result from increased purine degradation secondary to myocardial ischemia and enhanced xanthine oxidase activity, leading to oxidative stress and endothelial injury.
The findings of the present study are supported by Sarna MK et al. (2025) [1], who demonstrated a significant association between elevated serum uric acid levels and acute myocardial infarction in a case-control study involving 320 participants. Similarly, Choi JS et al. (2017) [15], Rathore A et al. (2023) [17], and Sharmila M et al. (2023) [18] reported significantly higher serum uric acid levels among ACS patients and showed an association with disease severity. Feng H et al. (2022) [19] further demonstrated that hyperuricemia was associated with more extensive coronary artery disease and greater clinical severity.
The most important observation in the present study was the significant association between serum uric acid levels and Killip classification. Hyperuricemia increased progressively from 28.7% in Killip Class I to 100% in Killip Class IV. Similarly, mean serum uric acid levels increased from 5.05 ± 1.33 mg/dL in Class I to 11.20 ± 0.09 mg/dL in Class IV (p=0.0001). These findings indicate that higher uric acid levels are associated with worsening clinical severity.
Comparable results have been reported by Kumar N et al. (2020) [20], who observed a progressive rise in serum uric acid levels across Killip classes. Similar associations between elevated uric acid levels and advanced Killip class were also reported by Shanker D et al. (2023) [21], Rathore A et al. (2023) [17], and Sharmila M et al. (2023) [18]. George J et al. (2019) [22] demonstrated an association between hyperuricemia and the extent of coronary artery disease, while Marak AF et al. (2019) [23] reported a higher incidence of cardiovascular complications among hyperuricemic ACS patients.
The progressive increase in serum uric acid levels with worsening Killip class may reflect greater myocardial ischemia, increased tissue hypoxia, enhanced purine metabolism, and heightened oxidative stress. Thus, elevated serum uric acid appears to reflect the metabolic disturbances associated with severe ACS.
Although Bagheri KR et al. (2022) [24] and Lin Y et al. (2021) [25] reported less consistent findings regarding the prognostic significance of uric acid, the majority of available evidence supports a positive association between elevated serum uric acid levels and disease severity.
Serum uric acid is inexpensive, widely available, and routinely measured in clinical practice. The significant association observed between serum uric acid levels and Killip classification suggests that it may serve as a useful metabolic marker for assessing disease severity in patients with ACS. Although limited by its single-center design and lack of serial uric acid measurements, the study demonstrates that hyperuricemia is common in ACS and correlates closely with worsening clinical status.
CONCLUSION:
Elevated serum uric acid levels were commonly observed among patients with acute coronary syndrome and were significantly associated with increasing clinical severity. Both the prevalence of hyperuricemia and mean serum uric acid concentrations increased progressively across Killip classes, suggesting a close relationship between serum uric acid and the extent of metabolic and hemodynamic impairment. These findings indicate that serum uric acid reflects the underlying pathophysiological changes accompanying myocardial ischemia and ventricular dysfunction. Owing to its low cost, widespread availability, and ease of estimation, serum uric acid may serve as a valuable metabolic marker for assessing disease severity and complement routine clinical evaluation in patients with acute coronary syndrome.
REFERENCES:
1. Sarna MK, Godara R, Pahadia MR, Goel N, Rijhwani P, Lakhotia M, Aggarwal A, Singh S, Sarna S. Study of Relationship of Serum Uric Acid in Acute Myocardial Infarction. Journal of Contemporary Clinical Practice. 2025 Jul;11(7):141-146.
2. Thakur CP, Bhattacharjee K, Das D. Understanding the role of serum uric acid as a prognostic marker in acute coronary syndrome: a hospital based study. J. Evid. Based Med. Healthc. 2018; 5(11), 986-990.
3. Scharf RE. Platelet signaling in primary haemostasis and arterial thrombus formation: Part 1. Hamostaseologie. 2018;38(4):203-210.
4. Mohan S, Gu S, Parikh A, Radhakrishnan J. Prevalence of hyponatremia and association with mortality: results from NHANES. Am J Med. 2013;126(12):1127-1137.e1.
5. Nadkar MY, Jain VI. Serum uric acid in acute myocardial infarction. J Assoc Physicians India. 2008;56:759-762.
6. Anker SD, Doehner W, Rauchhaus M, et al. Uric acid and survival in chronic heart failure: validation and application in metabolic, functional, and haemodynamic staging. Circulation. 2003;107:1991-1997.
7. Ochiai ME, Barretto ACP, Oliveira MT Jr, Munhoz RT, Morgado PC, Ramires JAF. Uric acid renal excretion and renal insufficiency in decompensated severe heart failure. Eur J Heart Fail. 2005;7(4):468-474.
8. Festa A, Haffner SM. Inflammation and cardiovascular disease in patients with diabetes: lessons from the Diabetes Control and Complications Trial. Circulation. 1998;97(24):2446-2448.
9. Hare JM, Johnson RJ. Uric acid predicts clinical outcomes in heart failure: insights regarding the role of xanthine oxidase and uric acid in disease pathophysiology. Circulation. 2003;107(15):1951-1953.
10. Farquharson CA, Butler R, Hill A, Belch JJF, Struthers AD. Allopurinol improves endothelial dysfunction in chronic heart failure. Circulation. 2002;106(2):221-226.
11. Anker SD, Doehner W, Rauchhaus M, et al. Uric acid and survival in chronic heart failure: validation and application in metabolic, functional, and haemodynamic staging. Circulation. 2003;107:1991-1997
12. Madan VD, Novak E, Rich MW. Impact of change in serum uric acid concentration on mortality in patients hospitalized with heart failure and hyponatremia. Circ Heart Fail. 2011;4(5):637-643.
13. Tang Q, Hua Q. Relationship between uric acid and in-hospital outcomes in Chinese patients with ST-elevation myocardial infarction. Intern Med. 2011;50(9):969-974.
14. Ibrahim FY, Qasim SE. The relation between serum uric acid and liver function tests in patients with acute coronary syndrome in Tikrit Teaching Hospital. Int J Adv Res Biol Sci. 2018;5(10):1-28.
15. Choi JS, Kim CS, Bae EH, et al. Prognostic impact of hyponatremia occurring at various time points during hospitalization on mortality in patients with acute myocardial infarction. Medicine (Baltimore). 2017;96(23):e7023.
16. Adhikari G, Agrawal A, Chhetri M, Baral D. Clinical profile of patients presenting with acute myocardial infarction in a tertiary care centre. Int J Adv Med. 2018;5(2):228-233
17. Rathore A, Tank L, Gupta D. Role of serum uric acid in acute myocardial infarction as a prognostic marker in a tertiary care center of South-Eastern Rajasthan. MGM J Med Sci. 2023;10(2):303-308.
18. Sharmila M, Bose P, Aparna SK, Kumar M. Serum uric acid level as an early prognostic indicator in patients with acute coronary syndrome. Int J Acad Med Pharm. 2023;5(4):1-4.
19. Feng H, Pan H, Yao W. Uric acid levels are associated with severity and mortality in patients with acute coronary syndrome. STE Medicine. 2022;3(3):e131.
20. Kumar N, Kumar H, Kumar V, Nayyer PS. A study of the serum uric acid level as prognostic indicator in acute myocardial infarction. J Assoc Physicians India. 2020;68(2):31-34
21. Shanker D, Gupta V. Prognostic role of serum uric acid in acute myocardial infarction: a prospective study. Int J Contemp Med Res. 2023;10(4).
22. George J, Kataria SP, Isser HS. Correlation of serum uric acid with risk factors and severity of coronary artery disease in acute coronary syndrome. Int J Contemp Med Surg Radiol. 2019;4(4):D107-D112.
23. Marak AF, Thongam N, Hijam D, Devi OP, Singh SR, Taruni N. Serum uric acid in acute coronary syndromes. Int J Contemp Med Res. 2019;6(3):C1-C5.
24. Bagheri RK, Najafi MN, Ahmadi M, Saberi M, Maleki M, Baradaran Rahimi V. Investigation of the association between serum uric acid levels and HEART risk score in patients with acute coronary syndrome. Physiol Rep. 2022;10(22):e15513.
25. Lin Y, Hidru TH, Fan R, Gao J, Li H, Yang X, Xia Y. The relationship between serum uric acid at different concentrations of lipid indices and the risk of myocardial revascularization in patients with acute coronary syndrome: a retrospective analysis. Front Cardiovasc Med. 2021;8:732715.