Cytohistopathological Correlation of Image-Guided Fine-Needle Aspiration Cytology in Intra-Abdominal Lesions: A Retrospective and Prospective Study.
- Manjula R , Assistant Professor, Department of Pathology, Belgaum Institute of Medical Sciences, Belgaum
- Aditya.S , Consultant Pathologist, Department of Pathology
- Aparna K , Consultant Pathologist, Department of Pathology
Article Information:
Abstract:
Background: Image-guided fine-needle aspiration cytology is a rapid and minimally invasive method for evaluating deep-seated intra-abdominal lesions. It can provide an early diagnosis and help distinguish benign, inflammatory and malignant lesions without the need for major surgical procedures. Aim: To evaluate the cytomorphological spectrum of intra-abdominal lesions diagnosed by image-guided fine-needle aspiration cytology and assess its diagnostic performance through cytohistopathological correlation. Materials and Methods: This hospital-based retrospective and prospective study was conducted in the Department of Pathology, Goa Medical College and Hospital, from 2010 to 2017. A total of 660 intra-abdominal lesions were sampled under ultrasonographic or computed tomographic guidance using a 22-gauge needle. Smears were stained with haematoxylin and eosin and May–Grünwald–Giemsa stains. Cytological findings were classified as benign, malignant or inconclusive. Histopathological correlation was performed in cases with available biopsy or surgical specimens. Results: Of the 660 patients, 392 (59.39%) were male and 268 (40.61%) were female. The 51–60-year age group was most frequently affected. Computed tomography guided 427 procedures (64.70%), while ultrasonography guided 233 procedures (35.30%). The liver was the most commonly sampled organ, accounting for 307 cases (46.52%). A definitive cytological diagnosis was obtained in 477 cases (72.27%). Malignant lesions accounted for 342 cases (51.82%), benign lesions for 135 cases (20.45%) and inconclusive aspirates for 183 cases (27.73%). Conclusion: Image-guided FNAC is a safe, rapid and reliable diagnostic method for intra-abdominal lesions. It provides high diagnostic accuracy, particularly for malignant lesions, and can reduce the need for more invasive procedures when interpreted with clinical and radiological findings.
Keywords:
Article :
INTRODUCTION:
Intra-abdominal lesions include a wide and diverse group of neoplastic, inflammatory, infective and cystic conditions involving the liver, gallbladder, pancreas, spleen, kidneys, adrenal glands, gastrointestinal tract, retroperitoneum, pelvic organs and intra-abdominal lymph nodes. These lesions may remain clinically silent until they reach an advanced stage or may present with nonspecific symptoms such as abdominal pain, distension, loss of appetite, weight loss, fever, jaundice or a palpable abdominal mass. Although modern radiological techniques can accurately determine the location, size and extent of a lesion, imaging findings alone may not always establish its exact pathological nature. Therefore, obtaining representative cellular or tissue material is often essential for making a definitive diagnosis and planning appropriate treatment.
Fine-needle aspiration cytology (FNAC) is a minimally invasive diagnostic procedure that allows the collection of cellular material from a suspected lesion using a thin needle. It is widely accepted because it is relatively simple, rapid, economical and associated with low patient discomfort. However, many intra-abdominal lesions are deeply situated, non-palpable or located close to major blood vessels and vital organs. Blind aspiration of such lesions may result in inadequate sampling or injury to surrounding structures. The use of radiological guidance, particularly ultrasonography and computed tomography, permits accurate localisation of the lesion and safe placement of the needle within its most representative area. Image-guided FNAC has consequently become an important diagnostic method for evaluating deep-seated abdominal and pelvic masses that cannot be accessed by conventional palpation-guided aspiration [1].
Ultrasonography is commonly used to guide FNAC because it is widely available, does not expose the patient to ionising radiation and allows real-time visualisation of the needle during the procedure. It is particularly useful for lesions involving the liver, gallbladder, pancreas, kidneys, ovaries and superficial retroperitoneal regions. Computed tomography guidance is preferred for small or deeply located lesions, especially those obscured by bowel gas, bone or complex anatomical structures. The combined use of imaging and cytology enables the radiologist to identify a safe needle path and helps the cytopathologist obtain representative cellular material from both palpable and non-palpable intra-abdominal lesions [2]. Studies have shown that image-guided FNAC can successfully differentiate inflammatory and non-neoplastic conditions from benign and malignant tumours, thereby supporting early clinical decision-making [3].
One of the major advantages of FNAC is its ability to provide a rapid preliminary diagnosis, which may reduce the need for exploratory laparotomy or other invasive diagnostic procedures. A cytological diagnosis of malignancy can assist clinicians in determining whether a patient requires surgery, chemotherapy, radiotherapy, palliative treatment or further investigation. FNAC is also useful in patients with advanced malignancy or poor general health who may not be suitable candidates for surgical biopsy. Compared with needle-core biopsy, FNAC generally requires a smaller needle, causes less tissue trauma and provides results more quickly. Nevertheless, core biopsy may offer better preservation of tissue architecture and may be required for the complete classification of certain tumours. The two techniques may therefore be considered complementary rather than competing procedures [4].
The diagnostic success of image-guided FNAC depends on several factors, including the size and location of the lesion, the presence of necrosis or fibrosis, the experience of the radiologist, the aspiration technique, specimen preparation and the cytopathologist’s expertise. Inadequate aspirates may occur when the lesion is very small, predominantly cystic, necrotic, calcified or poorly accessible. False-negative results may arise when the needle fails to sample the representative tumour area, while false-positive diagnoses are less common but may occur because of marked reactive atypia or difficulty in interpreting poorly differentiated neoplasms. Careful correlation of cytological findings with clinical and radiological features is therefore essential for improving diagnostic accuracy and reducing interpretation errors [5].
The spectrum of lesions encountered on intra-abdominal FNAC varies according to the organ involved and the patient population. The liver is frequently sampled because it is commonly affected by primary hepatocellular neoplasms, metastatic carcinomas, inflammatory conditions and abscesses. Pancreatic masses may include adenocarcinoma, neuroendocrine tumours, cystic neoplasms and inflammatory lesions. Renal, adrenal, retroperitoneal and lymph-node lesions also demonstrate varied cytomorphological patterns. A large single-centre experience involving abdominal organs showed that image-guided aspiration could provide clinically valuable diagnoses across multiple organ systems, although diagnostic yield differed according to the site and nature of the lesion [6].
Additional specimen-processing methods can improve the diagnostic value of FNAC. Cell-block preparation allows aspirated material to be processed in a manner similar to a small histological biopsy. It provides better appreciation of tissue architecture and enables the performance of special stains, immunocytochemistry and selected molecular investigations. Combining conventional cytological smears with cell-block sections has been reported to improve diagnostic sensitivity, specificity and tumour classification in intra-abdominal mass lesions [7]. However, despite these developments, cytological findings must be compared with histopathology whenever biopsy or surgical specimens are available.
Histopathological examination remains the reference standard for confirming the nature of a lesion because it permits assessment of tissue architecture, invasion, differentiation and the relationship between tumour cells and surrounding structures. Cytohistopathological correlation is therefore essential for evaluating the reliability of image-guided FNAC. It helps determine sensitivity, specificity, positive predictive value, negative predictive value and overall diagnostic accuracy. It also identifies causes of cytological–histological disagreement, such as sampling error, inadequate cellularity, tumour heterogeneity and interpretative difficulty. A prospective study of abdominopelvic masses reported high diagnostic accuracy for ultrasonography-guided FNAC when cytological diagnoses were compared with corresponding histopathological findings [8].
A study that includes both retrospective and prospective components can provide a more complete assessment of the diagnostic performance of image-guided FNAC. The retrospective component allows evaluation of the previously encountered cytological spectrum, adequacy rates and available histopathological follow-up, while the prospective component permits standardised specimen collection, clinical–radiological correlation and systematic histological confirmation. Therefore, the present study was undertaken to evaluate the cytomorphological spectrum of image-guided FNAC in intra-abdominal lesions and to correlate cytological diagnoses with histopathological findings. The study also aims to determine the diagnostic accuracy of the procedure and analyse the possible causes of discordant and inconclusive results.
MATERIALS AND METHODS:
The following section is based on the study design, setting, procedural details, cytological processing and cytohistopathological correlation reported in the thesis. The thesis describes 660 image-guided FNAC cases studied at Goa Medical College from 2010 to 2017, with histopathological follow-up available in 58 cases.
Study design and setting
This was a hospital-based observational study with retrospective and prospective components, conducted in the Department of Pathology, Goa Medical College and Hospital, Bambolim, Goa, India. The study covered an eight-year period from January 2010 to December 2017. It evaluated the cytomorphological spectrum and diagnostic utility of image-guided fine-needle aspiration cytology in patients with intra-abdominal lesions.
A total of 660 image-guided FNAC cases were included. The study assessed the patients’ demographic characteristics, anatomical distribution of lesions, imaging modality used for aspiration, cytological diagnosis and available histopathological findings. The retrospective component was based on cases documented during the earlier part of the study period, whereas cases included during the prospective component were evaluated at the time of presentation and aspiration. The exact division of the study period into retrospective and prospective phases was not stated in the thesis and should be added before journal submission.
Study population
The study population consisted of patients with clinically or radiologically detected intra-abdominal lesions who were referred to the Department of Pathology for image-guided FNAC. Lesions involving the following anatomical sites were included:
· Liver, gallbladder and common bile duct
· Spleen and pancreas
· Kidneys and adrenal glands
· Ovaries and uterus
· Retroperitoneal lymph nodes and other retroperitoneal masses
· Gastrointestinal tract
· Mesentery, omentum and psoas region
· Other intra-abdominal and pelvic sites
Patients of all age groups and both sexes were eligible when an intra-abdominal lesion could be localised by ultrasonography or computed tomography and image-guided aspiration was considered technically feasible.
Before the procedure, informed consent was obtained from the patient or, where applicable, from the parent or legally authorised representative. Patients underwent assessment of their coagulation status, including bleeding time, clotting time, platelet count and prothrombin time. Aspiration was undertaken only when the evaluated coagulation parameters were within the acceptable range.
Patients with uncorrected coagulation abnormalities or those in whom image-guided aspiration could not be safely performed were not considered suitable for the procedure. However, formal inclusion and exclusion criteria were not separately described in the original thesis and should be confirmed from the institutional records.
Clinical and radiological assessment
Relevant clinical details, including age, sex, presenting complaints, previous diagnosis of malignancy and suspected primary tumour site, were obtained from the available clinical records and cytology request forms. The anatomical location and radiological characteristics of each lesion were documented.
Fine-needle aspiration was performed under either ultrasonographic or computed tomographic guidance. The imaging modality was used to localise the lesion, identify a suitable area for sampling, determine a safe needle pathway and confirm the position of the needle tip within the lesion. The patient was positioned according to the anatomical location of the lesion and the requirements of the radiological procedure.
Before aspiration, the patient’s pulse and blood pressure were recorded. Patient cooperation was ensured, and the steps of the procedure were explained. No local anaesthesia was routinely administered.
Fine-needle aspiration procedure
Image-guided FNAC was performed using the standard aspiration technique described in the thesis. The equipment consisted of a sterile 22-gauge lumbar puncture needle measuring approximately 90 mm, a 10-mL disposable syringe and a modified Cameco syringe holder.
The skin overlying the selected aspiration site was cleaned with povidone-iodine and spirit and was allowed to dry. The needle was connected to the 10-mL syringe and mounted on the syringe holder. The patient was asked to remain still and, where required, to briefly hold their breath during needle insertion.
The needle was introduced through the skin and advanced towards the lesion under ultrasonographic or computed tomographic guidance. The location of the needle tip within the target lesion was confirmed radiologically. Negative pressure was then created by withdrawing the syringe plunger. The needle was moved gently backwards and forwards in different directions within the lesion to obtain representative material. Multiple directional movements were avoided during aspiration of splenic lesions because of the increased risk of bleeding.
Before withdrawing the needle, the negative pressure was released to prevent aspirated material from entering the syringe barrel. The needle was then removed, and firm pressure was applied to the puncture site to control minor bleeding. The aspiration site was sealed with a tincture of benzoin dressing.
Preparation and staining of cytological smears
After aspiration, the needle was detached from the syringe. The syringe was filled with air, and the needle was reattached. The aspirated material was gently expelled onto three to five clean glass slides, depending on the amount of material obtained.
Thin smears were prepared by placing a second glass slide over the aspirated material, applying gentle pressure and smoothly separating the two slides. Most smears were immediately wet-fixed in a solution containing equal proportions of ether and absolute ethyl alcohol. The minimum fixation period was two hours, after which the smears were stained with haematoxylin and eosin.
Additional smears were air-dried and stained with May–Grünwald–Giemsa stain. When the aspirated material was predominantly fluid, it was centrifuged, and smears were prepared from the resulting sediment.
The thesis did not report the routine use of cell-block preparation, immunocytochemistry or molecular investigations. These ancillary methods were therefore not included in the primary diagnostic protocol.
Cytological evaluation
All stained smears were examined by light microscopy in the Department of Pathology. Cytological interpretation was made after correlating the microscopic findings with the available clinical and radiological information.
Cases were classified into the following broad diagnostic groups:
1. Benign lesions
- Benign neoplastic lesions
- Non-neoplastic and inflammatory lesions
2. Malignant lesions
- Primary malignant neoplasms
- Metastatic malignant neoplasms
- Cases reported as positive for malignancy
3. Non-diagnostic or inconclusive lesions
- Scantily cellular aspirates
- Aspirates containing only blood
- Aspirates containing only necrotic material
- Smears showing only normal or reactive epithelial cells
- Smears showing atypical cells in which malignancy could not be confirmed
- Cases in which a definite benign or malignant diagnosis could not be established
The cytological diagnosis was further classified according to the organ involved and the specific morphological diagnosis wherever sufficient material was available.
Histopathological examination and reference standard
Histopathological correlation was undertaken in patients who subsequently underwent surgical biopsy or excision of the lesion. The final histopathological diagnosis was considered the reference standard for evaluating the accuracy of FNAC.
Histopathological follow-up was available in 58 of the 660 cases. Cytological and histopathological diagnoses were compared and classified as:
· True positive: FNAC and histopathology both indicated malignancy.
· True negative: FNAC and histopathology both indicated a benign or non-malignant lesion.
· False positive: FNAC indicated malignancy, but histopathology showed a benign or non-malignant lesion.
· False negative: FNAC was benign, inconclusive or non-diagnostic, but histopathology demonstrated malignancy.
The available correlation dataset contained 34 true-positive, 15 true-negative, two false-positive and seven false-negative cases.
Study outcomes
The primary outcome was the diagnostic performance of image-guided FNAC for differentiating malignant from benign intra-abdominal lesions using histopathological diagnosis as the reference standard.
Secondary outcomes included:
· Adequacy and diagnostic yield of FNAC
· Distribution of lesions according to age and sex
· Organ-wise and site-wise distribution
· Frequency of benign, malignant and inconclusive diagnoses
· Distribution of primary and metastatic malignancies
· Comparison of cytological and histopathological diagnoses
· Procedure-related complications
Statistical analysis
Data were summarised using frequencies and percentages for categorical variables. Age was presented using the mean and age-group distribution, as reported in the original study.
Based on the available 58 correlated cases, the thesis reported a sensitivity of approximately 85%, specificity of approximately 89%, positive predictive value of approximately 94%, negative predictive value of approximately 73% and overall diagnostic accuracy of approximately 86%.
For submission to a high-ranking journal, these diagnostic estimates should also be presented with 95% confidence intervals. The statistical software and version used for analysis should be added once confirmed.
RESULTS:
The retrospective and prospective components were analysed together because the thesis did not provide separate results for the two study phases. A total of 660 patients with intra-abdominal lesions underwent ultrasonography- or computed tomography-guided FNAC during the eight-year study period. The patients ranged in age from 19 days to 89 years. The largest proportion belonged to the 51–60-year age group, followed by the 41–50-year and 61–70-year groups. There were 392 males and 268 females, giving a male-to-female ratio of approximately 1.46:1. Computed tomography was used for guidance in 427 cases, whereas ultrasonography was used in 233 cases.
Table 1. Demographic and procedural characteristics of the study population
|
Characteristic |
Category |
Number of cases |
Percentage (%) |
|
Age group, years |
0–10 |
27 |
4.09 |
|
11–20 |
24 |
3.64 |
|
|
21–30 |
57 |
8.64 |
|
|
31–40 |
93 |
14.09 |
|
|
41–50 |
134 |
20.30 |
|
|
51–60 |
153 |
23.18 |
|
|
61–70 |
118 |
17.88 |
|
|
>70 |
54 |
8.18 |
|
|
Sex |
Male |
392 |
59.39 |
|
Female |
268 |
40.61 |
|
|
Radiological guidance |
Computed tomography |
427 |
64.70 |
|
Ultrasonography |
233 |
35.30 |
|
|
Total |
660 |
100.00 |
The liver was the most frequently aspirated organ, accounting for 307 cases. This was followed by retroperitoneal lymph nodes, kidneys, ovaries and gastrointestinal lesions. Together, hepatobiliary lesions accounted for 313 of the 660 cases. The anatomical distribution of the lesions is presented in Table 2.
Table 2. Anatomical distribution of intra-abdominal lesions subjected to image-guided FNAC
|
Anatomical site |
Number of cases |
Percentage (%) |
|
Liver |
307 |
46.52 |
|
Gallbladder |
3 |
0.45 |
|
Common bile duct |
3 |
0.45 |
|
Spleen |
25 |
3.79 |
|
Pancreas |
13 |
1.97 |
|
Kidney |
60 |
9.09 |
|
Adrenal gland |
9 |
1.36 |
|
Ovary |
52 |
7.88 |
|
Uterus |
13 |
1.97 |
|
Retroperitoneal lymph nodes |
70 |
10.61 |
|
Other retroperitoneal lesions |
32 |
4.85 |
|
Gastrointestinal tract |
46 |
6.97 |
|
Mesentery |
9 |
1.36 |
|
Omentum |
10 |
1.52 |
|
Psoas region |
4 |
0.61 |
|
Undescended testis |
3 |
0.45 |
|
Paravesical region |
1 |
0.15 |
|
Total |
660 |
100.00 |
A definite cytological diagnosis was possible in 477 cases, giving an overall diagnostic yield of 72.27%. Of the total study population, 135 cases were classified as benign and 342 as malignant. The remaining 183 cases were classified as inconclusive or non-diagnostic.
Among the benign diagnoses, 102 were non-neoplastic lesions and 33 were benign neoplasms. Among the malignant diagnoses, 200 were primary malignancies, 114 were metastatic malignancies and 28 were reported as positive for malignancy without further tumour typing. The non-diagnostic category included 157 cases with inadequate material and 26 cases showing atypical cells or cytological findings in which malignancy could not be excluded.
Table 3. Overall cytological classification of image-guided FNAC findings
|
Cytological category |
Number of cases |
Percentage of total (%) |
|
Definitive cytological diagnosis |
477 |
72.27 |
|
Benign lesions |
135 |
20.45 |
|
Benign neoplastic lesions |
33 |
5.00 |
|
Non-neoplastic lesions |
102 |
15.45 |
|
Malignant lesions |
342 |
51.82 |
|
Primary malignancies |
200 |
30.30 |
|
Metastatic malignancies |
114 |
17.27 |
|
Positive for malignancy |
28 |
4.24 |
|
Inconclusive/non-diagnostic |
183 |
27.73 |
|
Inadequate material |
157 |
23.79 |
|
Atypical cells/malignancy not excluded |
26 |
3.94 |
|
Total |
660 |
100.00 |
The proportion of benign, malignant and inconclusive lesions varied considerably according to the anatomical site. Malignancy was identified in all three gallbladder lesions and all three lesions involving undescended testes. High proportions of malignancy were also observed in adrenal lesions, retroperitoneal lymph nodes, gastrointestinal lesions and pancreatic masses.
Benign lesions predominated in the uterus, psoas region, mesentery and spleen. The highest proportions of inconclusive results occurred in the ovary, omentum, kidney and liver.
Table 4. Organ-wise distribution of benign, malignant and inconclusive FNAC diagnoses
|
Anatomical site |
Total |
Benign, n (%) |
Malignant, n (%) |
Inconclusive, n (%) |
|
Liver |
307 |
56 (18.24) |
160 (52.12) |
91 (29.64) |
|
Gallbladder |
3 |
0 (0.00) |
3 (100.00) |
0 (0.00) |
|
Common bile duct |
3 |
0 (0.00) |
2 (66.67) |
1 (33.33) |
|
Spleen |
25 |
16 (64.00) |
3 (12.00) |
6 (24.00) |
|
Pancreas |
13 |
1 (7.69) |
9 (69.23) |
3 (23.08) |
|
Kidney |
60 |
12 (20.00) |
29 (48.33) |
19 (31.67) |
|
Adrenal gland |
9 |
1 (11.11) |
7 (77.78) |
1 (11.11) |
|
Ovary |
52 |
12 (23.08) |
19 (36.54) |
21 (40.38) |
|
Uterus |
13 |
12 (92.31) |
1 (7.69) |
0 (0.00) |
|
Retroperitoneal lymph nodes |
70 |
6 (8.57) |
50 (71.43) |
14 (20.00) |
|
Other retroperitoneal lesions |
32 |
8 (25.00) |
18 (56.25) |
6 (18.75) |
|
Gastrointestinal tract |
46 |
0 (0.00) |
33 (71.74) |
13 (28.26) |
|
Mesentery |
9 |
6 (66.67) |
0 (0.00) |
3 (33.33) |
|
Omentum |
10 |
1 (10.00) |
5 (50.00) |
4 (40.00) |
|
Psoas region |
4 |
4 (100.00) |
0 (0.00) |
0 (0.00) |
|
Undescended testis |
3 |
0 (0.00) |
3 (100.00) |
0 (0.00) |
|
Paravesical region |
1 |
0 (0.00) |
0 (0.00) |
1 (100.00) |
|
Total |
660 |
135 (20.45) |
342 (51.82) |
183 (27.73) |
Among the 307 hepatic lesions, metastatic malignancy was the most frequent diagnosis, accounting for 83 cases. Hepatocellular carcinoma was diagnosed in 54 cases. Pyogenic abscess was the most frequent benign hepatic lesion, with 31 cases. Among the hepatic metastases, adenocarcinoma was the predominant morphological type.
Pyogenic abscess was the most frequent splenic diagnosis. Pancreatic adenocarcinoma was identified in eight of the 13 pancreatic aspirates. Renal cell carcinoma was the most frequent malignant renal diagnosis, followed by Wilms tumour and renal metastasis.
Papillary adenocarcinoma was the predominant ovarian malignancy, whereas leiomyoma represented almost all uterine lesions. Lymphoma was the most common diagnosis among retroperitoneal lymph-node aspirates. Sarcomas predominated among non-nodal retroperitoneal masses, while adenocarcinoma was the most frequent gastrointestinal diagnosis.
Table 5. Predominant cytological diagnoses according to anatomical site
|
Anatomical site |
Predominant diagnosis |
Number of cases |
Percentage within site (%) |
|
Liver |
Metastatic malignancy |
83 |
27.04 |
|
Liver |
Hepatocellular carcinoma |
54 |
17.59 |
|
Liver |
Pyogenic abscess |
31 |
10.10 |
|
Spleen |
Pyogenic abscess |
10 |
40.00 |
|
Pancreas |
Adenocarcinoma |
8 |
61.54 |
|
Kidney |
Renal cell carcinoma |
14 |
23.33 |
|
Adrenal gland |
Neuroblastoma |
5 |
55.56 |
|
Ovary |
Papillary adenocarcinoma |
14 |
26.92 |
|
Uterus |
Leiomyoma |
12 |
92.31 |
|
Retroperitoneal lymph nodes |
Lymphoma |
30 |
42.86 |
|
Other retroperitoneal lesions |
Sarcoma |
13 |
40.63 |
|
Gastrointestinal tract |
Adenocarcinoma |
31 |
67.39 |
|
Mesentery |
Mesenteric cyst |
4 |
44.44 |
|
Omentum |
Metastatic malignancy |
5 |
50.00 |
|
Psoas region |
Abscess |
4 |
100.00 |
|
Undescended testis |
Malignant germ-cell tumour |
3 |
100.00 |
Histopathological follow-up was available in 58 cases, representing 8.79% of the total study population. Based on the classification provided in the thesis, 34 cases were true positive, 15 were true negative, two were false positive and seven were false negative.
Using these raw values, the recalculated sensitivity of FNAC for detecting malignancy was 82.93%, specificity was 88.24%, positive predictive value was 94.44%, negative predictive value was 68.18%, and overall diagnostic accuracy was 84.48%.
Table 6. Cytohistopathological correlation and diagnostic performance of image-guided FNAC
A. Two-by-two diagnostic classification
|
FNAC classification |
Malignant on histopathology |
Benign on histopathology |
Total |
|
Malignant |
34, true positive |
2, false positive |
36 |
|
Benign/non-malignant |
7, false negative |
15, true negative |
22 |
|
Total |
41 |
17 |
58 |
B. Diagnostic performance
|
Diagnostic measure |
Estimate (%) |
95% confidence interval (%) |
|
Sensitivity |
82.93 |
68.74–91.47 |
|
Specificity |
88.24 |
65.66–96.71 |
|
Positive predictive value |
94.44 |
81.86–98.46 |
|
Negative predictive value |
68.18 |
47.32–83.64 |
|
Overall diagnostic accuracy |
84.48 |
73.07–91.62 |
Confidence intervals were calculated from the thesis-derived raw 2 × 2 data using the Wilson method.
No major procedure-related complications were recorded. Minor complications occurred in five patients, giving a complication rate of 0.76%. Three patients developed syncopal episodes associated with hypotension, while two experienced moderate abdominal pain. The affected patients recovered following conservative or symptomatic management.
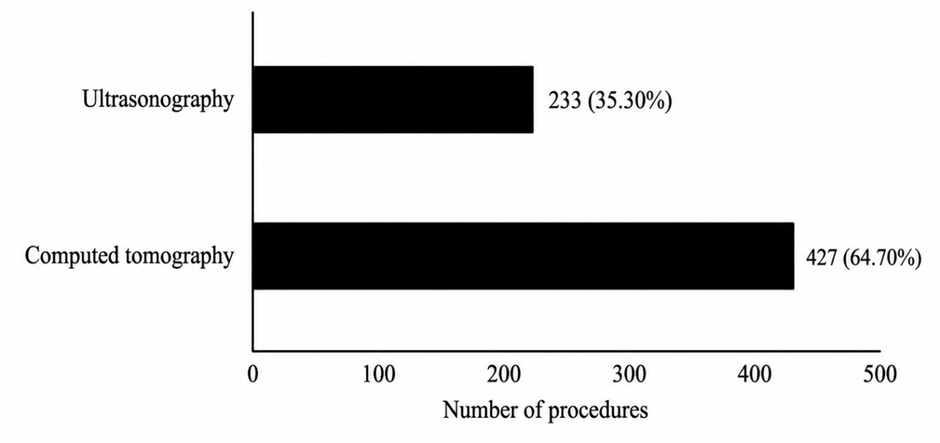
Figure 1. Distribution of image-guided fine-needle aspiration procedures according to the radiological guidance modality used
Figure 1 illustrates the distribution of image-guided fine-needle aspiration procedures according to the radiological guidance modality used. Of the 660 procedures included in the study, computed tomography guidance was used in 427 cases (64.70%), whereas ultrasonographic guidance was used in 233 cases (35.30%). Thus, computed tomography was the more frequently used imaging modality, accounting for nearly two-thirds of all image-guided FNAC procedures. Ultrasonography was used in slightly more than one-third of cases. The findings demonstrate the greater utilisation of computed tomography for the localisation and aspiration of intra-abdominal lesions in the study population.
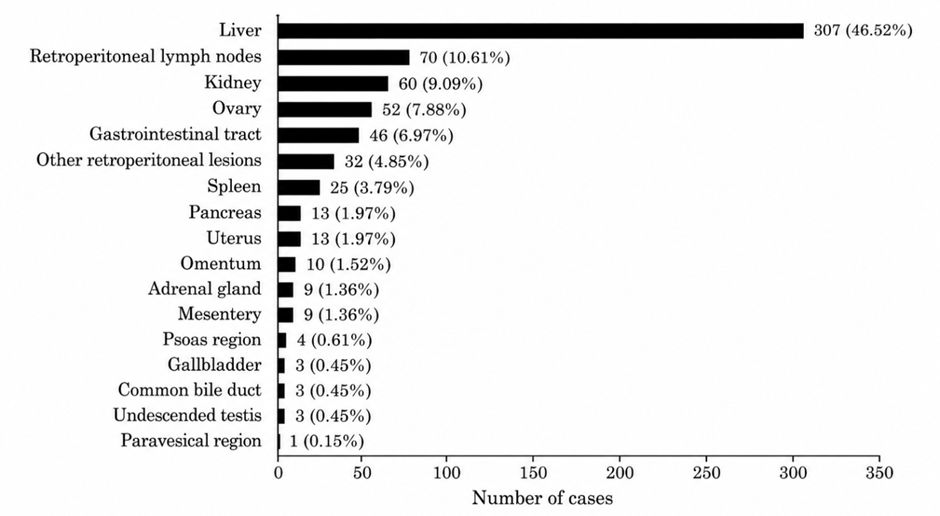
Figure 2. Anatomical distribution of the 660 intra-abdominal lesions subjected to image-guided fine-needle aspiration cytology
Figure 2 presents the anatomical distribution of the 660 intra-abdominal lesions subjected to image-guided FNAC. The liver was the most frequently aspirated site, accounting for 307 cases (46.52%), and represented almost half of all procedures. Retroperitoneal lymph nodes were the second most common site, with 70 cases (10.61%), followed by the kidney with 60 cases (9.09%), ovary with 52 cases (7.88%) and gastrointestinal tract with 46 cases (6.97%). Other retroperitoneal lesions accounted for 32 cases (4.85%), while splenic lesions constituted 25 cases (3.79%). Pancreatic and uterine lesions each accounted for 13 cases (1.97%). Lesions involving the omentum, adrenal gland, mesentery, psoas region, gallbladder, common bile duct, undescended testis and paravesical region were comparatively uncommon. Overall, the findings demonstrate a marked predominance of hepatic lesions among the intra-abdominal masses evaluated by image-guided FNAC.
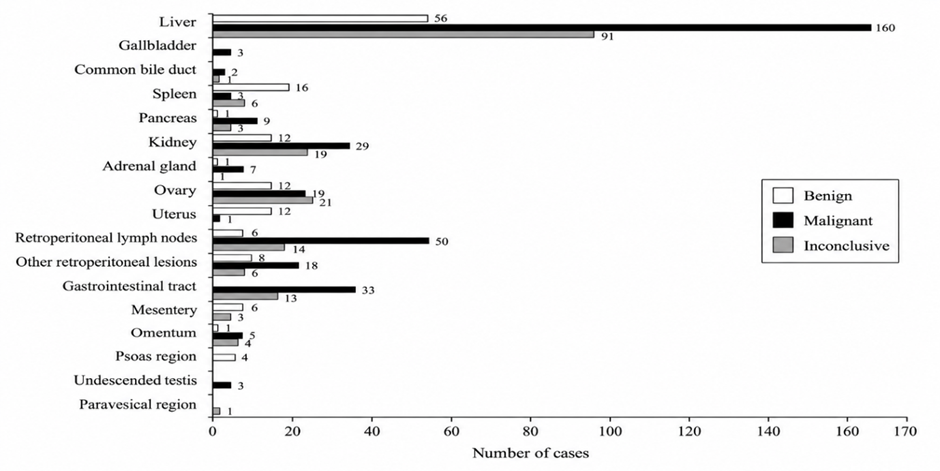
Figure 3. Organ-wise comparison of benign, malignant and inconclusive diagnoses obtained by image-guided fine-needle aspiration cytology
Figure 3 compares benign, malignant and inconclusive cytological diagnoses across the different intra-abdominal organs and anatomical sites. The liver contributed the largest number of cases, including 160 malignant, 91 inconclusive and 56 benign lesions. Malignant diagnoses also predominated in retroperitoneal lymph nodes (50 cases), the gastrointestinal tract (33 cases), kidneys (29 cases), ovaries (19 cases) and other retroperitoneal lesions (18 cases). Benign lesions were more common in the spleen (16 cases), uterus (12 cases), mesentery (6 cases) and psoas region (4 cases). The ovary showed the highest proportion of inconclusive aspirates, with 21 of 52 cases, followed by the kidney with 19 cases and retroperitoneal lymph nodes with 14 cases. All gallbladder and undescended testicular lesions were diagnosed as malignant, whereas the single paravesical lesion was inconclusive. Overall, malignant diagnoses formed the largest cytological category across most of the commonly sampled intra-abdominal sites.
DISCUSSION:
The present study evaluated 660 image-guided fine-needle aspiration cytology procedures performed for intra-abdominal lesions over eight years. The findings demonstrate the broad diagnostic application of FNAC across hepatobiliary, retroperitoneal, renal, splenic, pancreatic, gastrointestinal and female genital tract lesions. Most patients were male, and the highest frequency occurred in the 51–60-year age group. Similar studies of deep-seated abdominal masses have also reported greater representation of middle-aged and older patients and emphasised the value of integrating clinical, radiological and cytological findings [9,10].
Computed tomography was used in 427 cases (64.70%), whereas ultrasonography guided 233 procedures (35.30%). The predominance of CT guidance probably reflects the large number of deep, small or retroperitoneal lesions and the institutional availability of imaging services. CT permits precise localisation and selection of a safe needle pathway, while ultrasonography provides real-time guidance without ionising radiation. Sheikh et al. reported that both methods were useful for deep-seated masses and obtained diagnostic aspirates in 93.4% of cases without major complications [9]. The guidance modality should therefore be selected according to lesion location, visibility, accessibility and procedural safety.
The liver was the most frequently aspirated organ, contributing 307 cases (46.52%), followed by retroperitoneal lymph nodes, kidneys, ovaries and gastrointestinal lesions. This marked hepatic predominance may be explained by the liver’s accessibility and frequent involvement by both primary and metastatic tumours. Among malignant hepatic lesions, metastases were more frequent than hepatocellular carcinoma, with adenocarcinoma forming the largest metastatic group. Other hepatic FNAC studies have similarly identified metastatic carcinoma as a major component of malignant liver aspirates [11]. Swamy et al. and Nazir et al. showed that cytological architecture and cellular features can reliably differentiate hepatocellular carcinoma from metastatic malignancy [11,12].
Overall, malignant lesions accounted for 342 cases (51.82%), benign lesions for 135 cases (20.45%) and inconclusive aspirates for 183 cases (27.73%). The predominance of malignancy is expected in a tertiary referral hospital, where patients with radiologically suspicious, advanced or inoperable masses are more likely to undergo image-guided sampling. Hemalatha et al. also observed a high frequency of malignant lesions among abdominal and pelvic masses and reported an overall diagnostic accuracy of 96.3% [10]. These findings support FNAC as a useful tissue-sampling method for separating malignant from benign disease and guiding subsequent management.
The organ-wise pattern showed important variation. Malignancy predominated in the pancreas, adrenal gland, retroperitoneal lymph nodes, other retroperitoneal masses and gastrointestinal tract. Pancreatic adenocarcinoma was the leading pancreatic diagnosis, while lymphoma was the most common malignancy in retroperitoneal lymph nodes. Sarcomas formed the largest malignant group among non-nodal retroperitoneal lesions. Mehdi et al. likewise found image-guided FNAC useful for classifying retroperitoneal masses and highlighted the importance of cytomorphology, clinical information and radiological correlation, particularly for lymphomas and mesenchymal neoplasms [13].
Renal cell carcinoma was the most frequent malignant renal tumour. However, false-negative diagnoses occurred in cystic or inflammatory-appearing renal lesions that proved malignant on histopathology. Cystic change, necrosis and tumour heterogeneity can produce non-representative material. Renal FNAC remains useful in selected situations, including atypical imaging appearances, advanced disease, suspected metastasis and patients unsuitable for surgery [14]. Targeting viable solid areas and correlating cytology with imaging are essential for reducing sampling errors.
Most splenic lesions were benign, with pyogenic abscess predominating, whereas only a small proportion were malignant. This differs from splenic biopsy series focused mainly on lymphoma staging and may reflect differences in referral patterns and disease prevalence. Although splenic aspiration requires care because of the organ’s vascularity, Civardi et al. reported high clinical efficacy and low risk, with an overall diagnostic accuracy of 90.9% [15]. The absence of major haemorrhagic complications in the present study supports the safety of fine-needle sampling when coagulation parameters are acceptable and imaging guidance is used.
A definite cytological diagnosis was possible in 477 cases, producing a diagnostic yield of 72.27%. The inconclusive rate of 27.73% was relatively high and was mainly related to inadequate material, blood-only aspirates, necrosis and atypical cells insufficient for a firm diagnosis. Repeat aspiration, sampling from enhancing viable areas, rapid on-site evaluation, cell-block preparation and selective core biopsy could improve adequacy. Guo et al. obtained satisfactory liver aspirates in 99% of procedures and suggested that the presence of a pathologist in the radiology suite improves specimen quality and patient care [16].
Histopathological follow-up was available in 58 cases. Based on the raw correlation data, FNAC showed 82.93% sensitivity, 88.24% specificity, 94.44% positive predictive value, 68.18% negative predictive value and 84.48% overall diagnostic accuracy. The high positive predictive value indicates that a malignant FNAC diagnosis was highly reliable. However, the lower negative predictive value shows that a benign or inconclusive result cannot exclude malignancy when clinical and radiological suspicion remains high. Published accuracy estimates vary because of differences in lesion spectrum, sampling technique, on-site assessment and the handling of inconclusive aspirates [9,10,16].
Only five minor complications were recorded, including three syncopal episodes with hypotension and two cases of moderate abdominal pain; no major complication occurred. The principal limitations were the small proportion of cases with histopathological confirmation, the combined retrospective and prospective design and the absence of routine ancillary testing or on-site adequacy assessment. Despite these limitations, the large sample and broad anatomical spectrum indicate that image-guided FNAC is a rapid, minimally invasive and clinically valuable method for evaluating intra-abdominal lesions.
CONCLUSION:
Image-guided fine-needle aspiration cytology is a useful, rapid and minimally invasive method for evaluating intra-abdominal lesions. In the present study, it provided a definitive cytological diagnosis in 477 of 660 cases and successfully identified a broad spectrum of benign, malignant, inflammatory and metastatic lesions involving different abdominal organs. Malignant lesions formed the largest diagnostic category, and the liver was the most frequently sampled organ. Computed tomography was used more commonly than ultrasonography, reflecting its value in the assessment of deep-seated and anatomically complex lesions.
REFERENCES:
1. Pujani M, Jetley S, Jairajpuri ZS, Khan S, Hassan MJ, Rana S, et al. A critical appraisal of the spectrum of image guided fine needle aspiration cytology: a three year experience from a tertiary care centre in Delhi. Turk Patoloji Derg. 2016;32(1):27-34. doi:10.5146/tjpath.2015.01339.
2. Dosi S, Gupta G, Kawatra M, Chakrabarti PR, Agrawal P, Jain MR. Role of radiological-assisted cytology in intra-abdominal lesions: a 3 years’ experience in a tertiary care center. Int J Appl Basic Med Res. 2016;6(2):101-105. doi:10.4103/2229-516X.179022.
3. Sumana BS, Muniyappa B. Ultrasonography guided fine needle aspiration cytology with preparation of cell blocks in the diagnosis of intra-abdominal masses. J Clin Diagn Res. 2015;9(12). doi:10.7860/JCDR/2015/16490.6869.
4. Stewart CJR, Coldewey J, Stewart IS. Comparison of fine needle aspiration cytology and needle core biopsy in the diagnosis of radiologically detected abdominal lesions. J Clin Pathol. 2002;55(2):93-97. doi:10.1136/jcp.55.2.93.
5. Ghosh A, Ghartimagar D, Sathian B, Narasimhan R, Talwar OP. Value of image-guided fine-needle aspiration cytology: a study of 500 cases. Diagn Cytopathol. 2013;41(12):1052-1062. doi:10.1002/dc.22922.
6. Vasilj A, Kojić Katović S. Fine needle aspiration cytology of abdominal organs: ten-year single center experience. Acta Clin Croat. 2016;55(1):35-40. doi:10.20471/acc.2016.55.01.6.
7. Bhowmik S, Chakrabarti I, Ghosh P, Bera P, Banik T. Comparative evaluation of cell block method and smear cytology in fine needle aspiration cytology of intra-abdominal mass lesions. Iran J Pathol. 2018;13(2):179-187.
8. Baisakh P, Baisakh MR, Kumari BS, Mohanty BB, Panda DK, Pradhan S. Diagnostic accuracy of ultrasonography-guided fine needle aspiration cytology in abdominopelvic masses: a prospective study. Cureus. 2023;15(6). doi:10.7759/cureus.41228.
9. Sheikh M, Sawhney S, Dey P, Al-Saeed O, Behbehani A. Deep-seated thoracic and abdominal masses: usefulness of ultrasound and computed tomography guidance in fine needle aspiration cytology diagnosis. Australas Radiol. 2000;44(2):155-160. doi:10.1046/j.1440-1673.2000.00799.x.
10. Hemalatha AL, Sumana Sindhuram V, Sushma S, Suma JK, Varna I, Anubha Aditya. Ultrasound guided FNAC of abdominal-pelvic masses—the pathologists’ perspective. J Clin Diagn Res. 2013;7(2):273-277. doi:10.7860/JCDR/2013/4514.2745.
11. Swamy MCM, Arathi CA, Kodandaswamy CR. Value of ultrasonography-guided fine needle aspiration cytology in the investigative sequence of hepatic lesions with an emphasis on hepatocellular carcinoma. J Cytol. 2011;28(4):178-184. doi:10.4103/0970-9371.86344.
12. Nazir RT, Sharif MA, Iqbal M, Amin MS. Diagnostic accuracy of fine needle aspiration cytology in hepatic tumours. J Coll Physicians Surg Pak. 2010;20(6):373-376.
13. Mehdi G, Maheshwari V, Afzal S, Ansari HA, Ahmad I. Image-guided fine-needle aspiration of retroperitoneal masses: the role of the cytopathologist. J Cytol. 2013;30(1):36-41. doi:10.4103/0970-9371.107511.
14. Dragoescu EA, Liu L. Indications for renal fine needle aspiration biopsy in the era of modern imaging modalities. CytoJournal. 2013;10:15. doi:10.4103/1742-6413.115093.
15. Civardi G, Vallisa D, Bertè R, Giorgio A, Filice C, Caremani M, et al. Ultrasound-guided fine needle biopsy of the spleen: high clinical efficacy and low risk in a multicenter Italian study. Am J Hematol. 2001;67(2):93-99. doi:10.1002/ajh.1085.
16. Guo Z, Kurtycz DFI, Salem R, De Las Casas LE, Caya JG, Hoerl HD. Radiologically guided percutaneous fine-needle aspiration biopsy of the liver: retrospective study of 119 cases evaluating diagnostic effectiveness and clinical complications. Diagn Cytopathol. 2002;26(5):283-289. doi:10.1002/dc.10097.