Determinants of Sustainable Point-of-Care Testing Quality in Clinical Laboratories of Pakistan: Role of Quality Management Systems and Operational Controls.
- Rabeea Zia , MS QMS PIQC, superior university
- Sania Shahbas , MS QMS PIQC superior university
- Maria Tehreem , MBBS PGR chemical pathology at PKLI hospital
- Muhammad Waqas , MHA, Senior Manager at FMH Fatima Memorial Hospital Lahore
- Nadeem Iqbal , Lahore School of Aviation, The University of Lahore.
Article Information:
Abstract:
Background: Point-of-Care Testing (POCT) provides rapid diagnostic information but maintaining consistent quality outside conventional laboratory environments remains challenging. This study evaluated the determinants of sustainable POCT quality in clinical laboratories in Pakistan, with particular emphasis on Quality Management System Strength, Operator & Human Factors, Technology & Operational Control Factors, and Process Control Effectiveness.Methods: A quantitative, cross-sectional explanatory study was conducted among 344 laboratory managers, quality officers, laboratory technologists, and POCT operators working in public and private clinical laboratories in Pakistan. Data were collected using a structured questionnaire based on a five-point Likert scale. Descriptive statistics, Cronbach's alpha, and Pearson's correlation analysis were performed using SPSS, while relationships among study constructs and the mediating role of Process Control Effectiveness were assessed using Partial Least Squares Structural Equation Modeling (PLS-SEM) in SmartPLS.Results: Sustainable POCT Quality demonstrated the highest overall mean score (3.577 ± 0.607), followed by Process Control Effectiveness (3.556 ± 0.575), Quality Management System Strength (3.520 ± 0.609), Operator & Human Factors (3.480 ± 0.594), and Technology & Operational Control Factors (3.437 ± 0.625). All major constructs demonstrated positive correlations with Sustainable POCT Quality. Quality Management System Strength showed the strongest correlation with Sustainable POCT Quality (r = 0.633, p < 0.001). The QMS scale demonstrated good internal consistency (Cronbach's α = 0.840).Conclusion: Sustainable POCT quality was associated with organizational, human, technological, and process-control factors. Strengthening integrated quality-management and operational control systems may support more reliable and sustainable POCT services in Pakistan
Keywords:
Article :
INTRODUCTION:
Point of Care (POC) Testing is the term used for testing that occurs at or near the patient care location so that the health care provider can get their diagnostic results quickly and make appropriate clinical decisions. POCT can offer considerable advantages over traditional laboratory testing, including faster turnaround time, better diagnosis and treatment, more efficient workflow, and better patient outcomes, especially in emergency departments, intensive care units, outpatient clinics and healthcare centres (WHO, 2023; Nichols, 2021). Rising demand for POCT is due to technological breakthroughs, the escalating burden of chronic diseases and the need for decentralised healthcare services worldwide (Shaw, 2016).
The use of POCT has been growing significantly in private and public hospitals, clinical laboratories, emergency departments, and primary health care centres in Pakistan because of its ease of use, speed of result reporting and its contribution to improving the accessibility of healthcare. Examples of commonly used samples for POCT include glucose, cardiac biomarkers, diagnosis of infectious diseases, blood gasses and coagulation. The use of POCT is common, yet maintaining consistent quality and sustainability is still difficult due to the wide range of different healthcare professionals performing POCT with different levels of competency and training (Khan et al., 2019; Jafri et al., 2023).
International standards, including ISO 15189:2022 and ISO 22870:2016, highlight the need for the successful implementation of Quality Management Systems (QMS), competent staff, standardized operating procedures, equipment verification, quality control, documentation and ongoing quality improvement for sustainable POCT quality (International Organization for Standardization [ISO], 2016, 2022). Deficiencies of operator competency, lack of quality management practices, poor documentation, insufficient process control systems, equipment malfunction and a lack of compliance with standard operating procedures (SOPs) have been demonstrated to have effects on diagnostic accuracy, laboratory errors and patient safety (Plebani, 2018; Oliver et al., 2021).
In developing nations, including Pakistan, healthcare facilities face other specific problems such as restricted budget, poor infrastructure, lack of skilled personnel, regulatory compliance issues, and poor laboratory quality assurance systems. All these factors play a role in the variation of the performance of POCT and make the quality of the laboratory less sustainable in the healthcare institutions (WHO, 2023; Rabbani & Abbasi, 2017). Therefore, enhancing Quality Management Systems (QMS) and the implementation of effective operational controls are strategic goals for optimizing laboratory performance and assuring reliable diagnostic services.
In light of these factors, the present study aims to investigate the significance of sustainable POCT Quality determinants among the clinical laboratories of Pakistan by studying the effect of Sustainable POCT Quality determinants (SPSQ) such as Quality Management System Strength (QMS), Operator & Human Factors, and Technology & Process Control Factors (TPCF). Also, the study investigates the mediation of the relationship of these determinants to sustainable POCT quality through the variable Process Control Effectiveness.
Problem Statement
With the POCT, doctors can diagnose patients more quickly, take immediate action and give better care. However, with its increasing usage, there are still many clinical laboratories that have problems in supporting the sustainable quality of POCT. Current evidence suggests that diagnostic errors and the lack of consistency in testing performance are partly due to poor quality in Quality Management Systems, operator incompetency, lack of training, poor adherence to standard operating procedures, process failures in performing tests, lack of equipment maintenance, and limited technological integration (Plebani, 2018; Oliver et al., 2021).
There are several certified tertiary healthcare institutions in Pakistan with established quality assurance programs and some of them are implementing the internationally recognized quality standards, like ISO 15189 and ISO 22870 but the implementation is not uniform for all the public and private clinical laboratories in the country. Despite the availability of adequate funds, insufficient quality infrastructure and poor enforcement of regulations, many health care providers are still suffering from limited documentation, internal quality control, external quality assessment, equipment calibration, competency assessment, and continuous quality improvement issues (Jafri et al., 2023; Rabbani & Abbasi, 2017). These restrictions may lead to falsenegatives in diagnosis and negatively impact patient safety and clinical management.
Moreover, there has been a limited focus on the existing literature in Pakistan on laboratory accreditation, implementation of POCT services or just a single quality assurance practice. There has been limited empirical research that has at the same time explored the interaction of three factors (Quality Management System Strength, Operator & Human Factors, and Technology & Process Control Factors) on Sustainable POCT Quality. Besides, the role of Process Control Effectiveness as a mediator between the independent and dependent variables, i.e., improvement of sustainable quality outcomes has been scarcely explored in the Pakistani healthcare setting.
Thus, a comprehensive empirical research is needed, which combines organizational, human and technological factors in a single framework. This study aims to mitigate this research gap by exploring the relationship of Quality Management Systems and operational controls with Sustainable POCT Quality in the clinical laboratories of Pakistan with evidence-based recommendations that would be useful for the clinical laboratory managers, healthcare policy makers and quality professionals.
The study added value in both academic and healthcare management aspects with empirical evidence of determinants that influenced the sustainable quality of Point-of-Care Testing (POCT) in clinical laboratories of Pakistan. The results gave laboratory managers evidence to support the improvement of quality assurance systems, operator competency and operating controls, and enhanced continuous quality improvement practices. The study also gave pertinent evidence to policymakers and healthcare authorities to develop and strengthen the standardized management and quality assurance frameworks and national guidelines for POCT. The study was able to identify factors for the reliable, accurate and sustainable performance of POCT which could lead to better diagnostic accuracy and patient safety. In addition, the findings provided some additional evidence on POCT quality management in the context of a developing healthcare system and may be applicable to other healthcare quality-improvement efforts in Pakistan and other resource-limited environments.
Literature Review
Point-of-Care Testing (POCT) refers to the diagnostic testing conducted at or close to the patient's location, which helps in making quick clinical decisions and optimizes healthcare resources. In this context, POCT has grown rapidly worldwide, especially in hospitals, primary care centres, emergency departments and even in community health services, as it overcomes the turnaround time and improves patient outcomes (Miyachi, 2016; WHO, 2023). It is noteworthy in international literature that POCT is especially useful in clinical situations requiring immediate results for life-saving measures, such as critical care. Although it has many benefits, all global studies highlight the need for quality control measures and trained staff to ensure that POCT is not governed with unstructured quality systems and personnel, which are the main risks (ISO 22870:2016; WHO, 2023).
A raised patient load along with the lack of centralized laboratory facilities, has led to an upsurge of the use of POCT in tertiary care hospitals and private healthcare institutions in Pakistan. Major tertiary care hospitals, such as Aga Khan University Hospital, report extensive utilization of POCT for glucose testing, cardiac markers, infectious diseases and coagulation profiles. The literature also suggests that the implementation of POCTs in Pakistan is not always coordinated or standardized, experiences poor supervision, quality control issues, and limited linkage with laboratory quality management systems (QMS) (Khan et al., 2019; Jafri et al., 2023). This means there is a variation in test accuracy, and questions about the accuracy and safety of diagnosis.
Laboratory Quality Management System (QMS)
Quality Management System (QMS) is regarded as the backbone of any laboratory medicine globally. Laboratories are required to have structured systems, including documentation, internal audits, corrective actions, quality control, competency management, and continuous improvement, as per the standards (ISO 15189:2022; Oliver et al., 2021). In the international literature, it has been demonstrated that laboratories that have a well-established QMS framework have a higher diagnostic accuracy, better compliance and lower error rate (Plebani, 2018; WHO, 2023).
In healthcare systems, QMS is totally embedded in the laboratory operations and in the governance of POCT. In the European and Canadian health-care systems, for instance, the inclusion of multidisciplinary committees of POCT, the training of operators and the continuous monitoring of quality are mandatory for accreditation (Oliver et al., 2021; Pernet et al., 2012). These systems assure the reliability of POCT results; the same as that of central laboratory testing.
The implementation of QMS in Pakistan is not consistent. Many of public sector laboratories do not have formal internal audits, have not participated in external quality assessments on regular basis, nor have any structured documentation system been implemented (Rabbani & Abbasi, 2017). This disparity creates huge disparities in laboratory performance and POCT quality across the country. Funds being insufficient, unavailability of trained quality professionals and incompetence in the regulation enforcement are the main impediments to the implementation of QMS in Pakistan.
Human factors are known as one of the most important factors that contribute to laboratory and POCT errors worldwide. Research from around the world demonstrates that operator competence, training, experience, workload and following of SOPs directly influence test accuracy and reliability (WHO, 2023; Plebani, 2018). POCT is typically performed outside the laboratory setting, with testing often being done by non-laboratory personnel, such as nurses and physicians, which adds risk of pre-analytical and analytical errors.
Structured competency assessment program and continuous training have been demonstrated to have a positive impact on the performance of POCT worldwide, particularly in this respect (Oliver et al., 2021). In ISO 22870, the focus is on the training, assessment and ongoing monitoring of all operators of POCT.
According to literature in Pakistan, challenges are commonplace in operator. Research indicates that inadequate training, failure to obtain competency certification and improper SOPs implementation are significant factors responsible for the provision of inaccurate POCT results (Khan et al., 2019; Jafri et al., 2023). There are shortcomings in the implementation of formal system of competency evaluation in many hospitals particularly in public sector hospitals. This results in fluctuations of test performance and jeopardizes sustainable POCT quality. Human factors are operator competence, training, experience, procedure compliance, workload, communication and error management. Poor performance of operators is still one of the most common reasons for inaccurate POCT.
Factors that affect the technology and the process.Factors related to the technology and the process.Technology and process control systems are not only vital for quality control of POCT processes but also form a technological infrastructure throughout the world. The main factors that are regarded as the critical features of modern laboratory systems are equipment reliability, calibration, preventive maintenance, automation, and integration with the laboratory information systems (ISO 22870:2016; WHO, 2023). According to international literature, automated systems and integrated quality monitoring improves the consistency of diagnostic results and decreases human error.
In well-developed health-care systems, POCT devices are usually linked to a centralized laboratory system, so that the real time monitoring, documentation and quality monitoring of the devices can be made. This integration helps to ensure continuous enhancement and conform with regulatory requirements (Oliver et al., 2021).
However, there are many laboratories in Pakistan that are still using stand-alone POCT devices that have a lack of connectivity and maintenance system. From the literature, it is found that there are several challenges in maintaining the quality of POCTs including irregular calibration, no preventive maintenance, and poor equipment monitoring (Jafri et al., 2023). Such constraints can have a profound impact on the accuracy and reliability of these tests, especially within resource-limited healthcare environments. This includes equipment reliability, automation, calibration systems, maintenance systems and procedures, connectivity and standard operating procedures. The use of advanced technologies and well managed operational processes can lead to faster and more accurate and consistent testing.
Process Control Effectiveness
Process Control Effectiveness is the ability to achieve consistent quality by having the necessary internal quality control (IQC), external quality assessment (EQA), monitoring, corrective action, and standard procedures. The importance of effective process control to minimize laboratory errors and meet accreditation requirements is emphasized in international literature (Plebani, 2018; WHO, 2023).
Process control is monitored by quality indicators and automated systems throughout the process, in countries with a well-developed laboratory system. A structured corrective action process and continuous performance evaluation mechanisms (ISO 15189:2022; Oliver et al., 2021) are required in the laboratories.
However, in Pakistan, there is still a lack of consistency in implementing structured process control systems. There are no formal monitoring systems and processes for standardised corrective action in many laboratories, which results in variability in test quality. This gap underscores the need for more robust process control systems to ensure sustainable POCT quality in healthcare institutions in Pakistan. Process control effectiveness measures how well quality control processes, monitoring systems, corrective action and performance reviews are able to produce uniform test results. The quality outcomes are a vehicle that connects operational practices to effective process control.
Sustainable POCT Quality
Sustainable POCT Quality is the capability of healthcare systems to provide accurate, reliable, timely and clinically relevant POCT results in a sustainable manner that meets quality standards. Worldwide, sustainability of laboratory quality is achieved by ISO 15189:2022 integration of QMS, trained personnel, advanced technology and continuous process control.
International research reveals that structured governance models, ongoing training programs and integrated quality monitoring systems are crucial to sustaining POCT quality. In Europe and North America, governance committees have regulations and protocols that maintain the sustainability of POCT (Oliver et al., 2021).
However sustainable POCT quality is still being developed in Pakistan. While structured POCT programs have been introduced at some Tertiary hospitals, there is no standardized national guideline for governance of POCT in most healthcare institutions. Consequently, the quality of the service is not sustainable in all institutions and this poses risks to patients' safety and diagnostic reliability (Khan et al., 2019; Jafri et al., 2023). The ongoing capacity of point-of-care testing services to generate clinically relevant diagnostic information that is accurate, reliable, timely and compliant with quality standards for sustained operational efficiency is known as Sustainable POCT Quality.
Research Gap
Although the subject of POCT quality has gained attention at both the global and national level, there are still some gaps in the literature. Firstly, most global studies have been conducted on well resourced healthcare systems, and few studies have investigated POCT quality problems in developing countries such as Pakistan. Secondly, studies conducted in Pakistan predominantly discussed the implementation of POCT or accreditation of laboratories without considering sustainable POCT quality as a multidimensional construct. Thirdly, limited integration of QMS Strength, Operator & Human Factors and Technology & Process Control Factors in a single conceptual model. Fourth, there is a lack of empirical testing of mediating role of Process Control Effectiveness in the context of Pakistan. Fifth, most of the studies conducted in Pakistan are descriptive and are conducted on specific institutions and settings, which are mostly from tertiary health institutes and hence not representative of the public and private health care sector.
Thus, there is no integrated, empirical model that simultaneously investigates organizational, human, technological and operational determinants of sustainable POCT quality, applying advanced statistical analysis like Structural Equation Modeling (SEM) to the study. To this end, the present study aims to develop and test a complete framework for sustainable POCT quality in Pakistan's clinical laboratories in order to overcome such gaps.
Theoretical and Conceptual Framework
This study has been based on Total Quality Management (TQM) Theory and Socio-Technical Systems Theory. TQM offered an organizational quality perspective by focusing on continuous improvement, the management of effective processes, employee participation, and systematic programs to attain organizational quality goals. In the field of POCT, this view reinforced the need for organized quality policies, documentation, internal audits, corrective actions, and quality-improvement efforts for providing quality and reliable testing services.
Socio-Technical Systems Theory was used to explore the relationship between the human and technological factors of POCT services. The theory is that organizational performance relies on the successful integration of people, processes, technology and management systems. Thus, Operator & Human Factors (competency, training, experience, and adherence to standard operating procedures (SOP)) and Technology & Operational Control Factors (equipment reliability, calibration, maintenance, and automation) were included in the study. This approach acknowledged that quality of sustainable POCT requires a combination of suitable technology, but also skilled operators and adequate organizational resources.
This was the basis on which the conceptual framework was designed, which was used to investigate the determinants of Sustainable POCT Quality in clinical laboratories in Pakistan. The independent variables were defined as Quality Management System Strength, Operator & Human Factors, and Technology & Operational Control Factors, and the dependent variable was the Process Control Effectiveness, which was included as a mediating variable. The effectiveness of the quality-control procedures, monitoring systems, corrective actions, and process standardization was measured as Process Control Effectiveness. Sustainable POCT Quality was the dependent variable and was measured by accuracy, reliability, timeliness, regulatory compliance, and continuous performance improvement. It was thus suggested that the three independent variables had a direct and indirect effect on Sustainable POCT Quality via Process Control Effectiveness in the framework.
Table 1: Conceptual Framework Structure
|
Framework Component |
Study Variable |
Key Dimensions / Indicators |
Proposed Relationship |
|
Independent Variable 1 |
Quality Management System Strength (QMS) |
Quality policies; documentation and record control; internal audits; corrective and preventive actions; quality indicators; management support; continuous quality improvement |
Directly influences Sustainable POCT Quality and indirectly influences it through Process Control Effectiveness |
|
Independent Variable 2 |
Operator & Human Factors (OHF) |
Operator competency; formal training; competency assessment; professional experience; adherence to SOPs; understanding of device limitations; workload and staffing; communication; error reporting |
Directly influences Sustainable POCT Quality and indirectly influences it through Process Control Effectiveness |
|
Independent Variable 3 |
Technology & Operational Control Factors (TOCF) |
Equipment reliability; equipment verification; calibration; preventive maintenance; reagent and consumable management; equipment malfunction management; connectivity; service records; automation/data-management systems |
Directly influences Sustainable POCT Quality and indirectly influences it through Process Control Effectiveness |
|
Mediating Variable |
Process Control Effectiveness (PCE) |
Internal quality control; review of QC results; external quality assessment/proficiency testing; quality-indicator monitoring; root-cause analysis; corrective actions; evaluation of corrective-action effectiveness; process standardization; performance-trend analysis |
Mediates the relationships between QMS, OHF, TOCF and Sustainable POCT Quality |
|
Dependent Variable |
Sustainable POCT Quality (SPQ) |
Accuracy; reliability; clinically appropriate turnaround time; consistency across operators/locations; regulatory compliance; reduction of errors/nonconformities; continuous performance improvement; resilience to staffing/workload changes; overall sustainability |
Represents the overall quality and long-term sustainability of POCT services |
Objectives
The general objective of the study was to examine the effects of Quality Management System Strength, Operator & Human Factors, and Technology & Operational Control Factors on Sustainable Point-of-Care Testing (POCT) Quality in clinical laboratories in Pakistan, while assessing the influence and mediating role of Process Control Effectiveness in these relationships.
The specific objectives of the study were to determine the effects of Quality Management System Strength, Operator & Human Factors, and Technology & Operational Control Factors on Sustainable Point-of-Care Testing (POCT) Quality; to examine the effects of these three determinants on Process Control Effectiveness; to evaluate the influence of Process Control Effectiveness on Sustainable POCT Quality; and to assess whether Process Control Effectiveness mediated the relationships between Quality Management System Strength, Operator & Human Factors, and Technology & Operational Control Factors and Sustainable POCT Quality in clinical laboratories in Pakistan.
Research Questions
The study was guided by the overarching question of whether Quality Management System Strength, Operator & Human Factors, and Technology & Operational Control Factors influenced Sustainable POCT Quality directly and indirectly through Process Control Effectiveness. Specifically, it examined whether these three determinants were associated with Sustainable POCT Quality, whether they influenced Process Control Effectiveness, whether Process Control Effectiveness affected Sustainable POCT Quality, and whether Process Control Effectiveness mediated the relationships between the independent variables and Sustainable POCT Quality.
Hypotheses
The study tested the hypothesis that Quality Management System Strength, Operator & Human Factors, and Technology & Operational Control Factors were positively associated with Sustainable POCT Quality and that each of these determinants was also positively associated with Process Control Effectiveness. It further tested the hypothesis that Process Control Effectiveness positively influenced Sustainable POCT Quality and mediated the relationships between Quality Management System Strength, Operator & Human Factors, and Technology & Operational Control Factors and Sustainable POCT Quality. Accordingly, the study evaluated seven direct hypotheses concerning the relationships among the independent variables, Process Control Effectiveness, and Sustainable POCT Quality, together with three mediation hypotheses assessing the indirect effects of the three independent variables on Sustainable POCT Quality through Process Control Effectiveness.
MATERIALS AND METHODS:
Research Paradigm
This study is grounded in the positivist research paradigm, which assumes that reality is objective, measurable, and can be understood through empirical observation and statistical analysis. The positivist paradigm is appropriate because the study seeks to examine the relationships among clearly defined variables—Quality Management System Strength, Operator & Human Factors, Technology & Process Control Factors, Process Control Effectiveness, and Sustainable POCT Quality—using quantitative methods.
The research is deductive as hypotheses were formulated based on the existing theories such as Total Quality Management (TQM) Theory and Socio-Technical Systems Theory, and then tested by empirical data of lab professionals in public and private clinical lab in Pakistan.
The method used for collecting data is quantitative, cross sectional and the instrument used is structured questionnaire based on a five point likert scale. Data analysis will be performed by statistical analysis, including descriptive statistical, reliability analysis, confirmatory factor analysis (CFA) and structural equation modeling (SEM) using SmartPLS to analyze the direct and mediating relationship between the study variables.
The paradigm lays special focus on the objective, reliability and generalizability of the results obtained in the study so that the research community is able to find out the factors that affect the quality of the Point-of-Care Testing (POCT), and make evidence-based recommendations to improve the quality management practices and operational controls in clinical laboratories in Pakistan.
Table 2: Research Paradigm Summary
|
Component |
Description |
|
Research Paradigm |
Positivism |
|
Research Approach |
Deductive |
|
Research Method |
Quantitative |
|
Research Design |
Cross-sectional, Explanatory |
|
Data Collection |
Structured questionnaire (5-point Likert scale) |
|
Population |
Laboratory managers, quality officers, laboratory technologists, and POCT operators in public and private clinical laboratories in Pakistan |
|
Data Analysis |
Descriptive Statistics, Cronbach's Alpha, CFA, SEM (SmartPLS) |
|
Theoretical Foundation |
Total Quality Management (TQM) Theory and Socio-Technical Systems Theory |
Sample Size Determination
The required sample size was determined based on the requirements of multivariate analysis and Partial Least Squares Structural Equation Modeling (PLS-SEM). Because the proposed model included three independent variables, one mediating variable, and one dependent variable, with multiple hypothesized direct and indirect relationships, an adequate sample was required to provide sufficient statistical power for testing the structural model. The minimum sample size for the PLS-SEM analysis was considered using the commonly applied power-analysis principle for multiple regression, in which the required sample depends on the number of predictors, anticipated effect size, significance level, and statistical power. The sample size can be expressed as:
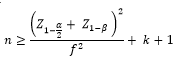
where N is the sample size needed, Z1−α/2 is the critical value for the selected significance level, Z1−β is the critical value for the desired statistical power, f2 is the expected effect size and k is the maximum number of predictors used in an endogenous construct. Based on the set α = 0.05, 80% power, an anticipated medium effect, and maximum number of predictors in the structural model, the study had a sufficient sample size to ensure the stability of the estimates of hypothesized relationships. A final sample size of 344 respondents was defined to include sufficient statistical power, allow for possible unusable responses and to sufficiently represent laboratory professionals from public and private healthcare institutions. In total, 344 completed and valid questionnaires were analysed.
Data Collection Instrument
The main data collection tool employed in the study was a structured, self-administered questionnaire. The conceptual framework and study objectives were used to develop the questionnaire which was designed to evaluate the major determinants of Sustainable Point-of-Care Testing (POCT) Quality in clinical laboratories in Pakistan namely organizational, human, technological and operational determinants. The questionnaire included questions related to the participants' demographic and professional characteristics, institutional and POCT-related information, Strength of the Quality Management System (QMS), Operator & Human Factors, Technology & Operational Control Factors, Process Control Effectiveness, and Sustainable POCT Quality. The main constructs were assessed with statements rated on a five point Likert scale (1, Strongly Disagree; 2, Disagree; 3, Neutral; 4, Agree; and 5, Strongly Agree). Before administering this questionnaire, it was reviewed for clarity, relevance, and consistency with the study objectives. A pilot assessment was carried out to detect unclear wording, to assess the instrument's feasibility and to assess the preliminary reliability of the instrument before the final data collection.
For the construct of the Quality Management System Strength the scope of assessment was to evaluate the extent to which the participating laboratories applied formal policies, controlled documentation, internal audits, quality indicators, corrective and preventive action and management support mechanisms, continuous improvement practices and included mechanisms for the management of POCT. Aspects that were evaluated by Operator & Human Factors include operator training, competency assessment, professional experience, standard operating procedures, workload, communication, and reporting of testing errors. Technology & Operational Control Factors evaluated equipment reliability, equipment verification, equipment calibration, equipment preventive maintenance, management of reagent and consumable materials, equipment malfunction, technological connectivity and monitoring of equipment performance. Process Control Effectiveness evaluated the implementation and effectiveness of internal quality control, external quality assessment, quality monitoring, investigation of nonconformities, corrective actions, process standardization and the evaluation of performance. The sustainable POCT Quality was evaluated using the following measures: accuracy, reliability, timeliness, regulatory compliance, consistency of performance, error reduction, and continuous quality improvement.
Data Analysis
The collected data were coded and analyzed using SPSS Statistics (version 27.0 for Windows). Descriptive statistics were run first to summarize the demographic, professional and institutional background of the respondents. Categorical variables were summarized in terms of frequencies and percentages, and continuous variables were summarized using appropriate measures of central tendency and dispersion, mostly means and standard deviations. Cronbach's alpha was used to determine internal consistency of the questionnaire constructs, acceptable internal reliability is defined as Cronbach's alpha value ≥ 0.70. Pearson's correlation analysis was then used to assess the directionality and strength of any relationship between the variables of Quality Management System Strength, Operator & Human Factors, Technology & Operational Control Factors, Process Control Effectiveness and Sustainable POCT Quality. Two-tailed tests were used to determine the statistical significance of the results and a p-value of <0.05 was regarded as statistically significant.
Since the study involved a number of latent constructs and the interrelationships were direct and indirect, the Partial Least Squares Structural Equation Modeling (PLS-SEM) was conducted using SmartPLS. Indicators loadings, Cronbach's alpha, composite reliability, average variance extracted (AVE) and heterotrait–monotrait (HTMT) ratios were used to determine the indicator reliability, internal consistency, convergent validity, and discriminant validity of the measurement model. The possible collinearity among the predictor constructs was evaluated using the variance inflation factor (VIF) values. Standardized path coefficients, coefficient of determination (R²), effect size (f²), and predictive relevance (Q²) were calculated in addition to appropriate model-fit assessment. The direct and indirect effects were estimated and statistically significant using bootstrapping with 5,000 resamples.The direct and indirect effects were estimated and statistically significant, taking the help of bootstrapping with 5,000 resamples. The indirect effect was assessed for each of the factors: Quality Management System Strength, Operator & Human Factors, and Technology & Operational Control Factors, between Sustainable POCT Quality and Process Control Effectiveness. An indirect effect was taken to be statistically significant if the 95% confidence interval for the indirect did not contain zero.
Ethical Considerations
The study was approved by the Institutional Review Board of PIQC and, if necessary, by the ethics or administrative committees of the healthcare institutions involved in the data collection. All participants gave informed written consent, including information about the purpose of the study, what they will be asked to do, how long they will spend, and that they can choose not to participate or withdraw at any time without penalty. The use of unique identification codes and avoiding unnecessary personal identifiers to ensure participant anonymity and confidentiality and reporting of the findings in an aggregate form. All questionnaires, electronic data, and approved institutional information was kept on password protected and secured devices and access to these was limited to the principal investigator and authorized supervisory personnel, and data were kept and destroyed as per institutional policy. The study entailed only a very low risk as no clinical interventions, experimental procedures, patient contact or collection of biological specimens were involved, and the main burden on the study consisted of the time taken to fill out the questionnaire. There was no financial or personal conflict of interest and this study was not a joint study or investigation between participating laboratories or diagnostic companies. Access to secondary institutional quality information (such as quality control records, external quality assessment results, audit reports, equipment maintenance records, and corrective action documentation) was permitted for research only, not for use with any patients, and without patient identifiers. The study followed the recommendations of National Bioethics Committee of Pakistan, institutional ethical clearance requirements and wherever applicable, principles of quality management and documentation as adopted by the ISO 15189:2022. It also ensured the rights and privacy of the participants, confidentiality and voluntary participation throughout the study.
Limitations and Delimitations of the Study
Limitations of the Study: The current study used a cross-sectional research design, which allowed the collection of data in one time point, so the associations between the Strength of the Quality Management System, Operator & Human Factors, Technology & Operational Control Factors, Process Control Effectiveness, and Sustainable POCT Quality were examined; however, causal relationships could not be definitively determined and changes in POCT quality or quality-management practices over time could not be evaluated. Questionnaires were primarily self-administered, which may have led to a response bias, social desirability bias, and a subjectivity when answering the questions, as the participants might have overstated the quality of their institutional practices and might have answered the questions as they thought the institution expected them to answer; anonymous data collection and standardized questionnaire administration were used to minimize these biases, however not fully eliminate them. Due to the study conducted on selected clinical laboratories (public and private) of Pakistan, the findings might not be fully generalizable for all clinical laboratories, including small rural clinical laboratories, primary healthcare clinics, as well as non-laboratory settings where POCT was applied, as various differences in the institutional resources, staffing, infrastructure, and quality-management systems might have contributed to the differences in applicability of the findings across these various clinical laboratories. Geographic scope and the number of laboratories involved were also constrained by resource and time limitations and, as noted, the study included 344 respondents representing relevant public and private healthcare sectors, but may not have fully represented the whole population of POCT practitioners and institutions across Pakistan, with some geographical or institutional differences not being fully captured. Another limitation was access to objective institutional quality records; the study used primarily respondents' perceptions of institutional quality where objective operational data were unavailable, due to institutional confidentiality policies and because some participating laboratories were either unwilling or unable to provide detailed quality-management records such as internal quality-control records, external quality assessment results, audit reports, equipment maintenance records, and documented corrective actions. Lastly, as a result of the study's pre-established conceptual framework, certain external factors that were known to have an impact on sustainable POCT quality were not directly explored, such as organizational culture, institutional leadership, government regulations, financial resources, trained personnel and procurement policies, as well as other characteristics of the healthcare system.
The aim of the study was to restrict the study to clinical laboratories implementing clinical POCT in public and private healthcare sectors in Pakistan to ensure that study population was institutions where the clinical POCT was routinely performed and quality-management practices could be meaningfully assessed. The primary respondents were the laboratory managers, quality officers, laboratory technologists and POCT operators, who were directly involved in the implementation of POCT, quality management, operational procedures and monitoring, whereas the healthcare professionals who were not directly involved in POCT activities were excluded. The investigation focussed on four major constructs: Quality Management System Strength, Operator & Human Factors, Technology & Operational Control Factors, and Process Control Effectiveness, reflecting the elements of an organization, operators, human factors, technology, and operational control factors which were considered relevant to sustainable POCT quality. A structured five-point Likert scale questionnaire was used to assess Sustainable POCT Quality, which was used as a mediating variable between the independent constructs of the study and Process Control Effectiveness. In this study, quantitative research methods were used and the data were analyzed using SPSS and SmartPLS with descriptive, reliability, Pearson's correlation analysis, and Partial Least Squares Structural Equation Modeling (PLS-SEM). No qualitative research methods were employed, such as interviews, focus groups and direct observation assessments. Lastly, the study was conducted within a predetermined 10-month period and was limited to existing quality-management practices and operational controls to not implement or evaluate a new quality-management system, trainings, technological intervention or process-control intervention.
Statistical Analysis
The data was entered, coded and analyzed using IBM SPSS Statistics and SmartPLS. Demographic, professional and institutional characteristics of the respondents were summarized using descriptive statistics. Frequencies and percentages were used to display categorical variables, and means and standard deviations were used to display continuous variables. The questionnaire constructs were evaluated for internal consistency using Cronbach's alpha with the value of ≥0.70 being deemed acceptable. Pearson's correlation analysis was conducted to assess the direction and intensity of the relationships between the components of Quality Management System Strength, Operator & Human Factors, Technology & Operational Control Factors, Process Control Effectiveness, and Sustainable POCT Quality. The correlation coefficients were evaluated by their size and statistical significance and a p value <0.05 (two-tailed) was regarded as statistically significant.
After using this form of multidimensional conceptual framework, a Partial Least Squares Structural Equation Modeling (PLS-SEM) was then applied to evaluate the measurement and structural model using SmartPLS software. Indicator loadings, Cronbach's alpha, composite reliability, average variance extracted (AVE), and heterotrait–monotrait (HTMT) ratios were used to test the measurement model for reliability and convergent and discriminant validity. The variance inflation factor (VIF) was used to check for collinearity. Standardized Path coefficients (β), coefficient of determination (R²), effect size (f²), predictive relevance (Q²), and relevant model-fit assessment were used to evaluate the structural model. The hypothesized direct and indirect effects were defined as significant and calculated their confidence intervals using bootstrapping with 5,000 resamples. The indirect effect of the relationship between the variables was tested by examining the mediating role of Process Control Effectiveness between Quality Management System Strength, Operator & Human Factors, and Technology & Operational Control Factors on Sustainable POCT Quality. A p value less than 0.05 was considered to be statistically significant, and a 95% confidence interval which excluded zero was taken as evidence for a statistically significant indirect effect.
RESULTS:
Among the 344 respondents, the mean age was 35.74 ± 5.28 years, with males comprising 64.2% (n=221) and females 35.8% (n=123). Technicians represented the largest professional group (39.8%, n=137), followed by nurses (14.2%, n=49), while 45.1% (n=155) had a bachelor's degree and 30.5% (n=105) had a master's/MPhil qualification. Regarding professional experience, 36.9% (n=127) had 1–5 years of experience, whereas 25.6% (n=88) had 6–10 years. POCT experience was most commonly 1–3 years (32.8%, n=113). Respondents were equally distributed between public and private institutions, with 172 (50.0%) participants from each sector.
Table 3. Sociodemographic and Professional Characteristics of Respondents (N = 344)
|
Characteristic |
Category |
n (%) |
|
Age, years |
Mean ± SD |
35.74 ± 5.28 |
|
Sex |
Male |
221 (64.2) |
|
Female |
123 (35.8) |
|
|
Professional designation |
Manager |
29 (8.4) |
|
Quality Officer |
25 (7.3) |
|
|
Technician |
137 (39.8) |
|
|
Pathologist |
15 (4.4) |
|
|
Physician |
25 (7.3) |
|
|
Nurse |
49 (14.2) |
|
|
POCT Coordinator |
25 (7.3) |
|
|
Biomedical Engineer |
15 (4.4) |
|
|
Other |
24 (7.0) |
|
|
Highest qualification |
Diploma |
13 (3.8) |
|
Bachelor |
155 (45.1) |
|
|
Master/MPhil |
105 (30.5) |
|
|
PhD/FCPS/Equivalent |
52 (15.1) |
|
|
Other |
19 (5.5) |
|
|
Professional experience |
<1 year |
20 (5.8) |
|
1–5 years |
127 (36.9) |
|
|
6–10 years |
88 (25.6) |
|
|
11–15 years |
73 (21.2) |
|
|
>15 years |
36 (10.5) |
|
|
POCT experience |
<1 year |
31 (9.0) |
|
1–3 years |
113 (32.8) |
|
|
4–6 years |
98 (28.5) |
|
|
7–10 years |
71 (20.6) |
|
|
>10 years |
31 (9.0) |
|
|
Institution sector |
Public |
172 (50.0) |
|
Private |
172 (50.0) |
The participating institutions showed representation from all major regions, with the highest proportion of respondents from Punjab (37.5%, n=129), followed by Khyber Pakhtunkhwa (25.3%, n=87) and Sindh (19.8%, n=68). Most institutions had 11–25 POCT operators (32.0%, n=110) or 26–50 operators (27.3%, n=94). A POCT management committee was reported by 59.0% (n=203) of respondents, while written POCT SOPs were available in 77.3% (n=266) of institutions. Regular participation in external quality assessment/proficiency testing was reported by 48.5% (n=167), whereas POCT systems were fully integrated with information systems in only 28.2% (n=97) of institutions.
Table 4. Institutional and POCT Characteristics of Respondents (N = 344)
|
Characteristic |
Category |
n (%) |
|
Province/territory |
Punjab |
129 (37.5) |
|
Sindh |
68 (19.8) |
|
|
Khyber Pakhtunkhwa |
87 (25.3) |
|
|
Balochistan |
18 (5.2) |
|
|
Islamabad |
24 (7.0) |
|
|
Gilgit-Baltistan |
5 (1.5) |
|
|
AJK |
13 (3.8) |
|
|
Number of POCT operators |
1–10 |
71 (20.6) |
|
11–25 |
110 (32.0) |
|
|
26–50 |
94 (27.3) |
|
|
51–100 |
46 (13.4) |
|
|
>100 |
23 (6.7) |
|
|
POCT management committee |
Yes |
203 (59.0) |
|
No |
83 (24.1) |
|
|
Don't know |
58 (16.9) |
|
|
Written POCT SOPs |
Yes |
266 (77.3) |
|
No |
54 (15.7) |
|
|
Don't know |
24 (7.0) |
|
|
EQA/PT participation |
Regularly |
167 (48.5) |
|
Occasionally |
87 (25.3) |
|
|
No |
45 (13.1) |
|
|
Don't know |
45 (13.1) |
|
|
POCT connectivity |
Fully integrated |
97 (28.2) |
|
Partially integrated |
139 (40.4) |
|
|
Not integrated |
89 (25.9) |
|
|
Don't know |
19 (5.5) |
All major study constructs demonstrated mean scores above the neutral midpoint of the five-point Likert scale. Sustainable POCT Quality had the highest mean score (3.577 ± 0.607), followed by Process Control Effectiveness (3.556 ± 0.575) and Quality Management System Strength (3.520 ± 0.609). Operator & Human Factors had a mean score of 3.480 ± 0.594, while Technology & Operational Control Factors had the lowest mean score (3.437 ± 0.625), indicating comparatively lower perceived performance in technological and operational controls.
Table 5. Descriptive Statistics of Study Constructs
|
Construct |
No. of items |
Mean ± SD |
|
Quality Management System Strength |
9 |
3.520 ± 0.609 |
|
Operator & Human Factors |
9 |
3.480 ± 0.594 |
|
Technology & Operational Control Factors |
9 |
3.437 ± 0.625 |
|
Process Control Effectiveness |
9 |
3.556 ± 0.575 |
|
Sustainable POCT Quality |
9 |
3.577 ± 0.607 |
For Quality Management System Strength, the highest-rated items concerned documentation of corrective and preventive actions (3.61 ± 0.95) and the establishment of continuous quality improvement (3.60 ± 0.96). Among Operator & Human Factors, the highest mean was observed for prompt reporting of errors and nonconformities (3.56 ± 0.92), while formal training before operator authorization had a mean of 3.45 ± 0.90. Overall, the findings indicated moderately positive perceptions of both quality-management practices and operator-related controls.
Table 6. Item-Level Descriptive Statistics for Quality Management System Strength and Operator & Human Factors
|
Construct |
Item |
Mean ± SD |
|
QMS |
Clearly defined POCT quality policy |
3.46 ± 0.90 |
|
Responsibilities clearly assigned |
3.52 ± 0.97 |
|
|
Current and controlled POCT SOPs |
3.45 ± 0.88 |
|
|
POCT documents and records maintained |
3.49 ± 0.91 |
|
|
Internal audits assess POCT compliance |
3.52 ± 0.87 |
|
|
Corrective/preventive actions documented |
3.61 ± 0.95 |
|
|
Quality indicators regularly reviewed |
3.54 ± 0.92 |
|
|
Management provides adequate support/resources |
3.49 ± 0.94 |
|
|
Continuous quality improvement established |
3.60 ± 0.96 |
|
|
OHF |
Formal training before authorization |
3.45 ± 0.90 |
|
Documented competency assessment |
3.50 ± 0.91 |
|
|
Competency reassessed periodically |
3.47 ± 0.93 |
|
|
Operators follow approved SOPs |
3.46 ± 0.93 |
|
|
Operators understand device limitations/errors |
3.47 ± 0.93 |
|
|
Additional training after quality problems |
3.49 ± 0.92 |
|
|
Workload/staffing permits correct procedures |
3.47 ± 0.94 |
|
|
Effective operator–laboratory communication |
3.45 ± 0.94 |
|
|
Operators report errors/nonconformities promptly |
3.56 ± 0.92 |
The Technology & Operational Control Factors showed moderate ratings across all assessed domains. The highest mean score was observed for appropriate equipment selection (3.50 ± 0.94) and appropriate connectivity/data-management mechanisms (3.50 ± 0.94). The lowest scores were observed for device verification before routine use (3.39 ± 0.98) and prompt management of equipment malfunctions (3.39 ± 0.92), suggesting potential areas for strengthening equipment verification and operational response mechanisms.
Table 7. Item-Level Descriptive Statistics for Technology & Operational Control Factors
|
Item |
Mean ± SD |
|
Equipment appropriately selected |
3.50 ± 0.94 |
|
Devices verified before routine use |
3.39 ± 0.98 |
|
Equipment calibration/calibration verification performed |
3.44 ± 0.94 |
|
Preventive maintenance performed according to schedule |
3.45 ± 0.90 |
|
Reagents/consumables appropriately stored |
3.41 ± 0.97 |
|
Equipment malfunction documented and managed promptly |
3.39 ± 0.92 |
|
Appropriate connectivity/data-management mechanisms |
3.50 ± 0.94 |
|
Equipment/service records regularly reviewed |
3.41 ± 0.94 |
|
Technology reduces manual/data-entry errors |
3.43 ± 0.97 |
Process Control Effectiveness demonstrated generally positive ratings, with the highest mean reported for review of QC results before continuation of testing (3.63 ± 0.93), followed by standardization of POCT processes across locations and operators (3.61 ± 0.93). Regular review of EQA/proficiency-testing results had a mean of 3.55 ± 0.89, while evaluation of corrective-action effectiveness had a mean of 3.53 ± 0.98. These findings suggested relatively strong implementation of routine quality-control and process-standardization activities.
Table 8. Item-Level Descriptive Statistics for Process Control Effectiveness
|
Item |
Mean ± SD |
|
Internal quality control performed at predefined intervals |
3.51 ± 0.90 |
|
QC results reviewed before continuation of testing |
3.63 ± 0.93 |
|
EQA/proficiency-testing results systematically reviewed |
3.55 ± 0.89 |
|
Quality indicators routinely monitored |
3.54 ± 0.91 |
|
POCT nonconformities investigated for root causes |
3.55 ± 0.94 |
|
Corrective actions implemented promptly |
3.55 ± 0.90 |
|
Effectiveness of corrective actions evaluated |
3.53 ± 0.98 |
|
POCT processes standardized across locations/operators |
3.61 ± 0.93 |
|
POCT performance trends regularly analyzed |
3.54 ± 0.93 |
Sustainable POCT Quality showed consistently positive ratings across its dimensions. The highest-rated item was the ability to maintain quality despite staffing or workload changes (3.62 ± 0.97), while the overall sustainable POCT system item also recorded a mean of 3.62 ± 0.89. Minimization of POCT errors and nonconformities over time had a mean of 3.60 ± 0.93, and compliance with quality and regulatory requirements scored 3.58 ± 0.93, indicating generally favorable perceptions of sustainable POCT performance.
Table 7. Item-Level Descriptive Statistics for Sustainable POCT Quality
|
Item |
Mean ± SD |
|
POCT results consistently reliable for clinical decisions |
3.55 ± 0.91 |
|
POCT results demonstrate acceptable accuracy |
3.54 ± 0.94 |
|
Results provided within clinically appropriate turnaround time |
3.56 ± 0.93 |
|
Performance consistent across operators/locations |
3.55 ± 0.91 |
|
Services meet quality and regulatory requirements |
3.58 ± 0.93 |
|
POCT errors/nonconformities minimized over time |
3.60 ± 0.93 |
|
Institution continuously improves POCT performance |
3.57 ± 0.97 |
|
Quality maintained despite staffing/workload changes |
3.62 ± 0.97 |
|
Overall sustainable POCT system |
3.62 ± 0.89 |
All study constructs demonstrated statistically significant positive correlations with Sustainable POCT Quality (p < 0.001). The strongest association was observed between Quality Management System Strength and Sustainable POCT Quality (r = 0.633), followed by Operator & Human Factors (r = 0.628) and Technology & Operational Control Factors (r = 0.599). Process Control Effectiveness was also positively correlated with Sustainable POCT Quality (r = 0.608). Among the independent variables, Quality Management System Strength was positively correlated with Technology & Operational Control Factors (r = 0.616) and Operator & Human Factors (r = 0.579), indicating substantial interrelationships among the determinants of sustainable POCT quality.
Table 8. Pearson Correlations Among Study Constructs
|
Variable |
QMS |
OHF |
TOCF |
PCE |
SPQ |
|
QMS |
1.000 |
0.579** |
0.616** |
0.568** |
0.633** |
|
OHF |
0.579** |
1.000 |
0.611** |
0.498** |
0.628** |
|
TOCF |
0.616** |
0.611** |
1.000 |
0.559** |
0.599** |
|
PCE |
0.568** |
0.498** |
0.559** |
1.000 |
0.608** |
|
SPQ |
0.633** |
0.628** |
0.599** |
0.608** |
1.000 |
Note: QMS = Quality Management System Strength; OHF = Operator & Human Factors; TOCF = Technology & Operational Control Factors; PCE = Process Control Effectiveness; SPQ = Sustainable POCT Quality. p < 0.01 (two-tailed). N = 344. All correlations were statistically significant at the 0.01 level. The strongest association was between QMS and SPQ (r = 0.633), while the weakest was between OHF and PCE (r = 0.498).
DISCUSSION:
The present study evaluated the determinants of sustainable Point-of-Care Testing (POCT) quality among 344 laboratory professionals working in public and private clinical laboratories in Pakistan. Overall, the findings demonstrated moderately favorable perceptions across all major study constructs, with Sustainable POCT Quality recording the highest mean score (3.577 ± 0.607), followed by Process Control Effectiveness (3.556 ± 0.575), Quality Management System Strength (3.520 ± 0.609), Operator & Human Factors (3.480 ± 0.594), and Technology & Operational Control Factors (3.437 ± 0.625). These findings suggested that although POCT quality-management practices were generally established, technological and operational controls remained comparatively weaker. This pattern was consistent with international literature emphasizing that POCT quality depends on the coordinated implementation of governance, competent personnel, quality assurance, equipment management, and continuous monitoring rather than on the testing device alone. Recent guidance has similarly emphasized that training, quality assurance, internal quality control (IQC), external quality assessment (EQA), and appropriate device selection are fundamental components of reliable POCT services. (Anne and Sandberg, 2024; Nichols et al., 2020).
The relatively high score for Quality Management System Strength (3.520 ± 0.609) indicated that respondents generally perceived the presence of quality policies, documentation, internal audits, corrective actions, and continuous improvement mechanisms within their institutions. This finding was important because POCT is performed in decentralized environments where maintaining laboratory-level governance can be difficult. International recommendations have identified quality policies, management review, audits, documentation, and multidisciplinary oversight as important components of POCT governance (Pernet et al., 2012). Furthermore, evidence from POCT quality-improvement studies has shown that systematic quality management involving IQC and EQA can improve analytical performance over time. (Price et al., 2018) The current finding therefore supported the concept that stronger institutional quality systems are likely to provide the organizational foundation necessary for sustainable POCT performance.
The Operator & Human Factors construct had a mean score of 3.480 ± 0.594, indicating moderately positive perceptions regarding operator competency, training, adherence to SOPs, communication, and error reporting. The finding was consistent with previous evidence showing that personnel competency is a critical determinant of POCT accuracy because many POCT procedures are performed by nurses, physicians, or other non-laboratory personnel. A systematic review found that structured training interventions improved nurses' competence in POCT, particularly when laboratory professionals were involved in training and support. (Liikanen, E., & Lehto, L. (2013). Similarly, AACC guidance has emphasized that a single training event is insufficient and that ongoing competency assessment, training, and laboratory support are needed to maintain POCT performance. (Nichols et al., 2020) The present findings therefore reinforced the importance of treating operator competency as a continuing quality-management responsibility rather than a one-time training requirement.
The relatively lower mean for Technology & Operational Control Factors (3.437 ± 0.625) was particularly noteworthy. Although equipment selection and connectivity received comparatively favorable ratings, equipment verification and management of equipment malfunction received lower scores. This finding suggested that technological availability did not necessarily translate into fully optimized operational control. Previous recommendations have emphasized that POCT quality assurance should encompass device selection, initial and ongoing verification, reagent and quality-control management, operator management, and documentation. (Venner et al., 2021). Similarly, studies of POCT quality indicators have identified calibration, analyzers, consumables, reagents, connectivity, and equipment-related problems as important sources of quality deviations. (Oliver et al., (2020). Thus, the lower score observed in the present study may reflect the practical challenge of maintaining equipment and technological systems consistently across decentralized testing locations.
Process Control Effectiveness recorded a relatively high mean score (3.556 ± 0.575), with particularly favorable ratings for reviewing QC results before continuation of testing (3.63 ± 0.93) and standardizing POCT processes across operators and locations (3.61 ± 0.93). These findings were consistent with the established role of IQC, EQA, quality indicators, corrective actions, and process standardization in POCT quality assurance. A large College of American Pathologists Q-Probes study involving 106 institutions reported high levels of documentation of operator training, operator identification, and QC events, although deficiencies remained in some aspects of POCT practice. (Dyhdalo et al., 2014). Similarly, evidence from an ISO 22870-accredited POCT network showed that continuous monitoring of quality indicators enabled identification of deviations involving patient identification, consumables, analyzers, calibration, IQC/EQA, connectivity, and operator identification, allowing corrective action to be implemented. (Oliver et al., 2020) These findings support the present observation that effective process monitoring can serve as an important mechanism for maintaining sustainable POCT quality.
The highest overall construct score was observed for Sustainable POCT Quality (3.577 ± 0.607). Within this construct, maintaining quality despite staffing or workload changes and the overall sustainability of the POCT system both recorded mean scores of 3.62, while minimization of errors and nonconformities over time scored 3.60 ± 0.93. These findings suggested that respondents generally considered their POCT services capable of maintaining acceptable performance under routine operational pressures. This was broadly consistent with evidence that structured quality-management interventions can improve POCT performance over time. A systematic review of POCT quality improvement found that regular participation in EQA and implementation of IQC were associated with improved analytical performance. (Price et al., 2017). More recent literature has likewise concluded that appropriate quality assurance can improve POCT measurement quality and potentially contribute to better patient outcomes. (Anne and Sandberg, 2024).
The correlation analysis provided further support for the proposed conceptual framework. Quality Management System Strength showed the strongest correlation with Sustainable POCT Quality (r = 0.633, p < 0.001), followed by Operator & Human Factors (r = 0.628, p < 0.001), Process Control Effectiveness (r = 0.608, p < 0.001), and Technology & Operational Control Factors (r = 0.599, p < 0.001). These positive associations indicated that stronger organizational quality systems, better operator-related practices, stronger technological controls, and more effective process-control mechanisms were all associated with better perceived sustainable POCT quality. The findings were compatible with the broader POCT literature, which describes quality as a multidimensional outcome dependent on governance, staff competency, technology, quality control, and continuous monitoring. (Brun et al., 2021). Importantly, the correlation between Quality Management System Strength and Sustainable POCT Quality was stronger than the associations involving the other determinants, highlighting the potentially central role of institutional quality governance.
The correlation between Process Control Effectiveness and Sustainable POCT Quality (r = 0.608, p < 0.001) was also substantial and supported the proposed mediating role of process control. Although correlation alone could not establish mediation or causality, the finding suggested that institutions with stronger QC, monitoring, corrective-action, and standardization processes tended to report better sustainable POCT quality. This interpretation was supported by previous research identifying quality indicators as essential tools for monitoring the pre-analytical, analytical, and post-analytical phases of POCT and for supporting continuous quality improvement. (Brun et al., 2021) The finding also supported the theoretical basis of the study, in which organizational resources and operator and technological capabilities were expected to translate into sustainable quality partly through effective operational processes.
The Cronbach's alpha of 0.840 for the Quality Management System Strength scale demonstrated good internal consistency and indicated that its nine items measured a coherent underlying construct. This finding strengthened confidence in the measurement of QMS strength within the present study. However, reliability values for the remaining constructs should be reported after their respective Cronbach's alpha analyses have been completed rather than inferred from the present results.
These findings supported the central premise of the study that sustainable POCT quality was not determined by a single factor but reflected the interaction of quality management, human competency, technology, and operational process control. The comparatively stronger association of QMS with sustainable POCT quality emphasized the importance of institutional governance, while the substantial correlations involving operator factors, technology, and process control demonstrated that these domains should be addressed together. This integrated interpretation was consistent with contemporary POCT guidance, which recommends combining operator competency, quality management, equipment verification, IQC/EQA, quality indicators, and continuous monitoring within a coordinated POCT program. Nevertheless, because the present study used a cross-sectional questionnaire-based design, the observed associations should be interpreted as relationships rather than definitive causal effects. Further analysis using PLS-SEM would be required to formally test the hypothesized direct pathways and determine whether Process Control Effectiveness significantly mediated the relationships between the three independent constructs and Sustainable POCT Quality.
REFERENCES:
1. Brun, M., Füzéry, A. K., Henschke, B., Rozak, K., & Venner, A. A. (2021). Identifying sources of error and selecting quality indicators for point of care testing. Practical laboratory medicine, 25, e00216. https://doi.org/10.1016/j.plabm.2021.e00216
2. Bukhari, M. H.., Siddiqui, A., & Khan, S. A. (2023). Adoption of point-of-care testing in emergency and primary care settings in Lahore, Pakistan. Journal of Health and Rehabilitation Research, 3(2), 112–118.
3. Dyhdalo, K. S., Howanitz, P. J., Wilkinson, D. S., Souers, R. J., & Jones, B. A. (2014). Documentation of quality control and operator training at point-of-care testing: a College of American Pathologists Q-Probes study of 106 institutions. Archives of pathology & laboratory medicine, 138(11), 1444–1448. https://doi.org/10.5858/arpa.2013-0552-CP
4. International Organization for Standardization. (2016). ISO 22870:2016 Point-of-care testing (POCT)—Requirements for quality and competence. Geneva, Switzerland: ISO.
5. International Organization for Standardization. (2022). ISO 15189:2022 Medical laboratories—Requirements for quality and competence. Geneva, Switzerland: ISO.
6. Islam, M.. (2024). Assessment of quality assurance procedures of diagnostic equipment at clinical laboratories of tertiary care hospitals in Karachi, Pakistan (Master's thesis). Aga Khan University.
7. Jafri, L.., Ahmed, S., Majid, H., Ghani, F., Pillay, T., Khan, A. H., Siddiqui, I., Shakeel, S., Ahmed, S., Azeem, S., & Khan, A. (2023). A framework for implementing best laboratory practices for non-integrated point-of-care tests in low-resource settings. Electronic Journal of the International Federation of Clinical Chemistry and Laboratory Medicine, 34(2), 110–122.
8. Khan, A. H.., Shakeel, S.., Hooda, K.., Siddiqui, K.., & Jafri, L.. (2019). Best practices in the implementation of a point-of-care testing program: Experience from a tertiary care hospital in a developing country. Electronic Journal of the International Federation of Clinical Chemistry and Laboratory Medicine, 30(3), 288–302.
9. Liikanen, E., & Lehto, L. (2013). Training of nurses in point-of-care testing: a systematic review of the literature. Journal of clinical nursing, 22(15-16), 2244–2252. https://doi.org/10.1111/jocn.12235
10. Miyachi, H.. (2016). Point-of-care testing: Current status and future perspectives. Rinsho Byori (Japanese Journal of Clinical Pathology), 64(10), 1181–1188.
11. Nagel, M.., & Luppa, P. B.. (Eds.). (2023). Point-of-care testing in hospitals and primary care. Deutsches Ärzteblatt International.
12. Nichols, J. H., Alter, D., Chen, Y., Isbell, T. S., Jacobs, E., Moore, N., & Shajani-Yi, Z. (2020). AACC guidance document on management of point-of-care testing. The Journal of Applied Laboratory Medicine, 5(4), 762-787. https://doi.org/10.1093/jalm/jfaa059
13. Nichols, J. H.. (2021). Point-of-care testing. In Tietz Textbook of Laboratory Medicine (7th ed.). Elsevier.
14. Oliver, P., Fernandez-Calle, P., Mora, R., Diaz-Garzon, J., Prieto, D., Manzano, M., Dominguez, I., & Buño, A. (2020). Real-world use of key performance indicators for point-of-Care Testing network accredited by ISO 22870. Practical laboratory medicine, 22, e00188. https://doi.org/10.1016/j.plabm.2020.e00188
15. Oliver, P.., Fernandez-Calle, P.., & Buño, A.. (2021). POCT accreditation ISO 15189 and ISO 22870: Making the point. Electronic Journal of the International Federation of Clinical Chemistry and Laboratory Medicine, 32(2), 131–139.
16. Pernet, P., Szymanowicz, A., Oddoze, C., Vassault, A., Annaix, V., Gruson, A., Boisson, M., & membres du sous-groupe biologie délocalisée (2012). Recommandations pour la mise en place d'un système de management de la qualité des examens de biologie médicale délocalisés [Guidelines for point-of-care testing quality management according to ISO 22870]. Annales de biologie clinique, 70 Spec No 1, 185–205. https://doi.org/10.1684/abc.2012.0680
17. Pernet, P.., et al. (2012). International recommendations for quality management of point-of-care testing. Clinical Chemistry and Laboratory Medicine, 50(6), 943–953.
18. Plebani, M.. (2018). Quality indicators in laboratory medicine: A fundamental tool for quality management. Clinical Biochemistry, 57, 1–2.
19. Price, C. P., Smith, I., & Van den Bruel, A. (2018). Improving the quality of point-of-care testing. Family practice, 35(4), 358-364. https://doi.org/10.1093/fampra/cmx120
20. Rabbani, F.., & Abbasi, I. N.. (2017). Accreditation and healthcare quality assurance in Pakistan: A desk review. Pakistan Journal of Public Health, 7(3), 152–160.
21. Shah, S. S. H.., Soomro, M. H., Lashari, U. G., et al. (2017). Point-of-care testing facilitates screening and treatment for anaemia in women and children in rural Pakistan. Australian Journal of Rural Health, 25(2), 112–118.
22. Shaw, J. L. V.. (2016). Practical challenges related to point-of-care testing. Practical Laboratory Medicine, 4, 22–29.
23. Stavelin, Anne, and Sverre Sandberg. “Analytical performance specifications and quality assurance of point-of-care testing in primary healthcare.” Critical reviews in clinical laboratory sciences vol. 61,3 (2024): 164-177. doi:10.1080/10408363.2023.2262029
24. Venner, A. A., Beach, L. A., Shea, J. L., Knauer, M. J., Huang, Y., Fung, A. W. S., Dalton, J., Provencal, M., & Shaw, J. L. V. (2021). Quality assurance practices for point of care testing programs: Recommendations by the Canadian society of clinical chemists point of care testing interest group. Clinical biochemistry, 88, 11–17. https://doi.org/10.1016/j.clinbiochem.2020.11.008
25. World Health Organization. (2023). Laboratory quality management system: Handbook. Geneva, Switzerland: WHO.