Maternal Knowledge Of Neonatal Danger Signs And Health Seeking Practices: A Community Based Cross-Sectional Study In Lucknow.
- Beg S , Assistant Professor, Department of Paediatrics Career Institute of Medical Sciences and Hospital, Lucknow, Uttar Pradesh, India
- Rehman MH , Professor & Head, Department of Physiology, Integral Institute of Medical Sciences and Research, Lucknow, Uttar Pradesh, India
- Abbas J , Professor & Head Department of Paediatrics, Career Institute of Medical Sciences and Hospital, Lucknow, Uttar Pradesh, India
- Siddiqui A M , Associate Professor, Department of Physiology, Career Institute of Medical Sciences and Hospital, Lucknow, Uttar Pradesh, India
- Qureshi J , Junior Resident, Department of Paediatrics, Career Institute of Medical Sciences and Hospital, Lucknow, Uttar Pradesh, India.
- Kheizran B , Junior Resident, Department of Paediatrics, Career Institute of Medical Sciences and Hospital, Lucknow, Uttar Pradesh, India.
Article Information:
Abstract:
Background: Early identification of neonatal danger signs is crucial for preventing newborn morbidity and mortality. Objective: To assess maternal knowledge, perception, experience, and health-seeking behaviour regarding neonatal danger signs, and to determine factors associated with good maternal knowledge. Methods: A community-based cross-sectional study among 372 mothers collected data on socio-demographic characteristics, knowledge of neonatal danger signs, and health service utilization. Chi-square tests were used to determine associations. Results: Most mothers had secondary education (48.7%), while 25.8% had no education. High-grade fever (91.9%), convulsions (85.5%), and poor feeding (74.2%) were the most recognized neonatal danger signs. Only 54.3% of mothers had good knowledge. Factors significantly associated with good knowledge included maternal education (p=0.001), income (p=0.001), maternal occupation (p=0.001), ANC visits (p=0.001), PNC visits (p=0.009), husband’s involvement (p=0.001), and counselling on danger signs (p=0.029). Conclusion: Maternal knowledge was moderate, with significant gaps in recognizing subtle but critical neonatal danger signs. Strengthening counselling during ANC/PNC visits and promoting family involvement are essential to improve early detection and reduce neonatal morbidity and mortality.
Keywords:
Article :
INTRODUCTION:
Neonatal mortality continues to pose a major global health challenge, particularly in low- and middle-income countries where early danger signs often go unnoticed or untreated (3,4). Many neonatal deaths occur due to preventable or treatable causes when recognized early. The World Health Organization (WHO) identifies key neonatal danger signs that require immediate medical attention (1,2). Maternal knowledge of these signs is essential for prompt care-seeking behaviour and timely intervention (7,9,11). However, studies from Ethiopia, Nigeria, and South Asia show that maternal knowledge is often inadequate, influenced by educational level, access to maternal health services, and socio-economic factors (7,10,11). Understanding mothers’ awareness, prior experiences, and the socio-demographic factors influencing knowledge is crucial in developing targeted interventions to reduce neonatal morbidity and mortality (6). This study assesses maternal knowledge, perception, and experiences regarding neonatal danger signs, healthcare-seeking behaviours, and the determinants of good knowledge.
MATERIALS AND METHODS:
Study Design-A community-based cross-sectional study was conducted among 372 mothers.
Data Collection-A structured, pretested, interviewer-administered questionnaire was used to obtain information on:
1. socio-demographic characteristics
2. maternal knowledge of neonatal danger signs
3. prior experience with danger signs
4. health-seeking practices
5. ANC and PNC service utilization
6. counselling after delivery
Outcome Variable- Maternal knowledge was categorized as good or poor based on the number of correctly identified WHO neonatal danger signs relative to the median score(1,2).
Data Analysis- Using SPSS v29 software, data were analysed. Frequencies and percentages summarized the data. Chi-square tests examined associations between maternal knowledge and independent variables. A p-value <0.05 was considered statistically significant.
Ethical clearance was obtained from the institutional ethical review committee. A written informed consent was taken from each of the study participants after a clear explanation of the aim of the study.
RESULTS:
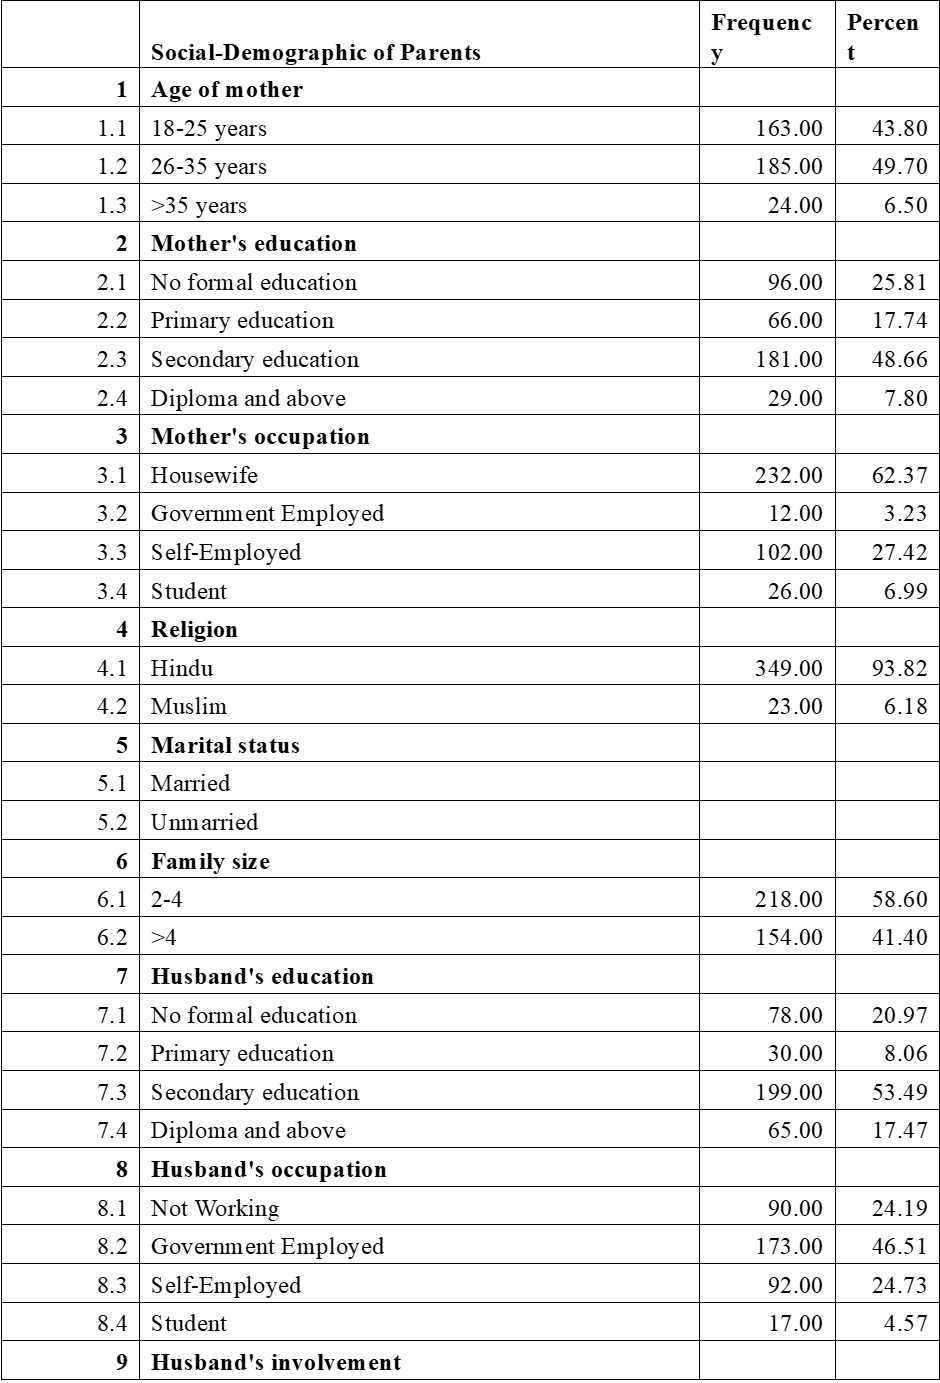
Among the 372 mothers surveyed, the socio-demographic profile indicated that nearly half (49.7%) were aged between 26 and 35 years. Educational attainment varied, with 48.7% having a secondary education, though a significant minority of 25.8% lacked formal schooling. The majority were housewives (62.4%) and Hindu (93.8%), with most families being relatively small (58.6% had 2–4 members). A positive trend in family dynamics was noted by the high rate of husband involvement in newborn care (69.4%), corresponding with husbands commonly having a secondary education (53.5%). Knowledge of neonatal danger signs was high for universally recognized acute symptoms such as high-grade fever (91.9%), convulsions (85.5%), poor sucking/feeding (74.2%), and unconsciousness (71.0%). Conversely, knowledge gaps were evident for less obvious or chronic signs, with low body temperature and reduced movement being the least recognized indicators (both 33.6%), followed by yellow discoloration (43.3%) and umbilical redness/pus (41.4%).
A total of 202 mothers (54.3%) had good knowledge. About 62.9% of mothers had previously observed one or more danger signs in their newborns or older children during the neonatal period.
The utilization of maternal healthcare services in the study population presents a mixed picture. While a strong majority (84.9%) chose government hospitals for delivery, and 70.2% met the benchmark of having four or more antenatal care (ANC) visits, there are clear gaps in accessibility and follow-up care. A significant barrier is the long travel time, with 77.4% of individuals requiring more than 30 minutes to reach the nearest facility. Postnatal care (PNC) also shows room for improvement, as the follow-up rate declined to 60.8% for initial visits and 58.1% for at least two visits. Educational efforts appear moderately successful, with 65.9% receiving counselling on neonatal danger signs. Finally, a notable 15.9% of the population reported a history of neonatal death, indicating a high-risk cohort that may require more intensive, targeted interventions.
When danger signs occurred, the majority of individuals sought care within the formal healthcare system, primarily at government hospitals (51.9%) and health centres (27.1%), with a smaller fraction utilizing private clinics (8.1%). However, a concerning minority either used home remedies (4.8%), did nothing (6.5%), or visited traditional healers (1.6%).
Good maternal knowledge regarding these signs was significantly associated with several key factors, all demonstrating a strong statistical relationship (p-values of 0.001 or 0.009/0.029). These factors include higher maternal education, higher family income, the mother's occupation, having four or more antenatal care visits, receiving postnatal care, the husband's involvement, and receiving counselling after delivery. This indicates that socioeconomic status and engagement with the formal healthcare system are crucial determinants of a mother's knowledge level and, consequently, their health-seeking behaviours during critical times.
DISCUSSION:
Most mothers were aged 26-35 years (49.7%). Nearly half had secondary education, while 25.8% had no formal schooling. Similar distributions have been reported in other community-based neonatal health studies(5,7).
This study found that only slightly more than half of the mothers had good knowledge of neonatal danger signs, comparable to findings in Ethiopia and Nigeria (7,10,11).
Recognition was highest for easily noticeable symptoms such as fever and convulsions, consistent with other studies from Ethiopia, Nigeria, and South Asia. However, awareness of hypothermia and reduced activity—often early indicators of severe neonatal illness—was low. WHO and UNICEF report that these missed signs contribute significantly to neonatal mortality (1,3,4).
Maternal education, income, ANC/PNC utilization, and counselling showed significant associations with good knowledge, aligning with global evidence that maternal health service uptake improves awareness and care-seeking behaviours(12,13).
Husband involvement also strongly influenced knowledge, suggesting that family-centered newborn care strategies could be beneficial and improves maternal and newborn outcomes (14).
While most mothers sought healthcare promptly when danger signs appeared, a small proportion still used home remedies or delayed care, underscoring the need for intensified community education, reflecting similar patterns in other studies (8,15).
CONCLUSION:
Maternal knowledge of neonatal danger signs was moderate, with substantial gaps in identifying less obvious but clinically significant signs. Strengthening counselling during ANC and PNC contacts, increasing community awareness, and involving husbands in newborn care could significantly enhance early detection and timely treatment of neonatal illnesses.
KEY MESSAGES-
1. Integrate structured neonatal danger signs counselling into every ANC and PNC visits.
2. Conduct community-level awareness drives focusing on low-recognition signs such as hypothermia and reduced activity.
3. Promote male partner involvement in maternal and newborn health programs.
4. Improve accessibility to healthcare facilities through transport support or community health workers.
REFERENCES:
1. World Health Organization. Managing Newborn Problems: A guide for doctors, nurses and midwives. Geneva: WHO; 2003.
2. World Health Organization. Integrated Management of Childhood Illness (IMCI) Chart Booklet. Geneva: WHO; 2014.
3. UNICEF. The State of the World’s Children 2023: For Every Child, Vaccination. New York: UNICEF; 2023.
4. Lawn JE, Cousens S, Zupan J. 4 million neonatal deaths: When? Where? Why? Lancet. 2005;365(9462):891–900.
5. Central Statistical Agency (Ethiopia) and ICF International. Ethiopia Demographic and Health Survey 2016. Addis Ababa; 2017.
6. Mengistie B, Berhe H, Berhanu D, et al. Awareness and healthcare seeking behavior of neonatal danger signs among mothers in Ethiopia: a multicenter cross-sectional study. BMC Pediatr 2024; 24(1): 278.
7. Mathewos R, Abate L, Berhanu D, et al. Process evaluation of the community-based newborn care program in Geze Gofa district, southern Ethiopia: A case study evaluation. BMC Pregnancy Childbirth 2019; 19(1): 444.
8. Abuidhail J, Al-Maktari S. Mothers’ knowledge of warning signs in newborns and actions taken when danger signs are present. Int J Nurs Pract. 2020;26(3): e12815.
9. Alemu M, Fekadu G, Kedir S. Maternal knowledge of neonatal danger signs and health-seeking practice in Ethiopia: a systematic review. BMC Pediatr. 2021;
10. Ekwochi U,et al. Knowledge of danger signs in newborns and care seeking among mothers in Nigeria. Clin Mother Child Health.2016;13(1):1-8.
11. 11.Nigatu D, Oljira L, Berhane Y. Maternal knowledge of neonatal danger signs in Eastern Ethiopia: A cross-sectional study. Int J Health Sci (Qassim). 2020;14(2):3-12.
12. Tura G, Fantahun M, Worku A. Effect of antenatal care on perinatal outcomes in Ethiopia. PLOS ONE. 2021;16(2): e0246348.
13. Amare ZY, Tesfaw G, Tefera S. Postnatal care service utilization in Ethiopia. Women Birth. 2018;31(4): e223-e229.
14. Sisay W, Tesfaw G, Ferede H. Male involvement in maternal health care and maternal knowledge of neonatal danger signs. Reprod Health. 2021; 18:65.
15. Owais A, et al. Neonatal danger signs recognition and health-seeking behaviour in low-resource settings: A review. BMC Pediatr Health.2023;23:1152.