A rare cause of acute small bowel obstruction: torsion of gangrenous adnexa encircling ileum with ileal perforation – A Case Report.
- Dr. Siddhi Lalwani , Junior Resident 3, Department of General Surgery, MGM Medical College and Hospital, Ch. Sambhajinagar, Maharashtra, India.
- Dr. Harsh Verma , Third Year Resident, Department of General Surgery, MGM Medical College and Hospital, Ch. Sambhajinagar, Maharashtra, India.
- Dr. Pratik Sinha , Third Year Resident, Department of General Surgery, MGM Medical College and Hospital, Ch. Sambhajinagar, Maharashtra, India.
Article Information:
Abstract:
Background: Acute small bowel obstruction (SBO) is a common surgical emergency, most frequently caused by adhesions, hernias, or malignancy. Gynecological causes are rare. We report an unusual case of a 41-year-old female presenting with features of intestinal obstruction, found intraoperatively to have torsion of a gangrenous right ovary and fallopian tube encircling the ileum, leading to obstruction and ileal perforation. The patient underwent emergency exploratory laparotomy with resection of gangrenous adnexa and primary repair of ileal perforation. This case highlights a rare etiology of small bowel obstruction and emphasizes the importance of early surgical intervention.
Keywords:
Article :
INTRODUCTION:
Acute small bowel obstruction is a frequently encountered surgical emergency. Common etiologies include postoperative adhesions, hernias, strictures, and neoplasms. Rarely, gynecological pathologies such as ovarian torsion may contribute to bowel obstruction.
Adnexal torsion typically presents with lower abdominal pain but rarely leads to mechanical bowel obstruction. Even rarer is the encirclement of bowel loops by torsed adnexa leading to ischemia and perforation. We present such a rare and surgically significant case.
CASE PRESENTATION:
A 41-year-old female presented with acute onset diffuse abdominal pain for one day, associated with three episodes of bilious vomiting and one episode of loose stools. There was no history of fever, urinary complaints, or trauma.
She had no known comorbidities. Patient had undergone total hysterectomy 4 years prior on examination, the patient was conscious and hemodynamically stable. Examination revealed a soft, non-distended abdomen with diffuse tenderness.
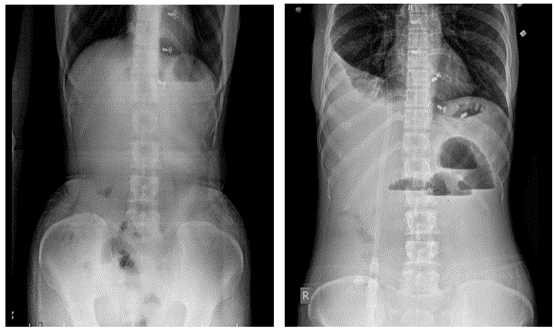
Fig 1. Abdomen erect Xray -Day 1 of admission.; Fig 2. Day 3 of admission
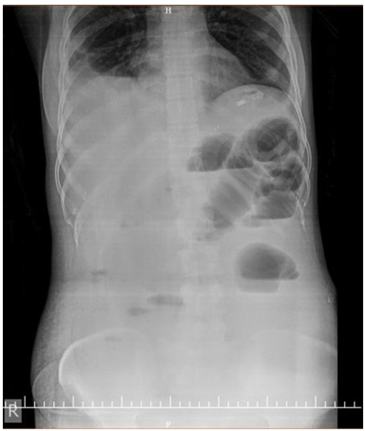
Fig 2. Day 5 post-admission- prior to surgery
USG Abdomen and pelvis reported enterocolitis. X- ray abdomen had no significant findings to confirm obstruction on day of admission.
Patient developed abdominal distension and constipation 1 day post admission
CECT Abdomen + Pelvis done, was suggestive of dilated distal ileal loops of maximum diameter 3.2 cm with transition zone located at the level of terminal ileal loops just proximal to IC junction with mild ascites. Conservative management was given initially.
Ryles tube inserted to relieve abdominal distension.
Patient had relief of symptoms and was started on oral sips. After 1 st day of trial of oral sips, patient developed abdominal distension, tenderness and obstipation. Plan of emergency exploratory laparotomy was decided on 5th day of hospitalisation.
Intra-operatively, torsional right ovary with fallopian tube was found to be gangrenous with multiple turns around the terminal ileum with dilated bowel loops proximally, thus confirming mechanical obstruction of the small bowel. After detorsion of the right ovary, bowel was examined for any signs of ischaemia/ strangulation / perforation. At approximately, 15 cm proximal to Ileo-ceacal junction, two perforations of size approximately 1 x 1 cm were noted over the inflamed ileum on the anti- mesenteric border with slough present over it. However, rest of the bowel appeared healthy. Around 2.5 litres of reactionary peritoneal fluid was drained and sent for culture and sensitivity. Modified graham’s patch repair was done for the perforation. Gangrenous right ovary and fallopian tube were excised and sent for histopathological examination. Thorough peritoneal lavage was done.
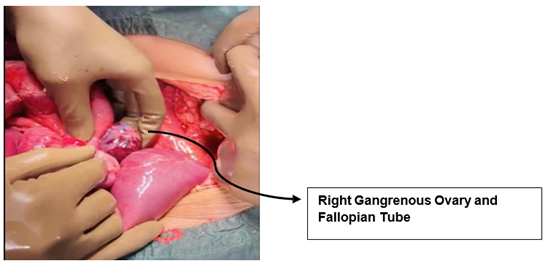
Fig 4. Right Gangrenous Ovary and Fallopian Tube
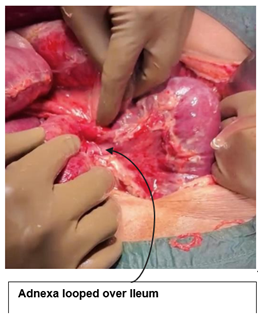
Fig 5. Adnexa looped over Ileum
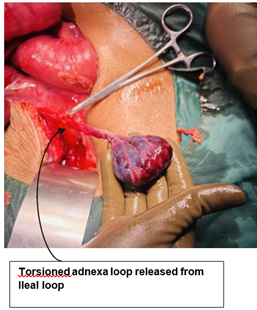
Fig 6. Torsioned adnexa loop released from Ileal loop
Outcomes
The patient was shifted to ICU postoperatively. Hemostasis was secured, and specimens were sent for histopathological examination. The immediate postoperative period was stable.
DISCUSSION:
Small bowel obstruction due to adnexal torsion is extremely rare. Most reported cases involve adhesions or external compression, whereas mechanical obstruction caused by torsed adnexa encircling bowel loops is exceptional.
Radiological imaging may suggest obstruction but often fails to identify such rare causes preoperatively, making diagnostic laparotomy both confirmatory and therapeutic. Early surgical intervention is critical to prevent complications such as perforation, peritonitis, and sepsis.
CONCLUSION:
This case highlights a rare but significant cause of small bowel obstruction. Surgeons should consider gynecological causes in female patients, especially with prior pelvic surgery. Prompt surgical exploration remains the cornerstone of management in complicated SBO.
REFERENCES:
1. Minhem M, Mohsen Y, Saade C, Hallal A. Intestinal obstruction caused by strangulating adnexa: a rare complication of ovarian sparing hysterectomy. BMJ Case Rep. 2018 Feb 14;2018: bcr2017223123. doi: 10.1136/bcr-2017-223123. PMID: 29444792; PMCID: PMC5847950.
2. Murugesan, R. K. S., Ross, K., & Prabakar, J. (2020). A case of ovarian cyst torsion causing intestinal obstruction. International Surgery Journal, 7(12), 4228–4230. https://doi.org/10.18203/2349-2902.isj20205389
3. Schick MA, Kashyap S, Collier SA, et al. Small Bowel Obstruction. [Updated 2025 Jan 19]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2026 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK44807
4. Schick MA, Kashyap S, Collier SA, et al. Small Bowel Obstruction. [Updated 2025 Jan 19]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2026 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK448079/
5. Lazaridis A, Maclaran K, Behar N, Narayanan P. A rare case of small bowel obstruction secondary to ovarian torsion in an IVF pregnancy. BMJ Case Rep. 2013 Feb 15;2013: bcr2013008551. doi: 10.1136/bcr-2013-008551. PMID: 23417952; PMCID: PMC3603835.