Comparative Assessment of Quality of Life in Women with Stress Urinary Incontinence and Urge Urinary Incontinence.
- Dr. Nandani Jha , Senior Resident, Department of Obstetrics and Gynaecology, Shree Narayan medical institute and Hospital, Saharsa, Bihar, India.
Article Information:
Abstract:
Background: Urinary incontinence adversely affects women’s physical, psychological and social well-being. Stress urinary incontinence and urge urinary incontinence have different symptom patterns and may consequently produce different effects on quality of life. Direct comparison of these clinical subtypes may help identify women requiring more intensive and individualised management. Aim: To compare quality of life among women diagnosed with stress urinary incontinence and urge urinary incontinence. Materials and Methods: A hospital-based comparative cross-sectional study was conducted at Department of Obstetrics and Gynaecology, Shree Narayan Medical Institute and Hospital, Saharsa, from April 2025 to September 2025 among 200 women, comprising 100 women with stress urinary incontinence and 100 with urge urinary incontinence. Sociodemographic, obstetric and clinical information was collected using a predesigned questionnaire. Symptom severity was assessed using the International Consultation on Incontinence Questionnaire–Urinary Incontinence Short Form, while condition-specific quality of life was assessed using the King’s Health Questionnaire. Quantitative variables were compared using the independent-samples t-test, while categorical variables were analysed using the chi-square test. Multiple linear regression analysis was performed to identify independent predictors of impaired quality of life. A p value below 0.05 was considered statistically significant. Results: Women with urge urinary incontinence were significantly older than those with stress urinary incontinence (51.8±9.3 versus 49.2±8.7 years; p=0.043) and had a longer duration of symptoms (4.4±2.7 versus 3.6±2.4 years; p=0.028). Nocturia (73.0% versus 31.0%), regular pad use (77.0% versus 48.0%) and the mean ICIQ-UI SF score (14.6±3.4 versus 12.8±3.1) were significantly higher in the urge incontinence group (all p<0.001). The overall King’s Health Questionnaire score was significantly higher among women with urge urinary incontinence (64.9±14.7) than among women with stress urinary incontinence (49.8±15.2), with a mean difference of 15.10 points (95% CI 10.93–19.27; p<0.001). The greatest difference was observed in the sleep and energy domain. Urge urinary incontinence (B=8.42, p<0.001), longer symptom duration (B=0.91, p=0.004), daily leakage (B=5.73, p=0.002), nocturia (B=6.86, p<0.001), regular pad use (B=4.37, p=0.013) and a higher ICIQ-UI SF score (B=1.84, p<0.001) were independent predictors of poorer quality of life. Conclusion: Urge urinary incontinence was associated with significantly greater quality-of-life impairment than stress urinary incontinence, particularly in relation to sleep, emotional health and social functioning. Symptom severity, nocturia, daily leakage, pad dependence and longer symptom duration were important predictors of poorer quality of life. Incorporating validated quality-of-life assessment into routine evaluation may facilitate patient-centred and subtype-specific management.
Keywords:
Article :
INTRODUCTION:
Urinary incontinence is defined as the complaint of involuntary leakage of urine and represents an important health problem among women worldwide. It is associated with embarrassment, social isolation, disturbed sleep, reduced physical activity, impaired sexual relationships, psychological distress and considerable financial burden. Despite these consequences, many affected women do not seek medical advice because of stigma, embarrassment or the belief that urinary leakage is an inevitable consequence of childbirth or ageing.[1,2] Stress urinary incontinence is characterised by involuntary leakage of urine during physical exertion or activities that increase intra-abdominal pressure, such as coughing, sneezing, laughing, exercising or lifting heavy objects. It commonly results from weakness of the pelvic-floor musculature and inadequate urethral support and is associated with pregnancy, vaginal delivery, obesity, menopause and previous pelvic surgery.[1,3] In contrast, urge urinary incontinence is defined as involuntary urinary leakage associated with urgency and is generally accompanied by increased urinary frequency and nocturia. It is considered part of the overactive bladder symptom complex and may result from involuntary detrusor contractions or altered bladder sensory mechanisms.[3,4] Although both conditions involve urinary leakage, their effects on daily life may differ considerably. Women with stress urinary incontinence may restrict exercise, occupational activities, lifting, travel and social participation because of fear of leakage during physical activity. Women with urge urinary incontinence may experience sudden unpredictable leakage, difficulty reaching the toilet, nocturnal disturbances and a persistent need to identify toilet facilities. Consequently, urge urinary incontinence may produce greater disruption of sleep, emotional well-being and social functioning, whereas stress urinary incontinence may have a greater effect on physical activity and role limitations.[2,4] Assessment based only on the frequency or volume of urinary leakage may underestimate its overall effect on women’s lives. Patient-reported quality-of-life instruments provide a broader evaluation of physical, psychological, occupational, social and interpersonal consequences. Validated instruments such as the International Consultation on Incontinence Questionnaire–Urinary Incontinence Short Form and King’s Health Questionnaire allow standardised assessment of symptom severity and condition-specific quality of life.[3,5] Direct comparison of quality of life between women with stress and urge urinary incontinence can identify the domains that are most severely affected in each group and assist clinicians in providing individualised counselling, prioritising treatment and evaluating patient-centred outcomes. Therefore, the present study was undertaken to compare quality of life and its different domains among women with stress urinary incontinence and urge urinary incontinence.
AIM
To compare quality of life among women diagnosed with stress urinary incontinence and urge urinary incontinence.
OBJECTIVES
1. To assess and compare the overall and domain-specific quality-of-life scores of women with stress urinary incontinence and urge urinary incontinence.
2. To determine the clinical and sociodemographic factors associated with impaired quality of life in women with urinary incontinence.
MATERIALS AND METHODS:
Source of Data
The study participants were recruited from women attending the outpatient departments of Obstetrics and Gynaecology and Urology at a tertiary-care teaching hospital. Women presenting with involuntary urinary leakage and clinically diagnosed with either stress urinary incontinence or urge urinary incontinence constituted the source population. Information was obtained through clinical interviews, physical examination, relevant investigations, bladder diaries and validated questionnaires.
Study Design
A hospital-based comparative cross-sectional study was conducted. Eligible participants were divided into two groups:
· Group A: 100 women with stress urinary incontinence.
· Group B: 100 women with urge urinary incontinence.
The quality-of-life scores and associated clinical characteristics were compared between the two groups.
Study Location
The study was conducted at Department of Obstetrics and Gynaecology, Shree Narayan Medical Institute and Hospital, Saharsa, from April 2025 to September 2025.
Study Duration
The study was conducted over 06 months, from April 2025 to September 2025, including participant recruitment, data collection, data analysis and report preparation.
Sample Size
The total sample size was 200 women, with 100 participants in each study group. The sample size was estimated for the comparison of two independent group means by using the following formula:
Where:
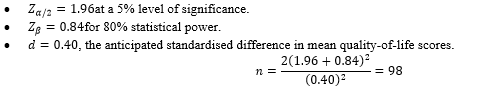
The calculated sample size was approximately 98 participants per group. It was rounded to 100 participants in each group, giving a final sample size of 200.
Sampling Technique
Eligible women were enrolled by consecutive sampling until 100 participants had been included in each group.
Inclusion Criteria
Women were included when they:
1. Were aged 18 years or older.
2. Had symptoms of urinary incontinence for at least three months.
3. Were clinically diagnosed with either stress urinary incontinence or urge urinary incontinence.
4. Were able to understand and answer the study questionnaires.
5. Provided written informed consent to participate.
Stress urinary incontinence was diagnosed when urinary leakage occurred during coughing, sneezing, laughing, physical exertion or other activities that increased intra-abdominal pressure. Urge urinary incontinence was diagnosed when urinary leakage was associated with a sudden compelling desire to void that was difficult to defer.
Exclusion Criteria
Women were excluded when they had:
1. Mixed urinary incontinence without a clearly predominant symptom.
2. Active urinary tract infection.
3. Pregnancy or a history of delivery within the preceding six months.
4. Pelvic organ prolapse beyond the hymen or advanced prolapse requiring surgical treatment.
5. Vesicovaginal fistula, ureterovaginal fistula or continuous urinary leakage.
6. Known neurological disorders affecting bladder function, such as spinal cord injury, multiple sclerosis, stroke or Parkinson’s disease.
7. Urinary tract malignancy, bladder calculus or significant urinary obstruction.
8. Previous surgery for urinary incontinence.
9. Severe cognitive impairment or psychiatric illness interfering with questionnaire completion.
10. Incomplete clinical information or questionnaire responses.
Data Collection
Data were collected using a predesigned, pretested case-record form. Sociodemographic information included age, residence, educational status, occupation, socioeconomic status and marital status. Clinical and obstetric information included body mass index, menopausal status, parity, mode of previous deliveries, duration of urinary symptoms, frequency of urinary leakage, nocturia, urgency, pad use, associated medical illnesses, previous pelvic surgery and current medication use.
Each participant completed a three-day bladder diary documenting fluid intake, voiding frequency, urgency episodes, incontinence episodes, nocturia and pad use. The International Consultation on Incontinence Questionnaire–Urinary Incontinence Short Form was used to evaluate the frequency, severity and overall impact of urinary leakage. The King’s Health Questionnaire was administered to assess condition-specific quality of life.
Procedure and Methodology
Ethical approval was obtained from the Institutional Ethics Committee before initiation of the study. Women presenting with urinary leakage were screened according to the predefined eligibility criteria. The nature and purpose of the study were explained, and written informed consent was obtained.
A detailed history was recorded, followed by general, abdominal, neurological and pelvic examinations. Height and weight were measured, and body mass index was calculated in kg/m². Pelvic examination was performed to identify pelvic organ prolapse, vaginal atrophy, pelvic masses and other abnormalities.
Participants with suspected stress urinary incontinence underwent a cough stress test with a comfortably full bladder. The test was considered positive when urine leakage was observed simultaneously with coughing. Women reporting urgency-associated leakage, usually accompanied by frequency and nocturia, were classified as having urge urinary incontinence after excluding urinary infection and other relevant conditions. Urodynamic testing was reserved for women with an uncertain diagnosis, voiding difficulty, previous pelvic surgery or discordance between symptoms and clinical findings.
Urine routine microscopy and, when indicated, urine culture were performed to exclude urinary tract infection. Ultrasonography of the urinary tract with post-void residual urine measurement was performed when clinically required. Women were assigned to either the stress urinary incontinence group or the urge urinary incontinence group based on standardised symptom assessment and clinical evaluation.
The validated local-language or interviewer-administered versions of the questionnaires were used when required. The investigator administered the questionnaires in privacy to reduce embarrassment and information bias. The same method of questionnaire administration was followed in both groups.
The King’s Health Questionnaire assessed general health perception, impact of incontinence, role limitations, physical limitations, social limitations, personal relationships, emotions, sleep/energy and severity measures. Domain scores were transformed to a scale ranging from 0 to 100. A higher score indicated greater impairment and poorer quality of life.
Sample Processing
No blood or tissue specimens were collected because the study primarily involved clinical assessment and questionnaire-based quality-of-life evaluation. A freshly collected midstream urine specimen was examined only when required to exclude urinary tract infection. Urine samples were collected in sterile containers, labelled with coded participant numbers and transported promptly to the laboratory. Routine microscopy was performed, and urine culture with antimicrobial-susceptibility testing was conducted when infection was suspected. Women with confirmed urinary tract infection were treated and were not included in the final comparison until the infection had resolved.
Outcome Measures
The primary outcome measure was the difference in the overall and domain-specific King’s Health Questionnaire scores between the two groups.
Secondary outcome measures included:
· ICIQ-UI Short Form score.
· Frequency of urinary leakage.
· Number of urgency and incontinence episodes.
· Nocturia and pad use.
· Factors independently associated with poor quality of life.
Statistical Methods
Data were entered into Microsoft Excel and analysed using IBM SPSS Statistics. Quantitative variables were summarised as mean and standard deviation when normally distributed and as median and interquartile range when distributions were skewed. Categorical variables were presented as frequencies and percentages.
Normality was assessed using the Shapiro–Wilk test and graphical methods. The independent-samples Student’s t-test was used to compare normally distributed quality-of-life scores between the two groups. The Mann–Whitney U test was applied to non-normally distributed variables. Categorical variables were compared using the chi-square test or Fisher’s exact test, as appropriate.
Mean differences were reported with 95% confidence intervals. Pearson’s or Spearman’s correlation coefficient was used to assess relationships between symptom severity, duration of incontinence and quality-of-life scores. Multiple linear regression analysis was performed to identify independent predictors of poorer quality of life after adjusting for age, body mass index, parity, menopausal status, duration of symptoms, comorbidities and type of urinary incontinence. A two-sided p value of less than 0.05 was considered statistically significant.
Ethical Considerations
Participant confidentiality was maintained by using coded identification numbers. Participation was voluntary, and participants could withdraw at any time without affecting their medical care. No invasive investigation was performed solely for research purposes. Women requiring treatment were counselled and managed according to institutional protocols.
RESULTS:
Table 1: Comparison of sociodemographic and clinical characteristics of women with stress and urge urinary incontinence (N=200)
|
Characteristic |
Stress urinary incontinence (n=100) |
Urge urinary incontinence (n=100) |
Difference (95% CI) |
Test statistic |
p value |
|
Age, years, mean (SD) |
49.2 (8.7) |
51.8 (9.3) |
-2.60 (-5.11 to -0.09) |
t=-2.04 |
0.043 |
|
BMI, kg/m², mean (SD) |
27.1 (3.6) |
27.8 (3.9) |
-0.70 (-1.75 to 0.35) |
t=-1.32 |
0.189 |
|
Parity, mean (SD) |
2.7 (1.3) |
2.9 (1.4) |
-0.20 (-0.58 to 0.18) |
t=-1.05 |
0.296 |
|
Duration of symptoms, years, mean (SD) |
3.6 (2.4) |
4.4 (2.7) |
-0.80 (-1.51 to -0.09) |
t=-2.21 |
0.028 |
|
Rural residence, n (%) |
43 (43.0) |
49 (49.0) |
-6.0% (-19.8 to 7.8) |
χ²=0.72 |
0.395 |
|
Education up to secondary level, n (%) |
37 (37.0) |
44 (44.0) |
-7.0% (-20.6 to 6.6) |
χ²=1.02 |
0.313 |
|
Postmenopausal, n (%) |
46 (46.0) |
58 (58.0) |
-12.0% (-25.7 to 1.7) |
χ²=2.88 |
0.089 |
|
Obesity, n (%) |
29 (29.0) |
36 (36.0) |
-7.0% (-19.9 to 5.9) |
χ²=1.12 |
0.291 |
|
Diabetes mellitus, n (%) |
18 (18.0) |
23 (23.0) |
-5.0% (-16.2 to 6.2) |
χ²=0.77 |
0.381 |
|
Previous vaginal delivery, n (%) |
72 (72.0) |
68 (68.0) |
4.0% (-8.7 to 16.7) |
χ²=0.38 |
0.537 |
|
Nocturia, n (%) |
31 (31.0) |
73 (73.0) |
-42.0% (-54.6 to -29.4) |
χ²=35.34 |
<0.001 |
|
Daily urinary leakage, n (%) |
54 (54.0) |
69 (69.0) |
-15.0% (-28.3 to -1.7) |
χ²=4.75 |
0.029 |
|
Regular pad use, n (%) |
48 (48.0) |
77 (77.0) |
-29.0% (-41.8 to -16.2) |
χ²=17.94 |
<0.001 |
|
ICIQ-UI SF score, mean (SD) |
12.8 (3.1) |
14.6 (3.4) |
-1.80 (-2.71 to -0.89) |
t=-3.91 |
<0.001 |
Among the 200 women, 100 had stress urinary incontinence and 100 had urge urinary incontinence. Women with urge urinary incontinence were significantly older than those with stress urinary incontinence (51.8±9.3 versus 49.2±8.7 years; mean difference -2.60 years, 95% CI -5.11 to -0.09; t=-2.04, p=0.043). The urge incontinence group also had a significantly longer duration of symptoms (4.4±2.7 versus 3.6±2.4 years; mean difference -0.80 years, 95% CI -1.51 to -0.09; t=-2.21, p=0.028). No significant differences were observed between the groups regarding BMI, parity, residence, education, menopausal status, obesity, diabetes mellitus or previous vaginal delivery (p>0.05). Nocturia was substantially more common among women with urge incontinence than among those with stress incontinence (73.0% versus 31.0%; χ²=35.34, p<0.001). Similarly, daily urinary leakage (69.0% versus 54.0%; χ²=4.75, p=0.029) and regular pad use (77.0% versus 48.0%; χ²=17.94, p<0.001) were significantly more frequent in the urge incontinence group. The mean ICIQ-UI SF score was also significantly higher among women with urge incontinence (14.6±3.4 versus 12.8±3.1; mean difference -1.80, 95% CI -2.71 to -0.89; t=-3.91, p<0.001), indicating greater symptom severity.
Table 2: Comparison of overall and domain-specific quality-of-life scores (N=200)
|
King’s Health Questionnaire domain |
Stress urinary incontinence (n=100), mean (SD) |
Urge urinary incontinence (n=100), mean (SD) |
Mean difference (95% CI) |
t value |
p value |
|
General health perception |
48.6 (18.4) |
57.9 (17.8) |
-9.30 (-14.35 to -4.25) |
-3.63 |
<0.001 |
|
Incontinence impact |
61.7 (20.3) |
74.8 (18.9) |
-13.10 (-18.57 to -7.63) |
-4.72 |
<0.001 |
|
Role limitations |
55.4 (21.7) |
69.6 (20.1) |
-14.20 (-20.03 to -8.37) |
-4.80 |
<0.001 |
|
Physical limitations |
59.8 (22.1) |
64.7 (21.4) |
-4.90 (-10.97 to 1.17) |
-1.59 |
0.113 |
|
Social limitations |
42.3 (20.6) |
58.9 (22.0) |
-16.60 (-22.54 to -10.66) |
-5.51 |
<0.001 |
|
Personal relationships |
38.7 (24.2) |
51.8 (25.1) |
-13.10 (-19.98 to -6.22) |
-3.76 |
<0.001 |
|
Emotional problems |
46.9 (21.8) |
66.4 (20.7) |
-19.50 (-25.43 to -13.57) |
-6.49 |
<0.001 |
|
Sleep and energy |
36.8 (20.4) |
68.7 (22.6) |
-31.90 (-37.90 to -25.90) |
-10.48 |
<0.001 |
|
Severity measures |
57.6 (18.9) |
72.3 (17.5) |
-14.70 (-19.78 to -9.62) |
-5.71 |
<0.001 |
|
Overall quality-of-life score |
49.8 (15.2) |
64.9 (14.7) |
-15.10 (-19.27 to -10.93) |
-7.14 |
<0.001 |
Women with urge urinary incontinence had consistently higher King’s Health Questionnaire scores, indicating poorer quality of life, than women with stress urinary incontinence. The overall quality-of-life score was significantly higher in the urge incontinence group (64.9±14.7) than in the stress incontinence group (49.8±15.2), with a mean difference of -15.10 points (95% CI -19.27 to -10.93; t=-7.14, p<0.001). The largest difference was observed in the sleep and energy domain, where the mean scores were 68.7±22.6 and 36.8±20.4, respectively (mean difference -31.90, 95% CI -37.90 to -25.90; t=-10.48, p<0.001). Women with urge incontinence also had significantly greater impairment in general health perception, incontinence impact, role limitations, social limitations, personal relationships, emotional well-being and severity measures (all p<0.001). Emotional problems showed a mean difference of -19.50 points, while social limitations showed a difference of -16.60 points. Although physical-limitation scores were higher in the urge incontinence group (64.7±21.4 versus 59.8±22.1), the difference was not statistically significant (mean difference -4.90, 95% CI -10.97 to 1.17; t=-1.59, p=0.113).
Table 3: Clinical and sociodemographic factors associated with impaired quality of life: multiple linear regression analysis (N=200)
|
Predictor |
Participant value, n (%) or mean (SD) |
Adjusted regression coefficient, B |
95% CI for B |
t value |
p value |
|
Urge urinary incontinence* |
100 (50.0) |
8.42 |
4.71 to 12.13 |
4.48 |
<0.001 |
|
Age, per one-year increase |
50.5 (9.1) |
0.14 |
-0.03 to 0.31 |
1.62 |
0.107 |
|
BMI, per 1 kg/m² increase |
27.5 (3.8) |
0.31 |
-0.08 to 0.70 |
1.57 |
0.118 |
|
Education up to secondary level |
81 (40.5) |
3.16 |
-0.27 to 6.59 |
1.82 |
0.071 |
|
Postmenopausal status |
104 (52.0) |
2.48 |
-1.19 to 6.15 |
1.33 |
0.185 |
|
Symptom duration, per one-year increase |
4.0 (2.6) |
0.91 |
0.29 to 1.53 |
2.90 |
0.004 |
|
Daily urinary leakage |
123 (61.5) |
5.73 |
2.18 to 9.28 |
3.18 |
0.002 |
|
Nocturia |
104 (52.0) |
6.86 |
3.31 to 10.41 |
3.81 |
<0.001 |
|
Regular pad use |
125 (62.5) |
4.37 |
0.92 to 7.82 |
2.50 |
0.013 |
|
ICIQ-UI SF score, per one-point increase |
13.7 (3.4) |
1.84 |
1.32 to 2.36 |
6.98 |
<0.001 |
|
Diabetes mellitus |
41 (20.5) |
2.11 |
-1.93 to 6.15 |
1.03 |
0.305 |
*Reference category: stress urinary incontinence.
Model statistics: ; adjusted ; F=23.69; p<0.001. Variance inflation factors were below 2.5, indicating no important multicollinearity.
Multiple linear regression analysis showed that the overall model was statistically significant (F=23.69, p<0.001) and explained 58% of the variation in the overall King’s Health Questionnaire score (R²=0.58; adjusted R²=0.56). After adjustment for sociodemographic and clinical variables, urge urinary incontinence remained independently associated with poorer quality of life. Women with urge incontinence had an adjusted score 8.42 points higher than women with stress incontinence (95% CI 4.71 to 12.13; t=4.48, p<0.001). Each additional year of symptom duration was associated with a 0.91-point increase in the quality-of-life impairment score (95% CI 0.29 to 1.53; p=0.004). Daily urinary leakage (B=5.73, 95% CI 2.18 to 9.28; p=0.002), nocturia (B=6.86, 95% CI 3.31 to 10.41; p<0.001) and regular pad use (B=4.37, 95% CI 0.92 to 7.82; p=0.013) were also independent predictors of poorer quality of life. Symptom severity had the strongest statistical association: every one-point increase in the ICIQ-UI SF score was associated with a 1.84-point increase in the overall King’s Health Questionnaire score (95% CI 1.32 to 2.36; t=6.98, p<0.001). Age, BMI, lower educational status, postmenopausal status and diabetes mellitus were not independently associated with quality-of-life impairment (p>0.05). Variance inflation factors below 2.5 indicated the absence of important multicollinearity among the predictors.
DISCUSSION:
The present comparative study evaluated the clinical characteristics and quality of life of 200 women with urinary incontinence, comprising equal numbers with stress urinary incontinence (SUI) and urge urinary incontinence (UUI). The findings demonstrated that women with UUI had more severe urinary symptoms and significantly poorer overall and domain-specific quality of life than women with SUI. Urinary incontinence is increasingly recognised as a multidimensional health problem affecting physical functioning, emotional well-being, sleep, interpersonal relationships and social participation. Aoki et al. (2017)[1] and Lukacz et al. (2017)[2] similarly observed that the clinical burden of urinary incontinence extends beyond urinary leakage and that its effect depends on the type, severity and predictability of symptoms.
Sociodemographic and clinical characteristics
Women with UUI were significantly older than women with SUI, with mean ages of 51.8±9.3 and 49.2±8.7 years, respectively (p=0.043). This finding was consistent with Milsom and Gyhagen (2019)[3], who reported that the frequency of urinary urgency and UUI increased with advancing age because of age-related changes in bladder capacity, detrusor activity, neurological control and functional mobility. Mostafaei et al. (2020)[4] also identified increasing age as an important factor associated with female urinary incontinence in developing countries. Batmani et al. (2021)[5], in a meta-analysis involving 518,465 older women, reported an overall urinary incontinence prevalence of 37.1% and demonstrated a significant relationship between increasing age and urinary incontinence.
Women with UUI had a significantly longer mean duration of symptoms than women with SUI (4.4±2.7 versus 3.6±2.4 years, p=0.028). The longer duration may reflect delayed help-seeking due to embarrassment, acceptance of urinary symptoms as a normal part of ageing or inadequate awareness of available treatment. Saboia et al. (2017)[6] observed that many women tolerated urinary symptoms for prolonged periods and modified their daily activities instead of seeking treatment. Hammad (2021)[7] similarly found low help-seeking behaviour among women with urinary incontinence, despite substantial social and personal consequences.
No significant differences were found between the groups regarding BMI, parity, residence, education, menopausal status, obesity, diabetes or previous vaginal delivery. These findings do not indicate that these variables are unimportant risk factors for urinary incontinence; instead, they suggest that their distributions were comparable between the two clinical subtypes in the present sample. Mostafaei et al. (2020)[4] and Batmani et al. (2021)[5] identified obesity, diabetes, parity and vaginal delivery as factors associated with the overall occurrence of urinary incontinence. However, these variables may be less useful in distinguishing UUI from SUI once urinary incontinence has already developed.
Nocturia was markedly more frequent among women with UUI than among those with SUI (73.0% versus 31.0%, p<0.001). This result was clinically expected because urgency, frequency and nocturia commonly coexist as components of the overactive bladder symptom complex. Aoki et al. (2017)[1] described UUI as a condition characterised by urgency-associated leakage, frequently accompanied by urinary frequency and nocturia. The interruption of sleep caused by nocturia may contribute to daytime fatigue, reduced concentration, emotional distress and deterioration of general health.
Daily urinary leakage and regular pad use were also significantly more frequent in the UUI group. Daily leakage was reported by 69.0% of women with UUI compared with 54.0% of women with SUI (p=0.029), while regular pad use was reported by 77.0% and 48.0%, respectively (p<0.001). Minassian et al. (2020)[8] reported that the natural history and severity of urinary incontinence varied according to subtype and that urgency-related symptoms frequently persisted or progressed over time. The unpredictable nature of urge-associated leakage may explain the greater dependence on pads in women with UUI.
The mean ICIQ-UI SF score was significantly higher in the UUI group than in the SUI group (14.6±3.4 versus 12.8±3.1, p<0.001), confirming greater symptom severity. Nyström et al. (2015)[13] demonstrated that ICIQ symptom and quality-of-life instruments were sensitive to clinically meaningful differences in urinary symptoms. The higher ICIQ-UI SF score among women with UUI was therefore consistent with the greater frequency of nocturia, daily leakage and pad use observed in this group.
Overall and domain-specific quality of life
Women with UUI had a significantly higher overall King’s Health Questionnaire score than women with SUI (64.9±14.7 versus 49.8±15.2; mean difference 15.10 points, p<0.001), indicating poorer quality of life. Pizzol et al. (2021)[9], in a systematic review and meta-analysis, concluded with strong certainty that urinary incontinence was associated with impaired quality of life. Saboia et al. (2017)[6] also demonstrated that the type of urinary incontinence influenced the pattern and magnitude of quality-of-life impairment. Urgency-related leakage may be particularly distressing because it is sudden, difficult to predict and often allows insufficient time to reach a toilet.
General health perception, incontinence impact and role-limitation scores were significantly poorer among women with UUI. The higher incontinence-impact score indicated that these women perceived urinary symptoms as having a greater effect on their everyday lives. Lukacz et al. (2017)[2] reported that urinary incontinence could restrict employment, household activities, exercise, travel and social participation. Women with UUI may plan their daily routine around toilet availability and restrict travel or outdoor activities because of fear of an urgency episode.
Social-limitation and personal-relationship scores were also significantly higher in the UUI group. Saboia et al. (2017)[6] observed that urinary incontinence affected social participation and relationships, with more severe effects among women with urgency or mixed symptoms. Stickley et al. (2017)[10] found that urinary incontinence was associated with loneliness and poorer mental health among community-dwelling older adults. Fear of odour, visible leakage and inability to reach a toilet may result in avoidance of social gatherings and reluctance to discuss symptoms with partners or family members.
Emotional problems were significantly greater among women with UUI, with a mean difference of 19.50 points compared with women with SUI (p<0.001). The psychological effect may arise from embarrassment, loss of control, anxiety about leakage and fear of public humiliation. Stickley et al. (2017)[10] reported significant associations of urinary incontinence with psychological distress, poor mental health and loneliness. Suhr and Lahmann (2018)[11] similarly showed that increasing incontinence severity was associated with a progressively greater effect on quality of life.
The largest between-group difference occurred in the sleep and energy domain. Women with UUI recorded a mean score of 68.7±22.6 compared with 36.8±20.4 among women with SUI, representing a difference of 31.90 points (p<0.001). This difference was consistent with the substantially higher prevalence of nocturia in the UUI group. Repeated awakening to void can cause fragmented sleep, daytime somnolence, fatigue and impaired work performance. Consequently, assessment of nocturia and sleep disturbance should form an essential part of the evaluation of women with UUI.
Severity-measure scores were also significantly higher in the UUI group (72.3±17.5 versus 57.6±18.9, p<0.001). This was consistent with the greater pad use and higher ICIQ-UI SF scores in these women. Kaşıkçı et al. (2015)[12] reported that greater severity of urinary leakage was associated with increasing restrictions in activities of daily living. In the present study, physical-limitation scores did not differ significantly between the groups (p=0.113). Both SUI and UUI may therefore impose similar limitations on exercise and physical activities, although UUI produced greater emotional, social and sleep-related impairment.
Factors independently associated with impaired quality of life
The multiple linear regression model explained 58% of the variation in overall King’s Health Questionnaire scores, indicating that the included clinical variables accounted for a substantial proportion of quality-of-life impairment. UUI remained independently associated with an 8.42-point increase in the overall score compared with SUI (p<0.001). This finding confirmed that the type of urinary incontinence influenced quality of life even after controlling for age, BMI, education, menopausal status, duration and comorbidities.
Longer symptom duration was independently associated with poorer quality of life (B=0.91 per year, p=0.004). Persistent symptoms may produce cumulative restrictions in social, occupational and intimate activities. Suhr and Lahmann (2018)[11] found that severity and continuing care needs were associated with greater quality-of-life impairment. Early identification and management may therefore prevent patients from progressively adapting their lives around urinary symptoms.
Daily urinary leakage, nocturia and regular pad use were significant independent predictors of poorer quality of life. These variables represent the frequency, unpredictability and practical burden of urinary incontinence. Pizzol et al. (2021)[9] reported that increasing symptom severity was associated with a larger deterioration in quality of life. Regular pad use may also reflect fear of leakage, financial burden and persistent awareness of the condition rather than merely serving as a protective measure.
The ICIQ-UI SF score showed the strongest statistical association with quality of life. Each one-point increase in the score was associated with a 1.84-point increase in the overall King’s Health Questionnaire score (p<0.001). This finding was consistent with Nyström et al. (2015)[13], who demonstrated that ICIQ instruments captured clinically relevant differences in symptom burden and quality of life. The close relationship between symptom severity and quality-of-life impairment supports the combined use of symptom-specific and quality-of-life instruments during clinical assessment.
Age, BMI, education, menopausal status and diabetes were not independently associated with quality-of-life scores after adjustment. Although these factors have been associated with the development of urinary incontinence in epidemiological research,[4,5] their influence on quality of life may operate indirectly through symptom type, frequency and severity. Thus, the actual burden of leakage, nocturia and pad dependence may be more important determinants of quality of life than demographic characteristics alone.
CONCLUSION:
Women with urge urinary incontinence experienced significantly greater impairment in overall quality of life than women with stress urinary incontinence. Urge urinary incontinence particularly affected sleep and energy, emotional well-being, social activities, personal relationships and role functioning. Women with urge incontinence also had more severe symptoms, including nocturia, daily urinary leakage, regular pad use and higher ICIQ-UI SF scores. Urge urinary incontinence, longer symptom duration, daily leakage, nocturia, pad use and greater symptom severity were independent predictors of poorer quality of life. Therefore, clinical assessment of urinary incontinence should include validated symptom-severity and quality-of-life instruments. Early diagnosis and individually tailored management, particularly for women with urgency and nocturia, may reduce the physical, psychological and social burden of the condition.
LIMITATIONS
This study had several limitations. First, its cross-sectional design identified associations but could not establish temporal or causal relationships between urinary incontinence and impaired quality of life. Second, the study was conducted at a single tertiary-care hospital; therefore, the findings might not be generalisable to women in the community or other healthcare settings. Third, consecutive sampling could have introduced selection bias because women attending a tertiary-care hospital might have had more severe symptoms. Fourth, urinary symptoms, pad use and quality-of-life outcomes were primarily self-reported and were therefore susceptible to recall and reporting bias. Fifth, embarrassment and social stigma might have led some participants to underreport their symptoms. Sixth, urodynamic testing was not performed routinely in all women, which could have resulted in some misclassification of urinary incontinence type. Women with mixed urinary incontinence were excluded, limiting the applicability of the findings to this common subgroup. Finally, psychological disorders, sexual functioning, medication use, treatment history and socioeconomic burden were not assessed comprehensively. Larger multicentre longitudinal studies are recommended to confirm these findings and evaluate changes in quality-of-life following treatment.
REFERENCES:
1. Aoki Y, Brown HW, Brubaker L, Cornu JN, Daly JO, Cartwright R. Urinary incontinence in women. Nat Rev Dis Primers. 2017;3:17042.
2. Lukacz ES, Santiago-Lastra Y, Albo ME, Brubaker L. Urinary incontinence in women: a review. JAMA. 2017;318(16):1592-1604.
3. Milsom I, Gyhagen M. The prevalence of urinary incontinence. Climacteric. 2019;22(3):217-222.
4. Mostafaei H, Sadeghi-Bazargani H, Hajebrahimi S, Salehi-Pourmehr H, Ghojazadeh M, Onur R, et al. Prevalence of female urinary incontinence in the developing world: a systematic review and meta-analysis. Neurourol Urodyn. 2020;39(4):1063-1086.
5. Batmani S, Jalali R, Mohammadi M, Bokaee S. Prevalence and factors related to urinary incontinence in older adult women worldwide: a comprehensive systematic review and meta-analysis of observational studies. BMC Geriatr. 2021;21(1):212.
6. Saboia DM, Firmiano MLV, Bezerra KC, Vasconcelos Neto JA, Oriá MOB, Vasconcelos CTM. Impact of urinary incontinence types on women’s quality of life. Rev Esc Enferm USP. 2017;51:e03266.
7. Hammad FT. Prevalence, social impact and help-seeking behaviour among women with urinary incontinence in the Gulf countries: a systematic review. Eur J Obstet Gynecol Reprod Biol. 2021;266:150-156.
8. Minassian VA, Hagan KA, Erekson E, Austin AM, Carmichael D, Bynum JPW, et al. The natural history of urinary incontinence subtypes in the Nurses’ Health Studies. Am J Obstet Gynecol. 2020;222(2):163.e1-163.e8.
9. Pizzol D, Demurtas J, Celotto S, Maggi S, Smith L, Angiolelli G, et al. Urinary incontinence and quality of life: a systematic review and meta-analysis. Aging Clin Exp Res. 2021;33(1):25-35.
10. Stickley A, Santini ZI, Koyanagi A. Urinary incontinence, mental health and loneliness among community-dwelling older adults in Ireland. BMC Urol. 2017;17(1):29.
11. Suhr R, Lahmann NA. Urinary incontinence in home care: a representative multicenter study on prevalence, severity, impact on quality of life, and risk factors. Aging Clin Exp Res. 2018;30(6):589-594.
12. Kaşıkçı M, Kılıç D, Avşar G, Şirin M. Prevalence of urinary incontinence in older Turkish women, risk factors, and effect on activities of daily living. Arch Gerontol Geriatr. 2015;61(2):217-223.
13. Nyström E, Sjöström M, Stenlund H, Samuelsson E. ICIQ symptom and quality of life instruments measure clinically relevant improvements in women with stress urinary incontinence. Neurourol Urodyn. 2015;34(8):747-751.