A COMPARITIVE STUDY ON FUNCTIONAL OUTCOME OF INTERLOCKING NAILING AND PLATE OSTEOSYNTHESIS FOR DIAPHYSEAL FRACTURES OF HUMERUS
- Kunche Alekhya , Assistant Professor, Department of Orthopaedics, Guntur Medical College, Guntur, Andhra Pradesh, India
- Naga Venkata Jayakrishna B , Assistant Professor, Department of Orthopaedics, Guntur Medical College, Guntur, Andhra Pradesh, India
- Dr Choppara Srikanth , Assistant Professor, Department of Orthopaedics, Guntur Medical College, Guntur, Andhra Pradesh, India.
Article Information:
Abstract:
Aim: To study the functional outcome of Interlocking nailing and plate osteosynthesis for diaphyseal fractures of humerus. Methodology: A clinical, prospective, observational comparative study.Carried out at Department of Orthopaedics, Government General Hospital, Guntur, during the period of 2years (From May 2022 to April 2024). Patients admitted with diaphyseal fractures of the humerus to the Orthopaedic Department, GGH, Guntur, who satisfy the inclusion and exclusion criteria. Results: In the present study, Group A treated with interlocking nailing had a mean age of 35.7 years(±7.3), while Group B treated with open reduction and plating had a mean age of 36.8 years (±6.7). In Group A, 75% were male (15participants) and 25% were female (5participants).In Group B, 65% were male (13 participants) and 35% were female (7 participants). In Group A, 55% had right-sided fractures (11 participants) and 45% had left-sided fractures (9 participants). In Group B, 45% had right-sided fractures (9 participants) and 55% had left-sided fractures (11 participants). No significant difference (p=0.845) was found. Group A had a mean time to surgery of 6.4 days (±1.2), while Group B had a mean of 7.2 days (±1.3). Group A had 35% comminuted fractures (7 participants), 20% segmental fractures (4 participants), 30% oblique fractures (6 participants), and 15% transverse fractures (3 participants). Group B had 30% comminuted fractures (6 participants), 25% segmental fractures (5participants), 30% oblique fractures (6 participants),and 15% transverse fractures (3 participants). No significant difference (p=0.979) was found. Group A had 40% Type A fractures (8 participants), 30% Type B fractures (6 participants), and 30% Type C fractures (6 participants). Group B had 35% Type A fractures (7 participants), 40% Type B fractures (8 participants), and 25% Type C fractures (5 participants). No significant difference (p=0.801) was observed. 85% of Group A achieved union in <16 weeks (17 participants) compared to 95% in Group B (19 participants). Delayed union occurred in 10% of Group A (2 participants) and5% of Group B(1participant).The mean duration for union was 14.05 weeks (±1.63) for Group A and 14.13 weeks (±1.49) for Group B. No significant difference (p=0.843) was observed. Among total study population 12.5%of participants underwent re- operation (5 participants), and 87.5% did not (35 participants). Conclusion: This study found no significant differences between the two groups in terms of fracture type, time to union, complications, or functional outcomes (ASES and DASH scores).Both groups had similar functional outcome in respect to recovery times.
Keywords:
Article :
Introduction:
Diaphyseal, or mid-shaft, fractures of the humerus represent a relatively small fraction of all skeletal fractures, accounting for approximately 1–3% of cases in clinical practice [1][2]. Earlier majority of these fractures can be effectively managed through non- operative means, using a range of immobilization techniques such as coaptation splints, Velpeau slings, hanging arm casts, and functional bracing [3][4][5]. These conservative approaches have been shown to achieve successful fracture healing in over 90% of cases [6][7][8][9].
However, not every fracture of the humeral shaft is amenable to non-operative treatment. Specific clinical circumstances necessitate surgical intervention. Indications for operative management include failure of conservative therapy, open (compound) fractures, segmental fractures, pathological fractures related to underlying disease, bilateral humeral shaft fractures, associated injuries like a floating elbow (simultaneous fracture of the humerus and forearm bones), vascular injury requiring repair, and fractures complicated by progressive neurological deficits [2][3][5].
The conventional operative method for these complex fractures has long been open reduction and internal fixation (ORIF) using a plate, typically a locking compression plate (LCP).
With advancements in orthopedic trauma surgery, intramedullary nailing has emerged as a minimally invasive alternative for humeral shaft fractures. Specifically, antegrade interlocking intramedullary nailing (ILN) has been introduced as a procedure offering several advantages over conventional plating. Compared to plating, ILN is less invasive, requiring smaller incisions and minimal soft tissue disruption. From a biomechanical perspective, the intramedullary nail acts as a load-sharing device, aligning with the natural mechanical axis of the humerus and promoting stable fixation under physiological loading conditions [10].
Moreover, the intramedullary approach preserves critical biological factors involved in fracture healing. An added biological advantage of ILN is the production of reamed bone debris during nail insertion, which acts as an autograft material, further stimulating bone healing at the fracture site [10].
In light of these theoretical and clinical advantages, this study was conducted to investigate and compare the outcomes of open reduction and internal fixation with locking compression plates (LCP) versus closed reduction and internal fixation using antegrade interlocking intramedullary nails (ILN) for the treatment of diaphyseal fractures of the humerus.
AIM: To study the functional outcome of Interlocking nailing and plate osteosynthesis for diaphyseal fractures of humerus.
OBJECTIVES:
1. To compare the functional outcomes of diaphyseal humeral fractures treated with antegrade interlocking intramedullary nailing (ILN) versus open reduction and internal fixation with plating.
2. To evaluate and compare postoperative recovery associated with interlocking nailing and plate osteosynthesis in the management of humeral shaft fractures.
Materials and Methods:
Study Design: A clinical, prospective, observational comparative study.
Study Period: 2years (From May 2022 to April 2024)
Study Setting: Department of Orthopaedics, Government General Hospital, Guntur.
Source of Data: Patients admitted with diaphyseal fractures of the humerus to the Orthopaedic Department, GGH, Guntur, who satisfy the inclusion and exclusion criteria.
Sample Size:
Total of 40 patients
• 20 patients treated with Interlocking Nailing
• 20 patients treated with Plate Osteosynthesis
Inclusion Criteria:
• Patients aged ≥18 years with diaphyseal fractures of the humerus.
• Comminuted fractures.
• Segmental fractures.
• Polytrauma cases.
• Skeletally mature individuals.
Patients willing to provide informed written consent and comply with follow-up requirements.
Exclusion Criteria:
• Skeletally immature patients.
• Open (compound) fractures.
• Pathological fractures.
• Fractures extending in to the proximal or distal joints.
• Patients medically unfit for surgery.
Method of Study:
Patients who fulfilled the inclusion criteria were selected from those admitted to the Department of Orthopaedics at Government General Hospital (GGH), Guntur. Informed written consent was obtained after explaining the purpose, methodology, potential benefits, and possible complications of the study. Preoperative evaluation included a detailed history noting the mechanism of injury, clinical examination to assess general condition and associated injuries, radiological assessment with standard anteroposterior and lateral X-rays of the humerus, routine blood investigations, and anesthesia fitness evaluation.
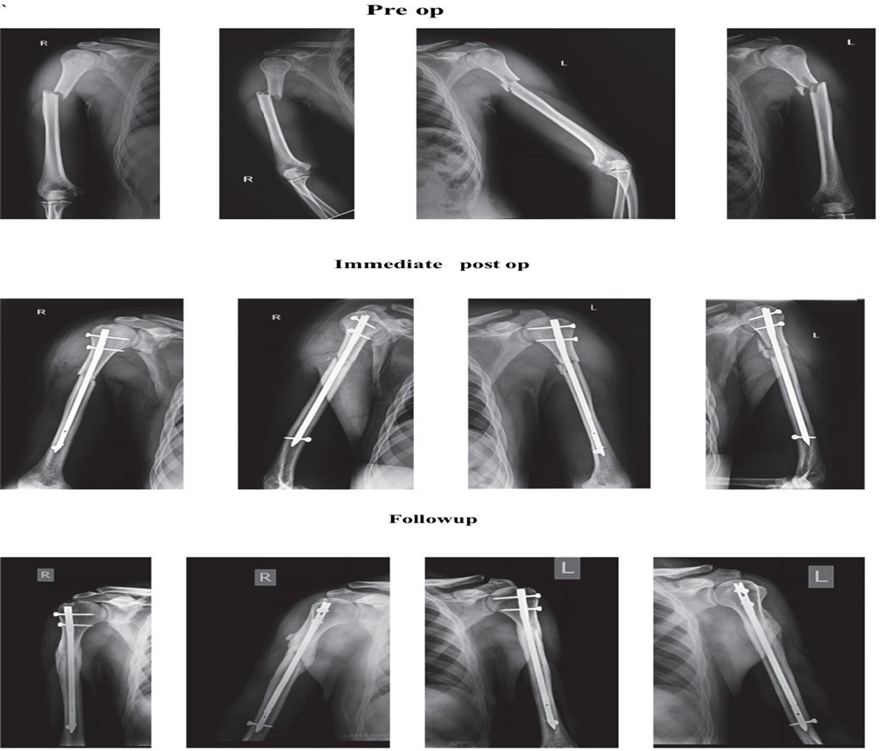
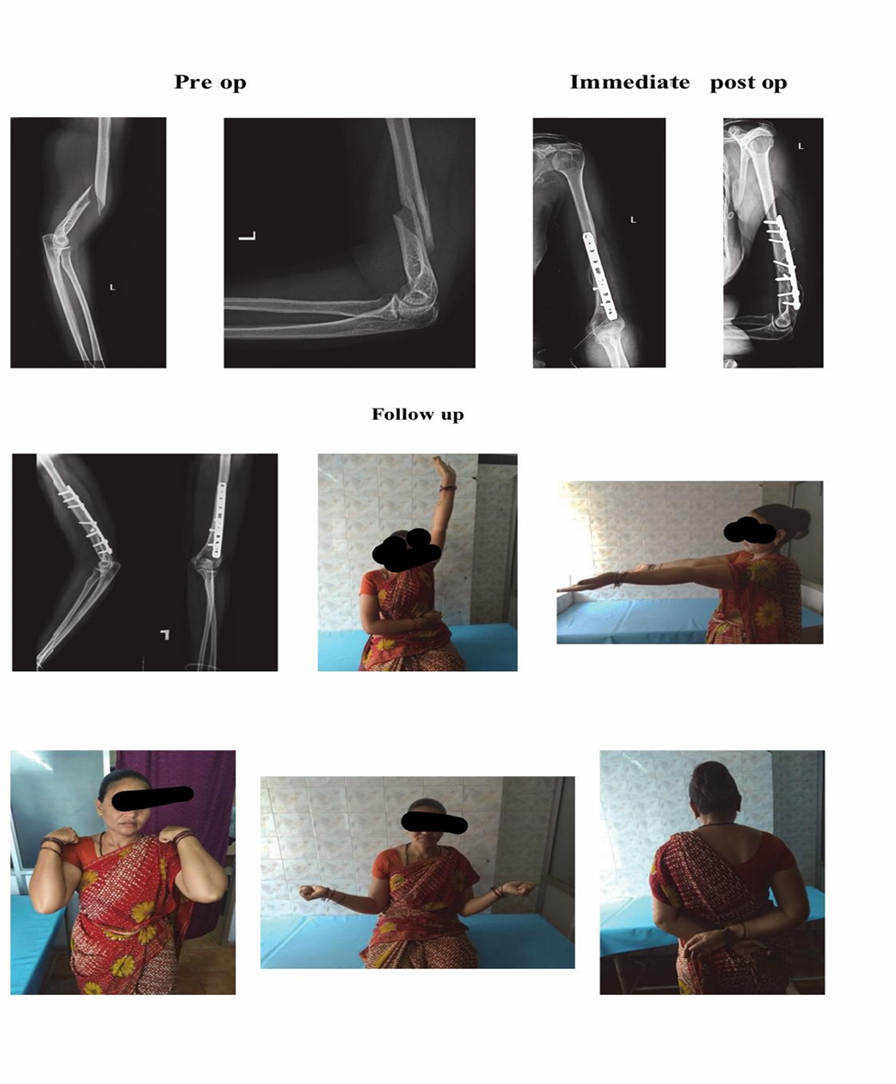
The selected patients were divided into two groups: Group A, treated with Interlocking Nailing, and Group B, treated with Plate Osteosynthesis. The choice of treatment modality was based on the surgeon’s discretion, fracture pattern, and patient preference. Interlocking Nailing was performed under general or regional anesthesia using standard techniques via antegrade approach. Plate Osteosynthesis was carried out under general or regional anesthesia using dynamic or locking compression plates through either an anterolateral or posterior approach.
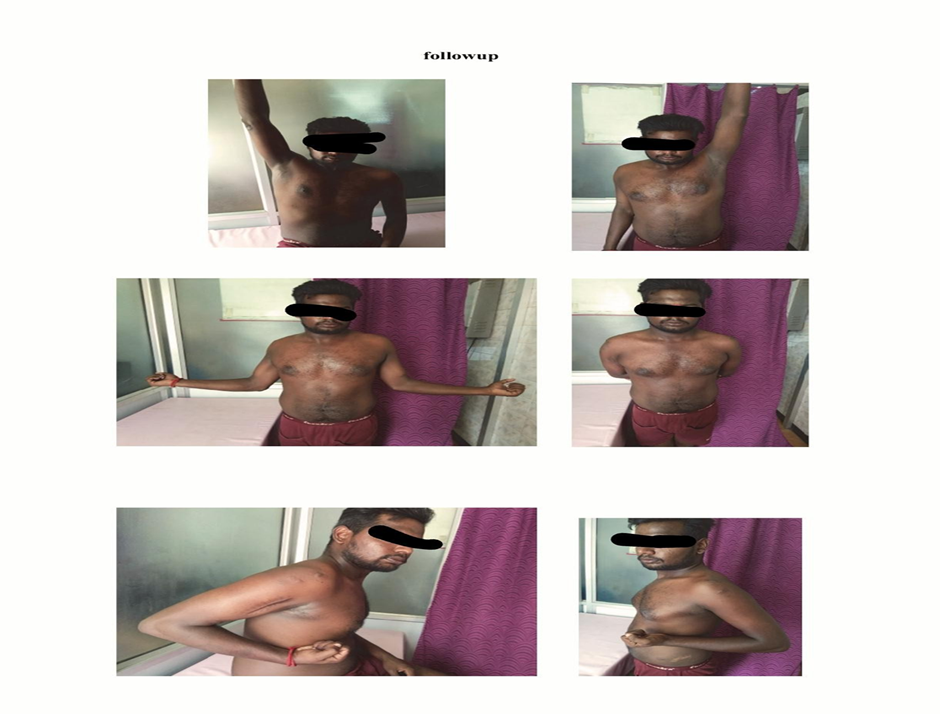
Postoperatively, patients were managed with analgesics and antibiotics as per hospital protocol, and early mobilization was encouraged. Follow-up visits were conducted at 6 weeks, 3 months, 6 months, and 1 year postoperatively. At each visit, clinical evaluation was done to assess pain, range of motion, and functional status, while radiological assessments were performed to evaluate union, alignment, and implant positioning. The primary outcome measured was the functional result, assessed using the American Shoulder and Elbow Surgeons (ASES) score and the Disabilities of the Arm, Shoulder, and Hand (DASH) score. Secondary outcomes included the time taken for radiological union, complication rates such as infection, non-union, and malunion, as well as the time to return to normal daily activities.
Data Analysis:
The collected data will be systematically recorded and entered into a computer database. Descriptive statistics will summarize demographic variables, fracture patterns, and treatment details. Functional outcomes will be assessed using the ASES score and DASH score at follow-up intervals.
Continuous variables like time to union and functional scores will be analyzed using the Independent Samples t-test or Mann-Whitney U test based on data distribution. Categorical variables, such as complication rates, will be compared using the Chi-square test. A p-value of <0.05 will be considered statistically significant. Statistical analysis will be performed using SPSS software and results will be presented with tables and graphs where appropriate.
Results:
Table1: Age Categories Distribution
|
AgeGroup (years) |
GroupA(n=20) |
Group B (n=20) |
Total (n=40) |
|
20–29 |
5 (25%) |
3 (15%) |
8 (20%) |
|
30–39 |
7 (35%) |
9 (45%) |
16(40%) |
|
40–49 |
5 (25%) |
5 (25%) |
10(25%) |
|
50–59 |
3 (15%) |
3 (15%) |
6 (15%) |
|
Total |
20(100%) |
20(100%) |
40(100%) |
|
Mean±SD |
35.7± 7.3 |
36.8± 6.7 |
|
In our study, 40 participants were divided into two groups, A and B, each with 20 individuals. Age distribution showed that Group A had more participants in the 20–29 (25%) and 30–39 (35%) age ranges, while Group B had a higher proportion in the 30– 39 (45%) group. Both groups were equally represented in the 40–49 (25%) and 50–59 (15%) age categories. The mean age for Group A was 35.7 years (±7.3) and for Group B was 36.8 years (±6.7), reflecting similar age distributions across the two groups.
Table3: Side of Fracture Distribution
|
Side of Fracture |
Group A (n=20) |
Group B (n=20) |
Total (n=40) |
|
Right |
11(55%) |
9 (45%) |
20(50%) |
|
Left |
9 (45%) |
11(55%) |
20(50%) |
|
Total |
20(100%) |
20(100%) |
40(100%) |
|
Chi square value=1.25, p value 0.845 |
|||
The table shows the distribution of fracture sides between two treatment groups, A and B, with a total of 40 participants.InGroupA,11participants (55%) had right-sided fractures and 9 participants (45%) had left-sided fractures. In Group B, 9 participants (45%) had right-sided fractures and 11 participants (55%) had left-sided fractures. The Chi-square value is 1.25, with a p-value of 0.845, indicating no significant difference in the side of the fracture between the two groups.
Table 4: Mean Time to Surgery(days)
|
Group |
MeanTime toSurgery (days) ±SD |
|
Group A (Interlocking Nailing) |
6.4±1.2 |
|
Group B(Plate Osteosynthesis) |
7.2±1.3 |
Group A (Interlocking Nailing) had a mean time to surgery of 6.4 days (±1.2),while Group B (Plate Osteosynthesis) had a mean time of 7.2 days (±1.3).
Table5: Mechanism of Injury Distribution
|
Mechanism of Injury |
Group A (n=20) |
Group B (n=20) |
Total (n=40) |
|
Road Traffic Accident |
12(60%) |
10(50%) |
22(55%) |
|
Fall from Height |
4 (20%) |
6 (30%) |
10(25%) |
|
Direct Blow |
3 (15%) |
3 (15%) |
6 (15%) |
|
Other |
1(5%) |
1(5%) |
2(5%) |
|
Total |
20(100%) |
20(100%) |
40(100%) |
|
Chi square value=0.582, pvalue= 0.901 |
|||
The table shows the distribution of injury mechanisms between two groups. Group A had12 (60%)road traffic accidents, 4 (20%) falls from height, 3 (15%) direct blows, and 1 (5%) other. Group B had 10 (50%) road traffic accidents, 6 (30%) falls from height, 3 (15%) direct blows, and 1 (5%) other. The Chi-square value is 0.582 with a p-value of 0.901, indicating no significant difference in the mechanism of injury between the two groups.
Table 6: Type of Fracture Distribution
|
Type of Fracture |
Group A (n=20) |
Group B (n=20) |
Total (n=40) |
|
Comminuted |
7 (35%) |
6 (30%) |
13(32.5%) |
|
Segmental |
4 (20%) |
5 (25%) |
9 (22.5%) |
|
Oblique |
6 (30%) |
6 (30%) |
12(30%) |
|
Transverse |
3 (15%) |
3 (15%) |
6 (15%) |
|
Total |
20(100%) |
20(100%) |
40(100%) |
|
Chi square value=0.188,pvalue= 0.979 |
|||
The table presents the distribution of fracture types between the two groups. In Group A, 7 participants (35%) had comminuted fractures, 4 (20%) had segmental fractures, 6 (30%) had oblique fractures, and 3 (15%) had transverse fractures. In Group B,6 participants (30%) had comminuted fractures, 5 (25%) had segmental fractures, 6 (30%) had oblique fractures, and 3 (15%) had transverse fractures. TheChi-square value is 0.188 with a p-value of 0.979, indicating no significant difference in the type of fracture between the two groups.
Table 7:AO Fracture Classification Distribution
|
AO Type |
Group A (n=20) |
Group B (n=20) |
Total (n=40) |
|
Type A (Stable) |
8 (40%) |
7 (35%) |
15(37.5%) |
|
Type B (Unstable) |
6 (30%) |
8 (40%) |
14(35%) |
|
Type C (Complex) |
6 (30%) |
5 (25%) |
11(27.5%) |
|
Total |
20(100%) |
20(100%) |
40(100%) |
|
Chi square value=0.443,pvalue= 0.801 |
|||
The table 7 shows the distribution of AO fracture types between the two groups. In Group A, 8 participants (40%) had Type A (Stable) fractures, 6 (30%) had Type B (Unstable) fractures, and 6 (30%) had Type C (Complex) fractures. In Group B, 7 participants (35%) had Type A fractures, 8 (40%) had Type B fractures, and 5 (25%)had Type C fractures. The Chi-square value is 0.443 with a p-value of 0.801, indicating no significant difference in the AO fracture type between the two groups.
Table 8: Associated Injury Distribution
|
Associated Injury |
Group A (n=20) |
Group B (n=20) |
Total (n=40) |
|
Head Injury |
4 (20%) |
5 (25%) |
9 (22.5%) |
|
Chest Injury |
3 (15%) |
2 (10%) |
5 (12.5%) |
|
Abdominal Injury |
2 (10%) |
3 (15%) |
5 (12.5%) |
|
Limb Injury |
8 (40%) |
7 (35%) |
15(37.5%) |
|
No Associated njury |
3 (15%) |
3 (15%) |
6 (15%) |
|
Total |
20(100%) |
20(100%) |
40(100%) |
|
Chisquarevalue=0.845,pvalue= 0.871 |
|||
The table shows the distribution of associated injuries between the two groups. InGroup A, 4 participants (20%) had head injuries, 3 (15%) had chest injuries, 2 (10%) had abdominal injuries, 8 (40%) had limb injuries, and 3 (15%) had no associated injuries. In Group B, 5 participants (25%) had head injuries, 2(10%) had chest injuries, 3 (15%) had abdominal injuries,7(35%) had limb injuries, and 3(15%) had no associated injuries. The Chi-square value is0.845 with a p-value of 0.871, indicating no significant difference in the occurrence of associated injuries between the two groups.
Table 9: Union Rateand Time to Union for Group A and Group B
|
Variables |
Group A |
Group B |
P value |
|
Union(<16weeks) |
17(85%) |
19(95%) |
0.873 |
|
Delayed Union(16-32weeks) |
2 (10%) |
1(5%) |
0.532 |
|
Non-union(>32weeks) |
1(5%) |
0(0%) |
0.321 |
|
Number of Patients with Union Achieved |
19(95%) |
19(95%) |
1.000 |
|
Mean Duration for Union (weeks) |
14.05±1.63 |
14.13±1.49 |
0.843 |
|
Mean Duration for Delayed Union (weeks) |
24.86±1.46 |
25.25±1.15 |
0.255 |
The table compares fracture healing outcomes between Groups A and B. In Group A, 85% achieved union in <16 weeks, compared to 95% in Group B (p=0.873). Delayed union occurred in 10% of Group A and 5% of Group B (p=0.532), while 5% of Group A had non-union (p=0.321). Both groups had 95% union achievement (p=1.000). The mean time to union was similar: 14.05 weeks (Group A) vs. 14.13 weeks (Group B) (p=0.843).
Table10: ASES Score Follow-Up Comparison
|
Follow-upInterval |
Group A (Mean ± SD) |
Group B (Mean ± SD) |
P value |
|
6 weeks |
45.3± 8.9 |
43.1± 7.3 |
0.471 |
|
3 months |
65.1± 7.5 |
63.3± 9.1 |
0.572 |
|
6 months |
81.5± 5.1 |
79.3± 7.7 |
0.335 |
|
1year |
91.7± 3.5 |
89.5± 5.3 |
0.212 |
The table compares the follow-up intervals between Groups A and B. At 6 weeks, Group A had a mean score of 45.3 (±8.9), while Group B had 43.1 (±7.3), with no significant difference (p=0.471). At 3 months, Group A had a mean of 65.1 (±7.5) and Group B had 63.3 (±9.1), with no significant difference (p=0.572). At 6 months, Group A had a mean of 81.5 (±5.1) and Group B had 79.3(±7.7) (p=0.335). A t1year, Group A had a mean of 91.7 (±3.5) and Group B had 89.5 (±5.3) (p=0.212), indicating no significant differences across follow-up intervals.
Table 11: DASH Score Follow-Up Comparison
|
Follow-up Interval |
Group A (Mean ± SD) |
Group B (Mean ± SD) |
P value |
|
6 weeks |
65.7±10.9 |
67.1±12.5 |
0.215 |
|
3 months |
45.3± 8.7 |
47.1±10.3 |
0.154 |
|
6 months |
29.1± 5.3 |
31.3± 7.1 |
0.092 |
|
1year |
15.5± 3.5 |
17.3± 5.1 |
0.142 |
The table compares the follow-up intervals between Groups A and B. At 6 weeks, Group A had a mean score of 65.7 (±10.9), and Group B had 67.1 (±12.5), with no significant difference (p=0.215). At 3 months, Group A had a mean of 45.3 (±8.7) and Group B had 47.1 (±10.3) (p=0.154). At 6 months, Group A had a mean of 29.1 (±5.3) and Group B had 31.3 (±7.1) (p=0.092). At 1 year, Group A had a mean of 15.5 (±3.5) and Group B had 17.3 (±5.1) (p=0.142), showing no significant differences across follow-up intervals.
Table 12: Complications Distribution
|
Complication |
GroupA |
Group B |
Total (n=40) |
|
Infection |
2 (10%) |
1(5%) |
3 (7.5%) |
|
Non-union |
1(5%) |
2 (10%) |
3 (7.5%) |
|
Malunion |
1(5%) |
1(5%) |
2(5%) |
|
Implant Failure |
0(0%) |
2 (10%) |
2(5%) |
|
Wound Dehiscence |
0(0%) |
1(5%) |
1 (2.5%) |
|
Deep Vein Thrombosis |
1(5%) |
0(0%) |
1 (2.5%) |
|
No Complications |
15(75%) |
13(65%) |
28(70%) |
|
Total |
20(100%) |
20(100%) |
40(100%) |
The table shows the complications in Groups A and B. In Group A, 2 participants (10%) had infections, 1 (5%) had non-union, 1 (5%) had malunion, 1 (5%) had deep vein thrombosis, and 15 (75%) had no complications. In Group B, 1 participant (5%) had an infection,2(10%)hadnon-union,1(5%) had malunion, 2 (10%) had implant failure, 1(5%) had wound dehiscence,13 (65%) had no complications.Overall,3 participants (7.5%) experienced infection, 3(7.5%) had non-union, and 28 participants (70%) had no complications.
Table13: Re-operation Rates
|
Re-operation Status |
Group A |
Group B |
Total (n=40) |
|
Underwent Re-operation |
2 (10%) |
3 (15%) |
5 (12.5%) |
|
Did Not Undergo Re-operation |
18(90%) |
17(85%) |
35(87.5%) |
|
Total |
20(100%) |
20(100%) |
40(100%) |
The table shows the re-operation status of participants in Groups A and B. In Group A participant (10%underwentre operation, while 18 participants (90%) did not. In GroupB,3 participants(15%) underwent re operation,and 17 participants (85%) did not. Overall, 5 participants (12.5%) underwent re-operation, and 35 participants (87.5%) did not.
Discussion:
AGE CATEGORY:
In our study, we analyzed the age distribution of patients with diaphyseal humeral fractures treated using two different surgical methods: Group A (n=20), treated with Interlocking Nailing (ILN), and Group B (n=20), treated with Plate Osteosynthesis (LCP). The majority of patients in both groups were concentrated in the 30–39 years age group— 35% (7 patients) in Group A and 45% (9 patients) in Group B, accounting for 40% of the total sample (16 out of 40 patients). This finding closely aligns with the results reported byGhosh etal. [11], who observed thatmost humeral fractures occurred in the 21–40 years (55.6%) age group. Similarly, Singisetti K et al. [12] also identified the maximum incidence in the 21–30 and 31–40 years ranges, which mirrors the pattern seen in both our groups.
In the 20–29 years age group, our study had 5 patients (25%) in Group A and 3 patients (15%) in Group B, together accounting for 20% (8 patients) of the total sample. This is comparable to findings by Gandhi et al. [13], who reported 50% of their patients in the 21–30 years group and 65% under 40years, highlighting that young, active adults are typically more prone to diaphyseal humeral fractures. Although our percentages in the 20–29 years group are slightly lower than some studies such as Ghosh et al. [11], the overall distribution confirms that the majority of cases still fall within the younger, more physically active age groups.
When considering the mean age, Group A (ILN) had a mean of 35.7 ±7.3 years, while Group B (LCP) had a slightly higher mean of 36.8 ± 6.7 years, with the combined mean being 36.3 ± 7.0 years. This closely compares with the findings of Gandhi et al. [28], who reported a mean age of 36.42 years in their series. Other studies, such as those by Lapsiwala et al. [14] (mean age 42 years), Parag et al. [15] (mean 42 years), and Verma et al. [16] (mean 38 years), reported slightly older populations, though they still confirm that humeral fractures predominantly occur in the third to fifth decades of life.
GENDER:
In our study, out of a total of 40 patients, there were 28 males (70%) and 12 females (30%), demonstrating a male preponderance. When broken down by treatment groups, Group A (Interlocking Nailing) included 15 males (75%) and 5 females (25%), while Group B (Plate Osteosynthesis) had 13 males (65%) and 7 females (35%). This male predominance is consistent with the majority of published studies on diaphyseal humeral fractures.
For instance, Ghosh et al. [11] reported a similar trend, with 23 males (63.9%) and 13 females (36.1%), aligning closely with our overall distribution. Similarly, Singisetti K et al. [12] observed 77% male patients, a percentage that corresponds well with our 75% in Group A and is slightly higher than our 65% in Group B.
SIDE OF FRACTURE
In our study, the distribution of fractures between the right and left sides was perfectly balanced, with 20 patients (50%) sustaining fractures on the right side and 20 patients (50%) on the left side. In Group A (Interlocking Nailing), 11 patients (55%) had a right-sided fracture, while 9 patients (45%) had a left-sided fracture.
In Group B (Plate Osteosynthesis), 9 patients (45%) had a right-sided fracture, and 11 patients (55%) had a left-sided fracture. This indicates no significant side predilection in our study overall.
Our findings are in agreement with several other studies. Parag et al. [15] similarly reported an equal distribution, with 15 patients (50%) experiencing right limb involvement and 15 patients (50%) with left limb involvement. Additionally, they referenced Singisetti et al. [12], who also observed no obvious side predilection in their series, consistent with our results.
MEAN TIME TO SURGERY
In our study, the mean time to surgery was 6.4 ± 1.2 days in Group A (Interlocking Nailing) and 7.2 ± 1.3 days in Group B (Plate Osteosynthesis). This suggests that patients treated with Interlocking Nailing underwent surgery slightly earlier than those treated with Plate Osteosynthesis, although both procedures were generally performed within a week from admission.
When compared with other studies, our findings show some variation. Ghosh et al. [11] reported a mean interval of 3.13 ± 1.26 days in patients with good or excellent outcomes and 4.5 ±1.73 days in those with moderate or poor outcomes. The difference was not statistically significant (p=0.056), but both averages were shorter than those observed in our study. Similarly, Rathod et al. [17] reported a mean interval of 9 (±3) days in the Locking Compression Plate (LCP) group and 8 (±3) days in the Interlocking Nailing (ILN) group, which is somewhat longer than in our groups, particularly for Plate Osteosynthesis.
MECHANISM OF INJURY
In our study, the most common mechanism of injury was road traffic accidents (RTA), accounting for 22 out of 40 cases (55%). This was followed by falls from heightin 10 cases (25%), direct blows in 6 cases (15%), and other causes in 2 cases (5%).
When compared with other studies, our findings show both similarities and differences. Ghosh et al. [11] reported that direct trauma was the most common cause, responsible for 25 out of 36 cases (69.4%).
However, within their breakdown, road traffic accidents contributed to 21 cases (58.3%), which is very close to our 55%. They also recorded domestic falls in 19.4%, falls from height in 5 cases, and physical assaults in 3 cases — a broader category range than ours.
TYPE OF FRACTURE
(AO FRACTURE CLASSIFICATION)
In our study, based on the AO classification, Type A (Stable) fractures were the most common, observed in 15 out of 40 cases (37.5%), followed closely by Type B (Unstable) fractures in 14 cases (35%), and Type C (Complex) fractures in 11 cases (27.5%). In Group A, Type A fractures constituted 40%, Type B 30%, and Type C 30%. Similarly, in Group B, Type A fractures accounted for 35%, Type B 40%, and Type C 25%.
When compared to published literature, our distribution differs somewhat. Parag et al. [15] classified fractures in their series of 30 patients as predominantly simple shaft fractures (AO12A) in 23 cases (76.7%), including5 spiral (12A1),9 oblique (12A2),and 9 transverse (12A3) fractures. Wedge shaft fractures (AO 12B) accounted for 7 cases (23.3%), while notably, no cases of Type C (multi fragment) fractures were reported. This contrasts with our study, where 27.5% were Type C fractures, indicating a higher proportion of complex fractures.
ASSOCIATED INJURY DISTRIBUTION
In our study, associated injuries were observed in a significant proportion of patients. Limb injuries were the most frequent, seen in 15 out of 40 patients (37.5%), followed by head injuries in 9 patients (22.5%), and chest and abdominal injuries, each in 5 patients (12.5%). Notably, 6 patients (15%) had no associated injuries. The distribution of associated injuries was relatively balanced between the two groups. Group A had a slightly higher frequency of limb injuries (40%) and chest injuries (15%), whereas Group B had a higher proportion of head injuries (25%) and abdominal injuries (15%).
In comparison, many of the studies cited in the literature primarily focused on fracture classifications, such as the AO/OTA system, but did not specifically report the incidence of associated injuries. For instance, studies by Parag et al. [15], Rathod et al. [17], and Lapsiwala et al.[14] predominantly concentrated on the classification and management of diaphyseal fractures, and the details on associated injuries were either not provided or not emphasized.
UNION RATE AND TIME TO UNION
The union rate and time to union for humeral shaft fractures were analyzed for both groups, with no significant difference observed between the two treatment methods. Both groups showed a high union rate of 95%. The mean time for radiological union was 14.05 ± 1.63 weeks for Group A (ILN) and 14.13 ± 1.49 weeks for Group B (DCP), with a p-value of 0.843, indicating no statistically significant difference. The time to union for delayed union cases was also comparable, with Group A having a mean of 24.86 ± 1.46 weeks and Group B at 25.25 ± 1.15 weeks (p = 0.255). A single case of non-union was recorded in Group A, while no non-union was observed in Group B.
ASES SCORE FOLLOW-UP COMPARISON
In our study, we used the ASES (American Shoulder and Elbow Surgeons) score to assess the functional outcomes of humeral shaft fractures over time. The follow-up intervals and corresponding ASES scores for Group A (interlocking nailing) and Group B (dynamic compression plating) were as follows: At 6 weeks, the mean ASES score for Group A was 45.3 ±8.9, and for Group B, it was 43.1 ±7.3.By3 months, Group A showed improvement with a mean ASES score of 65.1 ± 7.5, while Group B had 63.3 ± 9.1. At 6 months, the mean ASES score for Group A was 81.5 ±5.1, and for Group B, it was 79.3 ± 7.7. Finally, at 1 year, Group A reached a mean score of 91.7 ±3.5, while Group B had 89.5 ±5.3.
Comparing these results with studies in the literature, Parag et al. [15] reported a mean ASES score of 90.6, with scores ranging from 44 to 100. They found that 56.7%of patients had ASES scores between 91-100, and 36.7% scored between 81-90. This is quite similar to our findings at the 1-year follow-up, where both Group A and Group B had scores in the 80-90 range, with Group A scoring slightly higher at 91.7.
In Rathod et al. [17]'s study, the ASES score was used to assess functional outcomes, and they reported that 80.76% of patients had scores between 81-100. The mean ASES score for the anterior approach in their plating group was 86.30, while the posterior approach group had a higher score of 90.61. This trend of steadily improving ASES scores over time in our study is similar to Rathod et al. [17]'s findings, where both groups showed positive functional recovery.
In summary, the results of our study show that both treatment groups, Group A (interlocking nailing) and Group B (dynamic compression plating), had favorable functional outcomes, as reflected by the ASES scores. The scores showed gradual improvement over the follow-up period, with Group A reaching a slightly higher score at 1year.These findings are consistent with those from other studies, suggesting that both surgical interventions are effective in achieving functional recovery in humeral shaft fractures.
DASH SCORE FOLLOW-UP COMPARISON
In our study, we assessed functional outcomes using the DASH (Disabilities of the Arm, Shoulder, and Hand) score at multiple follow-up intervals. The findings for Group A (interlocking nailing) and Group B (dynamic compression plating) are as follows: At the 6-week follow-up, Group A had a mean DASH score of 65.7 ± 10.9, while Group B had a mean of 67.1 ± 12.5. At 3 months, the mean DASH score for Group A dropped to 45.3 ± 8.7, and for Group B, it was 47.1 ± 10.3. By 6 months, Group A showed further improvement with a mean score of 29.1±5.3, while Group B had31.3± 7.1. Finally, at the 1-year follow-up, the mean DASH score for Group A was 15.5 ± 3.5, and for Group B, it was 17.3 ± 5.1. These results demonstrate significant improvement in both groups over time.
When comparing these results with those from other studies, Ghosh et al. [11] used the DASH score to evaluate functional outcomes in 36 patients. They reported that 88.8% of their patients had good to excellent results, with 69.4% achieving excellent results and 19.4% achieving good results. The remaining 11.1% had poor to moderate outcomes. While our study doesn't directly report on the proportion of patients achieving good or excellent results, the improvement in DASH scores over the 1-year period in both Group A and Group B aligns with the positive functional outcomes observed by Ghosh et al. [11].
COMPLICATIONS
In this study, complications following surgical management of humeral shaft fractures were observed in 12.5% of the total cases. The most common complications included infection, non-union, malunion, implant failure, wound dehiscence, and deep vein thrombosis. In Group A, which was treated with plate fixation, the complication rate consisted of 10% infection and 5% non-union. Meanwhile, Group B, which underwent intramedullary interlocking nailing, showed a 10% rate of implant failure and a 10% rate of non-union. Overall, 70% of patients experienced no postoperative complications. A higher percentage of complication-free outcomes was recorded in the plate fixation group (75%) as compared to the nailing group (65%).
These findings are consistent with the work of Sharma et al. (2014), whoreported that non-union was not present in their series, although shoulder impingement and radial nerve palsy were noted as occasional complications. Their study reinforces the present study’s finding of a relatively low non-union rate (7.5%), while also highlighting nerve-related complications, which were less emphasized in this analysis. Similarly, Changulani et al. (2007) reported no cases of non-union in their series but documented shoulder impingement and radial nerve palsy, suggesting that while osseous healing is typically reliable, neurological complications remain a concern.Malunion and delayed union have also been identified as notable concerns in several studies. Kesemenli et al. (2003) observed these complications more frequently in patients treated with intramedullary nailing, likely due to the challenges of achieving and maintaining fracture alignment without direct visualization.
RE-OPERATIONRATES
In the present study, the overall re-operation rate was 12.5%, with 5 out of 40 patients requiring a second surgery. Specifically, in Group A (plate fixation), 2 patients (10%) underwent re-operation, while in Group B (intramedullary nailing), 3 patients (15%) required further surgical intervention. This indicates a slightly higher re-operation rate associated with intramedullary nailing compared to plating in this series.
When compared to the findings reported in the literature,there-operation rates in this study are relatively higher. In the study conducted by Ghosh et al. [11], the re- operation rate was limited to just one case in their entire series, demonstrating a much lower incidence. Similarly, Chapman etal. (ascited by Ghosh et al. [11]) reported no re- operations in their patient cohort, suggesting excellent primary outcomes with their chosen fixation method. McCormack et al. [18] (also mentioned by Ghosh et al. [11]) had are-operation rate of one case, while Putti et al. reported more-operations, and Fardeen Sheriff et al. recorded one re-operation in their respective studies. All of these figures indicate lower rates than the 12.5% overall found in the current study.
Conclusion:
This study found no significant differences between the two groups in terms of fracture type, time to union, complications, or functional outcomes (ASES and DASH scores).Both groups had similar functional outcome in respect to recovery times. According to ASES scoring system, p values of 0.471, 0.572, 0.335, 0. 212 were noted at follow-up period - 6 weeks, 3 months, 6 months , 1 year respectively. According to DASH scoring system, p values of 0.215, 0.154, 0.092, 0.142 were noted at follow-up period - 6 weeks , 3 months , 6 months , 1 year respectively. As the p values in both studies are not significant, this study suggest that both treatment approaches are equally effective, although patient-specific factors may influence outcomes. Further research with larger samples and longer follow-up is needed for more comprehensive conclusions.
References:
1. Brinker MR, Connor ODP. The incidence of fractures and dislocations referred for orthopaedic services in a capitated population. J Bone Joint Surg. 2004;86A:290-7.
2. Schemitsch EH, Bhandari M. Fractures of the diaphyseal humerus. In: Browner BD, Jupiter JB, Levine AM, Trafton PG, eds. Skeletal trauma, 3rd ed. Toronto: WB Saunders; 2001: 1481-1511.
3. 3.BohlerL.Conservative treatment of fresh closed fractures of humerus.JTrauma. 1965;5:464-8.
4. Sarmiento A, Zagorski JB, Zych GA, Latta LL, Capps CA. Functional bracing for the treatment of fracturesof the humeral diaphysis. J Bone Joint SurgAm. 2000;82:478- 86.
5. Koch PP, Gross DF, Gerber C. The results of functional (Sarmiento) bracing of humeral shaft fractures. J Shoulder Elbow Surg. 2002;11:143-50.
6. BalfourGW,MooneyV, AshbyME. Diaphyseal fractures of the humerus treated with a ready-made fracture brace. J Bone Joint Surg Am. 1982;64:11-3.
7. Brumback RJ, Bosse MJ, Poka A, Burgess AR. Intramedullary stabilization of humeral shaft fractures in patients with multiple trauma. J Bone Joint Surg. 1986;68: 960-70.
8. Mast JW, Spiegel PG, Harvey JP, Harrison C. Fractures of the humeral shaft. Clin Orthop. 1975;12:254-62.
9. Sarmiento A, Kinman P, Galvin E. Functional bracing of fractures of the shaft of the humerus. J Bone Joint Surg Am. 1977;59:596-601.
10. Wali MG,Baba AN,LatooI A, BhatNA, Baba OK, SharmaS. Internal fixation of shaft humerus fractures by dynamic compression plate or interlocking intramedullary nail: a prospective, randomised study. Strategies Trauma Limb Re-construction. 2014;9(3):133-40.
11. Ghosh S, Nayak B, Bera D, Samanta S. Functional outcome of diaphyseal fractures of humerus in adults treated with closed interlocking nails: A prospective study. Indian J Orthop Surg 2023;9(3):132-146.
12. Singisetti K, Ambedkar M. Nailing versus plating in humerus shaft fractures: A prospective comparative study. International Orthopaedics [Internet]. 2009 Jun 8;34(4):571–6. Available from: https://doi.org/10.1007/s00264-009-0813-2
13. Gandhi TJ, Rajpardhi HA, Patel RN. A comparative study of functional outcome in treatment of diaphyseal humerus fractures with open reduction and internal fixation
14. Lapsiwala, Harsh & Shandilya,Anurodh & Rathore,Bhanu &Shah, Prachi.(2023).A prospective comparative study of functional outcome in patients treated with interlocking nailing and dynamic compression plating for fracture shaft of humerus in adults. Asian Journalof Pharmaceutical and Clinical Research. 140-146.10.22159/ajpcr.2023.v16i5.47182.
15. Parag T, Damor H, Dave D, Patel D, Vadera T. Prospective study of 30 cases of humerus diaphyseal fractures in the adult population. International Journal of Pharmaceutical and Clinical Research. 2023;15(7):41–9.
16. Verma A, Kushwaha SS, Khan YA, Mohammed F, Shekhar S, Goyal A. Clinical outcome of treatment of diaphyseal fractures of humerus treated by titanium elastic nails in adult age group. JOURNAL OF CLINICAL AND DIAGNOSTIC RESEARCH [Internet]. 2017 Jan 1; Available from: https://doi.org/10.7860/jcdr/2017/26449.9812
17. Rathod M, Kanugula SK, Raja P. A prospective comparative study between interlocking nail and locking compression plate for management of diaphyseal fractures of the humerus. Int J Res Orthop2020;6:926-32.
18. Mccormack RG, Brien D, Buckley RE, Mckee MD, Powell J. Fixation of fractures of the shaft of the humerus by dynamic compression plate or intramedullary nail. A prospective, randomised trial. J Bone Joint Surg Br. 2000;82(3):336–9.