Sociodemographic Profile and Risk Factors of Retinopathy of Prematurity at a Tertiary Hospital in Eastern India.
- Sudeshna Roy , Associate Professor, Department of Ophthalmology, Nilratan Sircar Medical College & Hospital, Kolkata, West Bengal, India.
- SK Abid Hasan , Postgraduate Trainee, Department of Ophthalmology, Nilratan Sircar Medical College & Hospital, Kolkata, West Bengal, India.
- Krishna Pada Baidya , Professor, Department of Ophthalmology, Nilratan Sircar Medical College & Hospital, Kolkata, West Bengal, India.
Article Information:
Abstract:
Background: Retinopathy of prematurity is a major preventable cause of childhood blindness among preterm infants. With improving neonatal survival, especially in developing countries, the burden of ROP is increasing. Both neonatal and sociodemographic factors contribute significantly to the development and progression of ROP. This study was conducted to evaluate the sociodemographic profile and associated maternal and neonatal risk factors of ROP (Retinopathy of Prematurity) in a tertiary care hospital in Eastern India. Methods: A hospital-based observational analytical study was conducted among 90 preterm neonates admitted to the neonatal intensive care unit. Infants with birth weight <2000 g and/or gestational age <34 weeks, with or without additional risk factors, were screened for ROP. Data regarding gestational age, birth weight, oxygen therapy, mechanical ventilation, blood transfusion, sepsis, intraventricular haemorrhage, maternal conditions, and sociodemographic variables such as socioeconomic status, maternal education, and residence were collected and analysed statistically to determine their association with ROP. Results: The incidence of ROP was 47.0% among the screened neonates. Significant associations were observed between ROP and gestational age ≤30 weeks (p<0.001), birth weight <1000 g (p<0.001), mechanical ventilation (p=0.012), blood transfusion (p=0.024), and intraventricular haemorrhage (p=0.001). Sociodemographic determinants also showed significant influence, with higher prevalence of ROP among infants from rural areas (86.7%), low socioeconomic status (85.6%), younger maternal age, and mothers with lower educational status. Conclusion: Both clinical and sociodemographic factors play an important role in the development of ROP. Early screening, timely intervention, improved neonatal care, maternal education, and strengthening healthcare facilities in rural and resource-limited areas are essential to reduce the burden of ROP-related blindness. Targeted preventive strategies can significantly improve visual outcomes among preterm infants.
Keywords:
Article :
INTRODUCTION:
Retinopathy of prematurity is a leading cause of preventable bilateral blindness in early infancy and remains a major public health concern worldwide. It is characterized by abnormal retinal vascular development leading to vitreoretinal fibrosis, macular dragging, and retinal detachment with severe visual impairment if left untreated.[1] Several studies have demonstrated that lower gestational age and low birth weight are the most significant risk factors associated with the development of ROP (Retinopathy of Prematurity).[2] In addition, neonatal morbidities such as respiratory distress syndrome, bronchopulmonary dysplasia, sepsis, intraventricular haemorrhage, poor weight gain, and hyperglycaemia further increase the risk of disease progression.[3]
With advances in neonatal intensive care and improved survival of extremely premature infants, the incidence of ROP has also increased globally.[4] In India, the incidence of ROP ranges between 20–30%.[5,6] Although many cases regress spontaneously, a significant proportion may progress to retinal detachment and irreversible blindness if not detected and treated early.[5] Therefore, timely screening, regular follow-up, and prompt intervention are essential for preserving vision in affected infants.
India faces unique challenges in the management of ROP because of the high burden of preterm births and disparities in healthcare access. The disease has a multifactorial etiology influenced by maternal, neonatal, and sociodemographic factors such as socioeconomic status, maternal education, place of residence, and accessibility to specialized neonatal care. Understanding these determinants is crucial for developing effective screening and prevention strategies.
Despite the implementation of screening guidelines by the IAP (Indian Academy of Paediatrics) and IROP (Indian Retinopathy of Prematurity) programs, regional disparities in screening coverage and treatment facilities persist, especially in resource-limited settings. Tertiary care hospitals play a vital role in identifying at-risk neonates and providing timely management.
AIMS AND OBJECTIVES
The study aimed to estimate the proportion of ROP among preterm infants with birth weight <2000 grams and/or gestational age <34 weeks and to evaluate its association with neonatal, maternal, and sociodemographic risk factors. The study also aimed to identify preventable risk factors to support early screening, timely intervention, and improved neonatal care practices.
MATERIALS AND METHODS:
Study Design
This institution-based observational analytical case-control study was conducted in the Retina Clinic, Department of Ophthalmology, and Special Newborn Care Unit (SNCU) of Nil Ratan Sircar Medical College and Hospital, Kolkata. The study was carried out over a period of One and half years after obtaining approval of the synopsis from the West Bengal University of Health Sciences (WBUHS). The study population included preterm infants attending the Retina Clinic and SNCU with a birth weight less than 2000 grams and a gestational age less than 34 weeks who underwent screening for ROP.
Ethical Approval
The study was conducted after institutional ethics committee approval (ECR/609/Instt/WB/2014/RR-20)
Inclusion and Exclusion Criteria
The study included preterm infants with birth weight less than 2000 grams and/or gestational age less than 34 weeks, with or without associated risk factors, as well as follow-up cases of ROP with or without prior treatment. Written informed consent was obtained from parents or guardians before enrollment. Infants with birth weight more than 2000 grams and gestational age greater than 34 weeks were excluded from the study. Babies with congenital systemic anomalies, congenital ocular abnormalities, severe illness, ocular infections, or eyes showing tractional components or retinal detachment were also excluded from the study.
Sample Size Calculation
Sample size was calculated using the formula
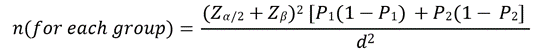
Where 𝑍𝛼/2=1.96 (at 95% confidence interval) is the critical value of the normal distribution at α/2, 𝑍𝛽=0.84 (at 80% power) is the critical value of the normal distribution at β.
P1 = Prevalence of risk factor in control arm.
P2 = Prevalence of risk factor in case arm. d=(P1 −P2)
Using P1=35.3% and P2=64.7% as the proportions of infants developing ROP and NO ROP (Study by Vipin Thakur et al.,[7]). Using this formula minimum sample size in each group was 42, rounded off to 45.Total sample size was 90.
Data Collection Procedure
Data collection was carried out through routine newborn ROP screening at the departmental Retina Clinic and Special Newborn Care Unit (SNCU) in the presence of a pediatrician. Preterm infants with birth weight less than 2000 grams and/or gestational age less than 34 weeks, with or without associated risk factors, as well as follow-up cases of ROP with or without treatment, were included after obtaining informed consent from parents or guardians. The first ophthalmological examination was performed at 3 weeks of postnatal age for both inborn and outborn babies. Pupillary dilatation was achieved using diluted tropicamide 0.5% and phenylephrine 5%, instilled at 10-minute intervals up to three times. Examinations were conducted one hour after feeding to minimize the risk of vomiting and aspiration. Indirect ophthalmoscopy was performed using a binocular indirect ophthalmoscope with the help of an Alfonso eye speculum and paediatric scleral depressor or baby wire vectis, assisted by SNCU nursing staff. Newborns diagnosed with ROP were included in the study, and their neonatal, maternal, and sociodemographic risk factors were recorded. The zone, stage, and extent of ROP, along with the presence or absence of plus or pre-plus disease, were documented. Follow-up schedules were maintained until a definitive outcome was achieved, including spontaneous regression or severe ROP requiring treatment (Type 1 ROP), after which follow-up was terminated.
Statistical Analysis
All collected data were compiled in Microsoft Excel and analysed using SPSS (Statistical Package for Social Sciences) version 24. Continuous variables were expressed as mean ± standard deviation (SD) or median with interquartile range (IQR), while categorical variables were presented as proportions and percentages. Data were displayed using tables and charts. Statistical analysis included Unpaired t-test, Pearson correlation coefficient, and one-way ANOVA for normally distributed continuous variables, while Mann–Whitney U test, Spearman correlation coefficient, and Kruskal–Wallis ANOVA were used for skewed data. Chi-square test or Fisher’s exact test, along with the Odds Ratio (OR) and 95% confidence interval (CI), was applied for categorical variables. Multivariate analysis was performed wherever required. A p-value of less than 0.05 was considered statistically significant.
RESULTS:
Table 1. Distribution of Gestational Age
|
Gestational Age |
Frequency |
Percentage |
|
≤30 weeks |
45 |
50.0% |
|
>30 to ≤34 weeks |
36 |
40.0% |
|
>34 weeks |
9 |
10.0% |
|
Total |
90 |
100% |
Table 1 illustrates the distribution of gestational age among the neonates included in the study. Half of the neonates (50.0%) were born at ≤30 weeks of gestation, while 40.0% were born between >30 and ≤34 weeks. Only 10.0% were born after 34 weeks. This indicates that the majority of neonates were extremely or moderately premature, which is an important risk factor for Retinopathy of Prematurity (ROP).
Table 2. Distribution of Birth Weight
|
Birth Weight |
Frequency |
Percentage |
|
<1000 gm |
26 |
28.9% |
|
1000–1500 gm |
57 |
63.3% |
|
>1500 gm |
7 |
7.8% |
|
Total |
90 |
100% |
Table 2 observes the distribution of birth weight among the study neonates. The majority (63.3%) had a birth weight between 1000 and 1500 gm, while 28.9% had extremely low birth weight (<1000 gm). Only 7.8% weighed more than 1500 gm. These findings suggest that low birth weight was highly prevalent in the study population and may contribute significantly to the development of ROP.
Table 3. Distribution of Gender and Mode of Delivery
|
Variable |
Category |
Frequency |
Percentage |
|
Gender |
Male |
49 |
54.4% |
|
|
Female |
41 |
45.6% |
|
Mode of Delivery |
LUCS |
56 |
62.2% |
|
|
NVD |
34 |
37.8% |
Table 3 illustrates the gender distribution and mode of delivery among neonates. Male neonates constituted 54.4% of the study population, showing a slight male predominance. Regarding delivery mode, 62.2% of neonates were delivered through LUCS (Lower Uterine Caesarean Section), while 37.8% were delivered by NVD (Normal Vaginal Delivery). The higher proportion of LUCS may reflect the increased obstetric complications associated with premature deliveries.
Table 4. Distribution of Maternal Age
|
Maternal Age |
Frequency |
Percentage |
|
<20 years |
38 |
42.2% |
|
20–30 years |
33 |
36.7% |
|
>30 years |
19 |
21.1% |
|
Total |
90 |
100% |
Table 4 demonstrates the maternal age distribution in the study population. Mothers aged below 20 years constituted the highest proportion (42.2%), followed by mothers aged 20–30 years (36.7%). Younger maternal age has been associated with preterm delivery and low birth weight, thereby indirectly increasing the risk of ROP.
Table 5. Association of Sociodemographic Profile with Plus Disease
|
Variable |
Category |
Plus Disease Present (%) |
P value |
|
Gestational Age |
≤30 weeks |
48.9% |
<0.001* |
|
Birth Weight |
<1000 gm |
65.4% |
<0.001* |
|
Maternal Age |
<20 years |
52.6% |
<0.001* |
|
Socioeconomic Status |
Low SES |
28.6% |
0.084 |
|
Place of Residence |
Rural |
29.5% |
0.123 |
Table 5 highlights the association between sociodemographic factors and the presence of plus disease. Significant associations were observed with gestational age ≤30 weeks, birth weight <1000 gm, and maternal age <20 years (p<0.001). These findings indicate that extreme prematurity, very low birth weight, and younger maternal age are important predictors of severe ROP progression.
Table 6. Association of Maternal and Neonatal Risk Factors with Plus Disease
|
Risk Factor |
Plus Disease Present (%) |
P value |
|
PIH |
36.8% |
0.062 |
|
GDM |
23.1% |
0.752 |
|
Oxygen Therapy >7 days |
31.4% |
0.056 |
|
Mechanical Ventilation |
70.0% |
0.001* |
|
Blood Transfusion |
31.9% |
0.024* |
|
Sepsis |
29.3% |
0.201 |
|
Intraventricular Haemorrhage |
66.7% |
0.001* |
Table 6 observes the association between maternal and neonatal risk factors and plus disease. Mechanical ventilation, blood transfusions, and IVH (Intraventricular Haemorrhage) showed statistically significant associations with plus disease. Neonates requiring prolonged respiratory support and transfusions were at significantly greater risk of developing severe forms of ROP.
Table 7. Association of Sociodemographic Profile with Aggressive ROP (AROP)
|
Variable |
Category |
AROP Present (%) |
P value |
|
Gestational Age |
≤30 weeks |
37.8% |
<0.001* |
|
Birth Weight |
<1000 gm |
50.0% |
<0.001* |
|
Maternal Age |
<20 years |
36.8% |
0.002* |
|
Low Socioeconomic Status |
Low SES |
20.8% |
0.080 |
|
Rural Residence |
Rural |
21.8% |
0.278 |
Table 7 illustrates the association between sociodemographic variables and aggressive ROP (AROP). A statistically significant association was found between AROP and gestational age ≤30 weeks, birth weight <1000 gm, and maternal age <20 years. These findings suggest that extreme prematurity and younger maternal age increase the risk of aggressive retinal disease.
Table 8. Association of Neonatal Risk Factors with AROP and Zone of ROP
|
Risk Factor |
AROP Present (%) |
P value |
Zone 1 ROP (%) |
P value |
|
Mechanical Ventilation |
50.0% |
0.012* |
40.0% |
0.737 |
|
Blood Transfusion |
23.6% |
0.087 |
49.1% |
0.568 |
|
Sepsis |
21.3% |
0.480 |
49.2% |
0.485 |
|
Intraventricular Haemorrhage |
58.3% |
<0.001* |
100.0% |
0.014* |
|
GDM |
— |
— |
76.9% |
0.018* |
Table 8 demonstrates the association of important neonatal risk factors with AROP and Zone of ROP. Mechanical ventilation and intraventricular haemorrhage showed significant association with AROP, while GDM and IVH were significantly associated with severe Zone 1 ROP. IVH emerged as one of the strongest predictors of severe retinal involvement.
DISCUSSION:
The present study was conducted to evaluate the sociodemographic profile and various maternal and neonatal risk factors associated with ROP in a tertiary care hospital in Eastern India. The incidence of ROP in the present study was found to be approximately 47.0%, which is comparatively higher than several previously published Indian studies. This high incidence may be attributed to improved survival of extremely premature neonates, increased referral of high-risk babies to tertiary care centres, and the predominance of neonates belonging to low socioeconomic and rural backgrounds in the present study. Similar increasing trends in ROP incidence have been reported in developing countries due to advancements in neonatal care and survival of preterm infants.[8,9]
In the present study, the majority of neonates were born before 34 weeks of gestation, with 50% born at ≤30 weeks. Gestational age showed a strong association with severe ROP manifestations such as plus disease and AROP. These findings are consistent with studies by Gour R et al.,[8] Patel SS et al.,[9] Thakur V et al.,[7] and Caberry W. Yu et al.,[10] who identified lower gestational age as one of the strongest predictors for development and progression of ROP. Prematurity interrupts normal retinal vascularization and exposes the immature retina to fluctuating oxygen levels, leading to abnormal neovascularization.
Birth weight was another important determinant observed in the present study. Most neonates had low birth weight, with 28.9% weighing below 1000 grams. Extremely low birth weight infants showed significantly higher prevalence of severe ROP. Similar observations were reported by Patel SS et al.,[9] Yang CY et al.,[11] and Azami M et al.,[12] where low birth weight was found to be a major independent risk factor for ROP. Lower birth weight reflects retinal immaturity and systemic instability, thereby increasing susceptibility to retinal vascular damage.
The present study demonstrated a slight male predominance among affected neonates, similar to findings reported by Gour R et al.[8] However, gender did not show any statistically significant association with severe ROP, which is comparable with previous studies.[12]
Maternal sociodemographic factors played a significant role in the present study. A large proportion of mothers belonged to rural areas and low socioeconomic status, and most had only primary or secondary education. These findings highlight the impact of social determinants on neonatal outcomes. Similar observations were made by Strawbridge JC et al.,[13] and Karmouta R et al.,[14] who emphasized the importance of socioeconomic conditions, healthcare access, maternal education, and antenatal care in influencing ROP outcomes. Poor socioeconomic conditions may contribute to delayed antenatal care, nutritional deficiencies, poor maternal health awareness, and inadequate neonatal follow-up.
Younger maternal age was also found to be significantly associated with severe ROP manifestations in the present study. Teenage pregnancies are frequently associated with prematurity, low birth weight, and poor antenatal care, thereby indirectly increasing the risk of ROP. Similar associations between maternal factors and ROP have been highlighted in previous literature.[13]
Among maternal risk factors, PIH (Pregnancy-Induced Hypertension) was present in a considerable proportion of mothers in the present study. Although PIH did not show statistically significant association with all severe forms of ROP, it remains an important contributor to prematurity and fetal growth restriction. Yang CY et al.[11] also reported maternal preeclampsia as a significant predictor for threshold ROP. GDM (Gestational Diabetes Mellitus) was less prevalent in the current study but showed an association with severe Zone 1 ROP, suggesting that metabolic instability during pregnancy may contribute to retinal vascular abnormalities.
Prolonged oxygen therapy was highly prevalent among neonates in the present study, with more than three-fourths receiving oxygen therapy for over seven days. Oxygen exposure is a well-established risk factor for ROP due to suppression of normal retinal vascular growth followed by hypoxia-induced neovascularization. Similar findings were reported by Hakeem AA et al.,[15] Chaudhari S et al.[16] and Utomo TM et al.,[17] where oxygen therapy was identified as a major independent predictor of ROP.
Mechanical ventilation showed a statistically significant association with severe ROP and AROP in the present study. Ventilator support often reflects severe respiratory illness and prolonged oxygen exposure, both of which contribute to oxidative stress and retinal vascular injury. Comparable findings were observed in studies by Thakur V et al.[7] and Yang CY et al.[11] where prolonged mechanical ventilation significantly increased the risk of threshold ROP.
Blood transfusion was another important neonatal risk factor identified in this study. Neonates receiving blood transfusions showed a higher prevalence of severe ROP. Similar associations were reported by Patel SS et al.,[9] Hakeem AA et al.,[15] and Chaudhari S et al.[16] Blood transfusions may contribute to oxidative stress and iron overload, leading to abnormal retinal vascular proliferation.
Neonatal sepsis was highly prevalent in the current study population. Although statistical significance was not consistently observed for all severe ROP forms, sepsis remains an important contributor to systemic inflammation and vascular instability. Several previous studies including Utomo TM et al.,[17] Azami M et al.,[12] and Nayyar et al.[18] identified sepsis as a significant risk factor for ROP progression.
Intraventricular haemorrhage emerged as one of the strongest predictors of severe ROP in the present study, showing significant association with Plus Disease, AROP, and severe Zone 1 disease. Similar observations were reported by Azami M et al.[12] and Yang CY et al.[11] IVH reflects systemic vascular instability and extreme prematurity, both of which contribute to retinal vascular dysregulation.
Regarding disease characteristics, Zone 2 ROP was the most common presentation in the present study, followed by Zone 1 involvement. Stage 2 ROP constituted the majority of cases, while Plus Disease and AROP were observed in a smaller but clinically significant proportion of neonates. Similar disease profiles were observed in studies by Terchandani U et al.[19] and Nayyar et al.,[18] where severe posterior disease and AROP were increasingly reported among preterm infants.
The findings of the present study emphasize the importance of early screening, strict oxygen monitoring, infection control, and improved neonatal intensive care practices. Additionally, maternal education, socioeconomic upliftment, and strengthening neonatal healthcare services in rural areas are essential to reduce the burden of ROP-related blindness. Timely diagnosis and intervention can significantly improve visual outcomes and prevent irreversible blindness in preterm infants.
LIMITATIONS
Despite the significant findings of the present study, certain limitations should be considered while interpreting the results. The study included a relatively small sample size of 90 preterm neonates, which may limit the generalizability of the findings to the wider population. Being a single-centre study conducted at a tertiary care hospital, the results may not accurately represent neonatal populations from other healthcare settings, particularly rural and resource-limited areas. In addition, several potential confounding factors such as maternal nutritional status, quality of antenatal care, environmental influences, and genetic predisposition were not extensively analysed and may have influenced the development and severity of ROP. Furthermore, the study lacked long-term follow-up of neonates, preventing assessment of long-term visual outcomes and neurodevelopmental sequelae associated with ROP. Therefore, future multicentric studies with larger sample sizes and prolonged follow-up are recommended to validate the present findings and to improve screening, prevention, and management strategies for ROP.
CONCLUSION:
This study highlights that, in addition to established neonatal risk factors such as prematurity, low birth weight, oxygen exposure, mechanical ventilation, sepsis, blood transfusions, PIH, and GDM, sociodemographic factors also play a significant role in the development of ROP. A higher prevalence of ROP was observed among neonates from rural areas, low socioeconomic backgrounds, and mothers with lower education levels and younger maternal age. These findings emphasize the need for improved maternal education, prevention of teenage pregnancies, strengthening neonatal care services in resource-limited settings, and ensuring timely ROP screening and early intervention. Enhanced collaboration between neonatologists, ophthalmologists, and public health policymakers is essential to reduce the burden of preventable childhood blindness due to ROP.
Conflict of Interest: Nil.
REFERENCES:
1. Hellström A, Smith LE, Dammann O. Retinopathy of prematurity. Lancet 2013;382:1445-57.
2. Liu L, Tian T, Zheng CX, et al. Risk factors and laser therapy for retinopathy of prematurity in neonatal intensive care unit. World J Pediatr 2009;5:304-7.
3. Lee J, Dammann O. Perinatal infection, inflammation, and retinopathy of prematurity. Semin Fetal Neonatal Med 2012;17:26-9.
4. Shah PK, Prabhu V, Karandikar SS, et al. Retinopathy of prematurity: past, present and future. World J Clin Pediatr 2016;5:35-46.
5. Arun S. Guidelines for universal eye screening in newborns including retinopathy of prematurity. 2016.
6. Chaudhari S, Patwardhan V, Vaidya U, et al. Retinopathy of prematurity in a tertiary care center--incidence, risk factors and outcome. Indian Pediatr 2009;46:219-24.
7. Thakur V, Randa R, Sharma S, et al. Clinical profile and risk factors of retinopathy of prematurity (ROP) in central Indian population. European Journal of Molecular & Clinical Medicine 2021;8(4):3505-14.
8. Gour R, Shende S, Melwani V, et al. Pattern and risk factors of retinopathy of prematurity in tertiary care centre. Indian Journal of Clinical and Experimental Ophthalmology 2021;7(4):695-8.
9. Patel SS, Shendurnikar N. Retinopathy of prematurity in India: incidence, risk factors, outcome and the applicability of current screening criteria. Int J Contemp Pediatr 2019;6(6):2235-41.
10. Caberry W. Yu CM, Popovic MM, et al. Demographic risk factors of retinopathy of prematurity: a systematic review of population-based studies. Neonatology 2022;119(2):151-63.
11. Yang CY, Lien R, Yang PH, et al. Analysis of incidence and risk factors of retinopathy of prematurity among very-low- birth-weight infants in North Taiwan. Pediatr Neonatol 2011;52:321-6.
12. Azami M, Jaafari Z, Rahmati S, et al. Prevalence and risk factors of retinopathy of prematurity in Iran: a systematic review and meta- analysis. BMC Ophthalmol 2018;18:83.
13. Strawbridge JC, Janzen C, Chu A, et al. Maternal sociodemographic risk factors for retinopathy of prematurity. Invest Ophthalmol Vis Sci 2022;63:4188–F0248.
14. Karmouta R, Altendahl M, Romero T, et al. Association Between Social Determinants of Health and Retinopathy of Prematurity Outcomes. JAMA Ophthalmol 2022;140(5):496-502.
15. Hakeem AA, Mohamed GB, Othman MF. Retinopathy of prematurity: a study of prevalence and risk factors. Middle East Afr J Ophthalmol 2012;19:289-94.
16. Chaudhari S, Patwardhan V, Vaidya U, et al. Retinopathy of prematurity in a tertiary care center-incidence, risk factors and outcome. Indian Pediatr 2009;46:219-24.
17. Utomo MT, Harahap A, Etika R. Incidence and Risk Factors of Retinopathy of Prematurity (ROP): A Single Centre Study in a Tertiary Centre in Indonesia. International Journal of Research Publications 2021;87(1):266-76.
18. Nayyar M, Sood M, Panwar PK. Profile and risk factors of sight-threatening retinopathy of prematurity: Experience from SNCU in North India. Oman Journal of Ophthalmology 2024;17(2):224-33.
19. Terchandani U, Katoch D, Dogra MR. Five-year demographic profile of retinopathy of prematurity at a tertiary care institute in North India. Indian J Ophthalmol 2021;69:2127-31.